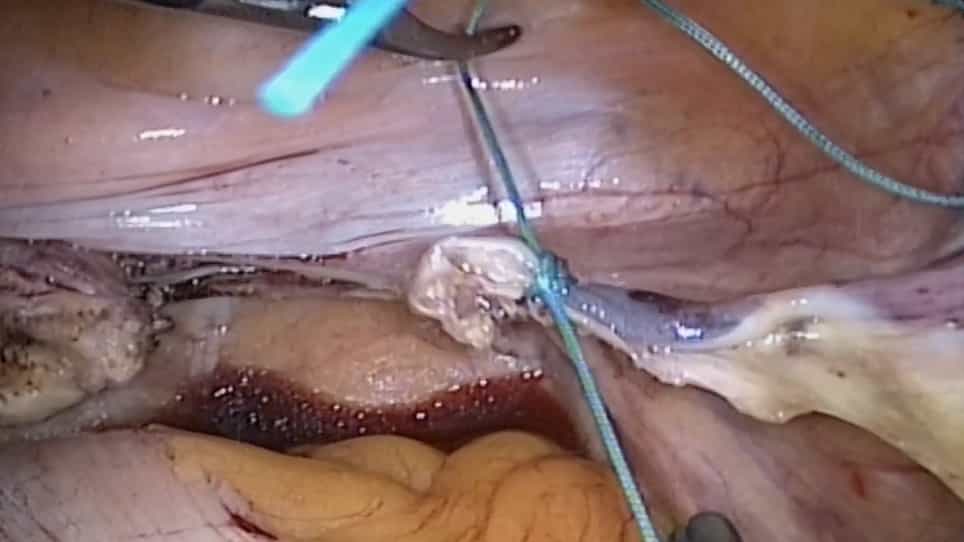
Related Experiment Video
Updated: Apr 20, 2026


Author Spotlight: Advancing Pelvic Prolapse Treatment with a Non-Mesh Approach using Laparoscopic Pectopexy
Published on: October 25, 2024
Route matters: comparing vaginal (TOT) and laparoscopic (MERT-Burch) approaches in stress urinary incontinence and
Burak Elmaağaç1, Ezgi Başaran2, Ali Yasin Özercan3
1Department of Urology, Kayseri Faculty of Medicine, University of Health Sciences, Kayseri City Hospital, Kayseri, 38080,Türkiye.

Background:
Stress urinary incontinence (SUI) negatively affects women's sexual well-being and quality of life through anxiety about urine leakage during intercourse.
Aim:
To compare the effects of vaginal (transobturator tape, TOT) and laparoscopic (Multiple Endoclip Retraction Technique-Burch, MERT-Burch) routes on postoperative sexual function, quality of life, and time to comfortable coitus.
Methods:
This retrospective study included 114 sexually active women who underwent TOT (n = 55) or laparoscopic MERT-Burch colposuspension (n = 59) between January 1, 2021, and August 5, 2025. Pre- and 6-month postoperative data were collected using validated questionnaires: International Consultation on Incontinence Questionnaire-Short Form (ICIQ-SF), Urogenital Distress Inventory-6 (UDI-6), Incontinence Quality of Life Questionnaire (I-QOL), Female Sexual Function Index (FSFI), and International Index of Erectile Function-5. Complications were graded by the Clavien-Dindo system.
Outcomes:
Primary outcomes were postoperative improvement in sexual function and the timing of first and comfortable coitus.
Results:
The mean age and body mass index were similar between groups. The MERT-Burch group resumed sexual activity significantly earlier (first coitus: 7 vs 35 days; comfortable coitus: 15 vs 54 days, P < .001). Both procedures improved ICIQ-SF, UDI-6, I-QOL, and FSFI scores (P < .001). Persistent dyspareunia occurred in 14.5% of TOT patients but in none after MERT-Burch. No major complications were recorded.
Clinical Implications:
Route of surgery affects postoperative sexual comfort and the time to first comfortable coitus, favoring the non-vaginal, mesh-free laparoscopic approach.
Strengths & Limitations:
Use of validated scales and the novel "first comfortable coitus" parameter are strengths; retrospective design and limited follow-up are limitations.
Conclusion:
Both techniques effectively restore continence, but the laparoscopic MERT-Burch provides earlier and more comfortable sexual recovery, establishing "first comfortable coitus" as a practical indicator of postoperative sexual healing.