Related Experiment Video
Updated: Apr 21, 2026


Catheter Ablation in Combination With Left Atrial Appendage Closure for Atrial Fibrillation
Published on: February 26, 2013
Incident Atrial Fibrillation and Flutter in Patients With Pulmonary Arterial Hypertension: Influence of Right
Danny Mohama1, Pitchaya Worapongsatitaya1, Bettia Celestin2
1Cardiovascular Division, Department of Medicine University of Minnesota Minneapolis MN USA.

Background:
The relationship between right atrial (RA) structural and functional remodeling and risk of incident atrial fibrillation/flutter (AF/AFL) in pulmonary arterial hypertension remains poorly defined.
Methods:
In a multicenter observational cohort study of 326 patients with pulmonary arterial hypertension, we evaluated associations between RA structure and function, as determined by echocardiography, and incident AF/AFL. Incidence rates were calculated using time-to-event analysis. Cox proportional hazards models identified factors associated with incident AF/AFL, and Harrell's C-statistics compared predictive performance. Survival decision tree and restricted cubic spline analyses identified thresholds associated with increased risk of AF/AFL.
Results:
The mean age was 51±15 years, 79% were women, and the mean REVEAL (Registry to Evaluate Early and Long-Term Outcomes in Pulmonary Arterial Hypertension) Lite score was 7.4±2.9. Over a median follow-up of 6.1 years, 56 patients (17.1%) developed AF/AFL, corresponding to an incidence rate of 25.3 cases (95% CI, 19.5-32.8) per 1000 person-years. Each 5% decrease in RA emptying fraction (hazard ratio [HR], 1.38 [95% CI, 1.03-1.86]; P=0.03) and each 1-cm increase in right ventricular basal diameter (HR, 1.55 [95% CI, 1.18-2.05]; P=0.002) were independently associated with 38% and 55% higher hazards of incident AF/AFL, respectively. The C-statistics for predicting incident AF/AFL were 0.62 for RA emptying fraction and 0.65 for right ventricular basal diameter. Survival decision tree and restricted cubic spline analyses identified thresholds for right ventricular basal diameter (≥5.4 cm) and RA emptying fraction (<17% and <45%) associated with increased AF/AFL risk.
Conclusions:
Larger right ventricular basal diameter and lower RA emptying fraction are associated with increased risk of incident AF/AFL in patients with pulmonary arterial hypertension and may help identify individuals at higher risk.


Related Concept Videos
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias
 01:29
Disturbances in Heart Rhythm
Arrhythmias are categorized by their speed, rhythm, and origin. A slow heart...
 01:26
Treatment for Pulmonary Arterial Hypertension: Receptor Tyrosine Kinase Inhibitors and Calcium Channel Blockers
TKIs, such as imatinib (Gleevec), are particularly effective in tackling the growth and mitogenic factors that become upregulated in PAH patients. These factors contribute to the...
 01:28
Dysrhythmias II: Classification of Tachyarrhythmias
 01:30
Pulmonary Hypertension: Classification and Pathogenesis
There are various classifications for PH, each relating to different underlying causes and also...
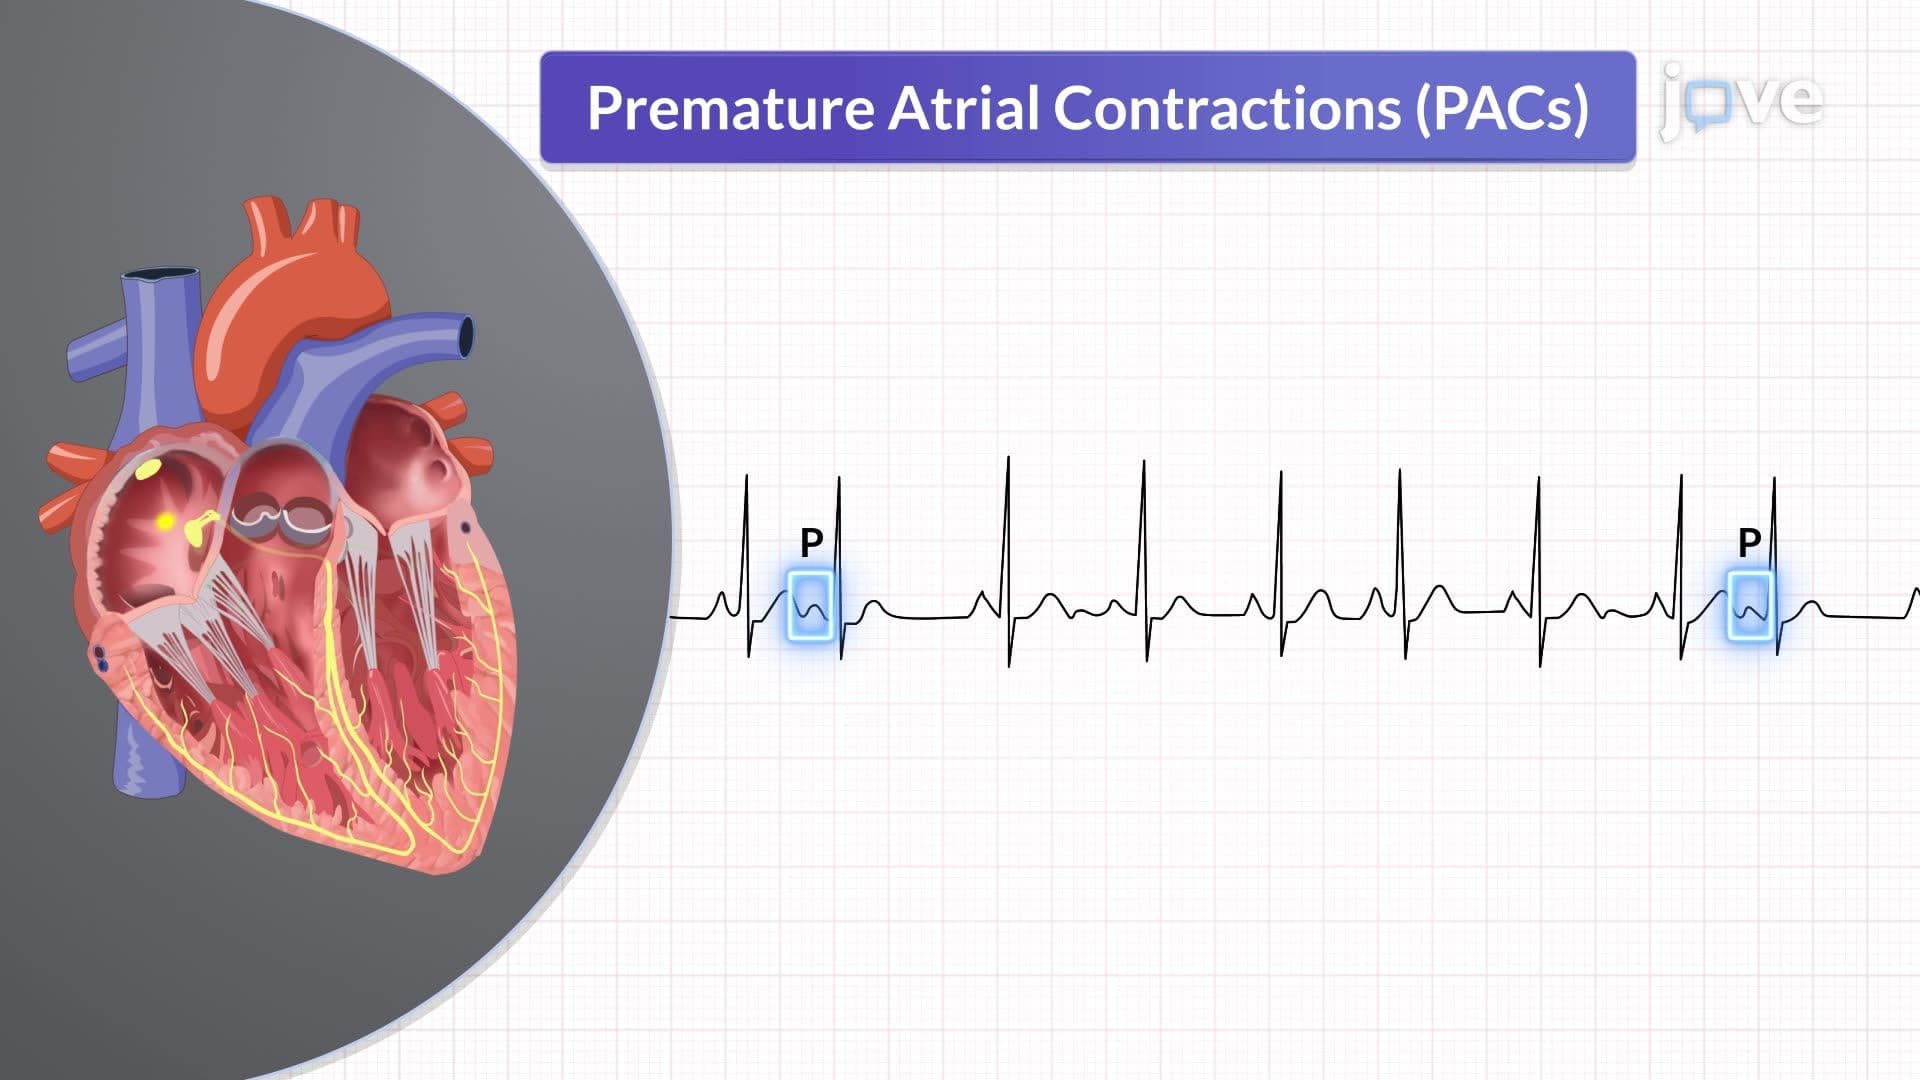 01:29
Dysrhythmias III: Characteristics of Dysrhythmias