Exercise-Induced Hypoalgesia Following Blood Flow Restriction in Rotator Cuff Repair Rehabilitation: A Randomized Crossover Clinical Trial
Related Experiment Video
Updated: Apr 21, 2026
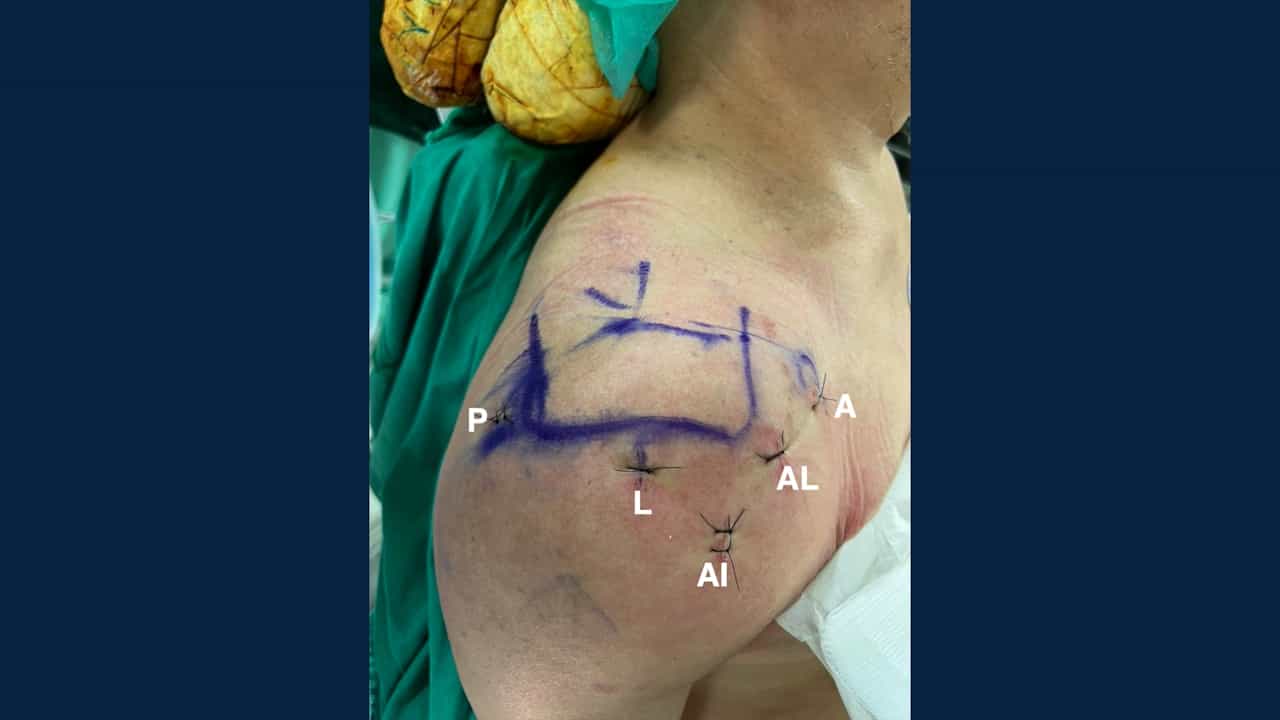
Knotless Independent Double-Row Repair and Biceps Augmentation for Anterosuperior Rotator Cuff Tears
Published on: January 23, 2026
Felipe Ponce-Fuentes1,2, Iván Cuyul-Vásquez3,4, Joaquín Salazar-Méndez5
1Escuela de Kinesiología, Facultad de Medicina y Ciencias de la Salud, Universidad Mayor, Temuco, Chile, umayor.cl.

Objectives:
To compare the acute effect on exercise-induced hypoalgesia (EIH) between isometric exercise with blood flow restriction (BFR) and isometric exercise alone in adults undergoing arthroscopic RC repair and to determine the level of correlation between EIH and kinesiophobia, disability and quality of life.
Design:
Blinded randomized crossover clinical trial.
Patients:
Twenty-three adults with degenerative rotator cuff (RC) repair.
Intervention:
Patients completed three shoulder isometric exercises. They were randomized to receive isometric exercises alone (control intervention) or isometric exercises with BFR (experimental intervention) in the first session and the alternate condition in the next session.
Outcomes:
Primary outcomes included pressure pain threshold (PPT) and conditioned pain modulation (CPM), assessed before, immediately after, and 10 min after isometric exercises with BFR and isometric exercises alone.
Results:
In the affected limb, BFR isometric exercises increased PPT immediately after exercise in upper trapezius (MD: 0.4 kg/cm2 [CI95% 0.1 to 0.9]), and in the unaffected limb, BFR isometric exercises increased deltoid PPT immediately after exercise (MD: 0.4 kg/cm2 [CI95% 0.1 to 0.7]). However, post hoc between-group comparisons showed that no significant differences existed between BFR and control at any time point, as all CI95% crossed zero and these changes did not exceed the minimum detectable change (≈1.1 kg/cm2). Besides, isometric exercise alone increased deltoid CPM immediately after in affected limb (MD: 30.1% [CI95% 10.8 to 49.4]) and 10 min after exercise in unaffected limb (MD: 12.0% [CI95% -0.4 to 24.4]). No significant changes were found in clinical pain intensity measured by the visual analog scale (VAS) at any time point. Statistically significant weak correlations were found between PPT with Western Ontario Rotator Cuff (WORC) index (r = -0.322 for sport, r = -0.331 for work, r = -0.302 for lifestyle; p < 0.05) and Shoulder Pain Disability Index (SPADI) (r = -0.309; p < 0.05), respectively.
Conclusion:
A single session of low-intensity isometric exercises with BFR did not produce a clinically meaningful EIH response nor was it superior to isometric exercise alone in patients after RC repair. The observed statistical signals did not reach the minimum detectable change, and the inconsistent CPM shifts suggest that BFR does not provide an additional acute advantage for endogenous pain modulation in this early postoperative stage. Trial Registration: ClinicalTrials.gov identifier: NCT06924112.