Related Experiment Video
Updated: Apr 22, 2026
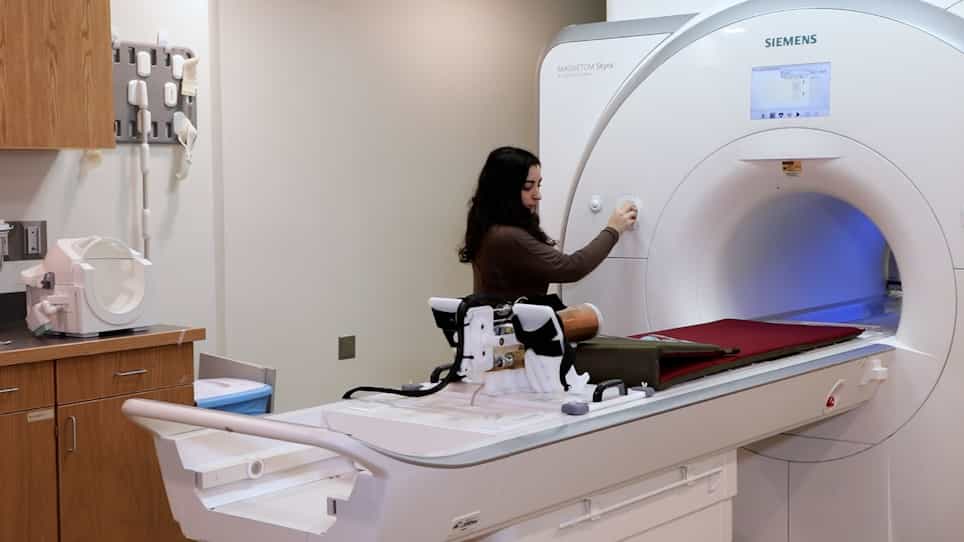

Use of a Foot-Induced Digitally Controlled Resistance Device for Functional Magnetic Resonance Imaging Evaluation in Patients with Foot Paresis
Published on: July 7, 2023
A HFMEA-driven Standardized Mobilization Protocol Reduces Adverse Events During Early Out-of-bed Activity in
Yun-Chen Tsai1, Shiou-Ying Chang2, Ting-Yuan Sheu1
1Division of Physical Therapy, Department of Physical Medicine and Rehabilitation.

Background:
Early mobilization in neurocritical care may support neurological recovery but is often deferred because of concerns regarding hemodynamic instability, airway compromise, and device-related adverse events. Current ICU mobilization frameworks provide limited neurocritical-specific guidance, leading to practice variation and preventable safety risks. System-level risk-mitigation strategies are therefore required.
Methods:
We conducted a prospective, single-center pre-post quality-improvement evaluation in a tertiary neurotrauma ICU. Healthcare Failure Mode and Effects Analysis (HFMEA) mapped the baseline mobilization process into 25 subprocesses, identifying 60 potential failure modes. High-risk pathways informed development of a standardized workflow incorporating eligibility thresholds, graded activity progression, structured interdisciplinary handoff, airway and device securement, and real-time electronic safety reporting. Mobilization-related adverse events, ventilator-tubing dislodgement, and screening accuracy were compared between a 6-month pre-implementation and a 12-month post-implementation phase, analyzed at the session level.
Results:
A total of 950 mobilization sessions were recorded pre-implementation and 781 post-implementation. Adverse-event rates decreased from 1.89% to 0.64% (relative risk: 0.34; 95% CI: 0.13-0.91; P =0.023), representing a 66.2% relative risk reduction. Ventilator-tubing dislodgement decreased from 0.42% to 0% (4/950 vs. 0/781). Eligibility-screening accuracy improved from 85% to 95% ( P <0.001). Structured handoff completion increased from 30% to 100%, and real-time electronic adverse-event reporting increased from 72% to 95%.
Conclusions:
An HFMEA-guided, standardized early-mobilization workflow reduced mobilization-related adverse events and improved process reliability in neurocritical care. Treating early mobilization as a safety-engineered process supports safer, more consistent ICU rehabilitation and provides a reproducible model for patient-safety improvement.

