Related Experiment Video
Updated: Apr 23, 2026


Improving IV Insulin Administration in a Community Hospital
Published on: June 11, 2012
Willingness to use a mobile syringe service program among people who inject drugs in rural Appalachia
Alex Elswick1,2, Amanda Fallin-Bennett3,4, Tasfia Jahangir5
1University of Kentucky, Lexington, USA. Alexander.elswick@uky.edu.

Background:
Rural people who use drugs face a litany of structural and psychosocial barriers to SSP utilization (e.g., unreliable transportation, stigma). Mobile SSPs may mitigate some barriers, but little is known about acceptability among rural people who use drugs and their preferences for mobile SSP design. This study examines (1) factors associated with willingness to use a mobile SSP among rural people who use drugs, and (2) their desired attributes and services.
Methods:
Data were collected from 259 participants who inject drugs that were recruited through outreach and respondent-driven sampling (RDS) in Appalachian Kentucky. In addition to descriptive analyses, independent variables' associations with the outcome (i.e., being willing to use a mobile SSP) were estimated using generalized estimating equations. All models controlled for lifetime use of a fixed-site SSP.
Results:
Overall, 59.9% (n = 155) endorsed mobile SSPs as a program they would be willing to use. People with lower income, had less reliable access to transportation, were using methamphetamine, were engaging in syringe sharing and reuse, and who had experienced more overdoses in their lifetime were more willing to use a mobile SSP than were their counterparts. Those who experienced more shame around their drug use were less likely to use a mobile SSP than those who experienced no shame. Participants were receptive to a variety of locations, unit sizes, and staffing models, but the most desired staffing and locations were clinical in nature and most preferred hours of operation were afternoon hours.
Discussion:
Findings suggest moderate willingness to engage in mobile SSP services among this population, particularly for people who use drugs who have challenges with transportation and who are engaging in behaviors that increase risk for HIV and HCV. Mobile SSPs may increase accessibility, acceptability, and ultimately, the utilization of critical harm reduction services in Appalachia.


Related Concept Videos
 01:30
Specialized Care Centers and Settings-II
Rural health centers are specialized care facilities in remote locations with very few medical personnel. The primary care providers who run the centers are mostly Registered Nurse Practitioners. Here, emergency treatment is provided to critically ill or injured patients before they are transferred to the closest hospital. Fortunately, due to advancement in technology, many rural healthcare facilities and professionals have easy access to diagnostic and treatment...
 01:28
Parenteral Drug Delivery Systems: Injectables, Implants, and Infusion Devices
 01:29
Drug Delivery: Parenteral Route
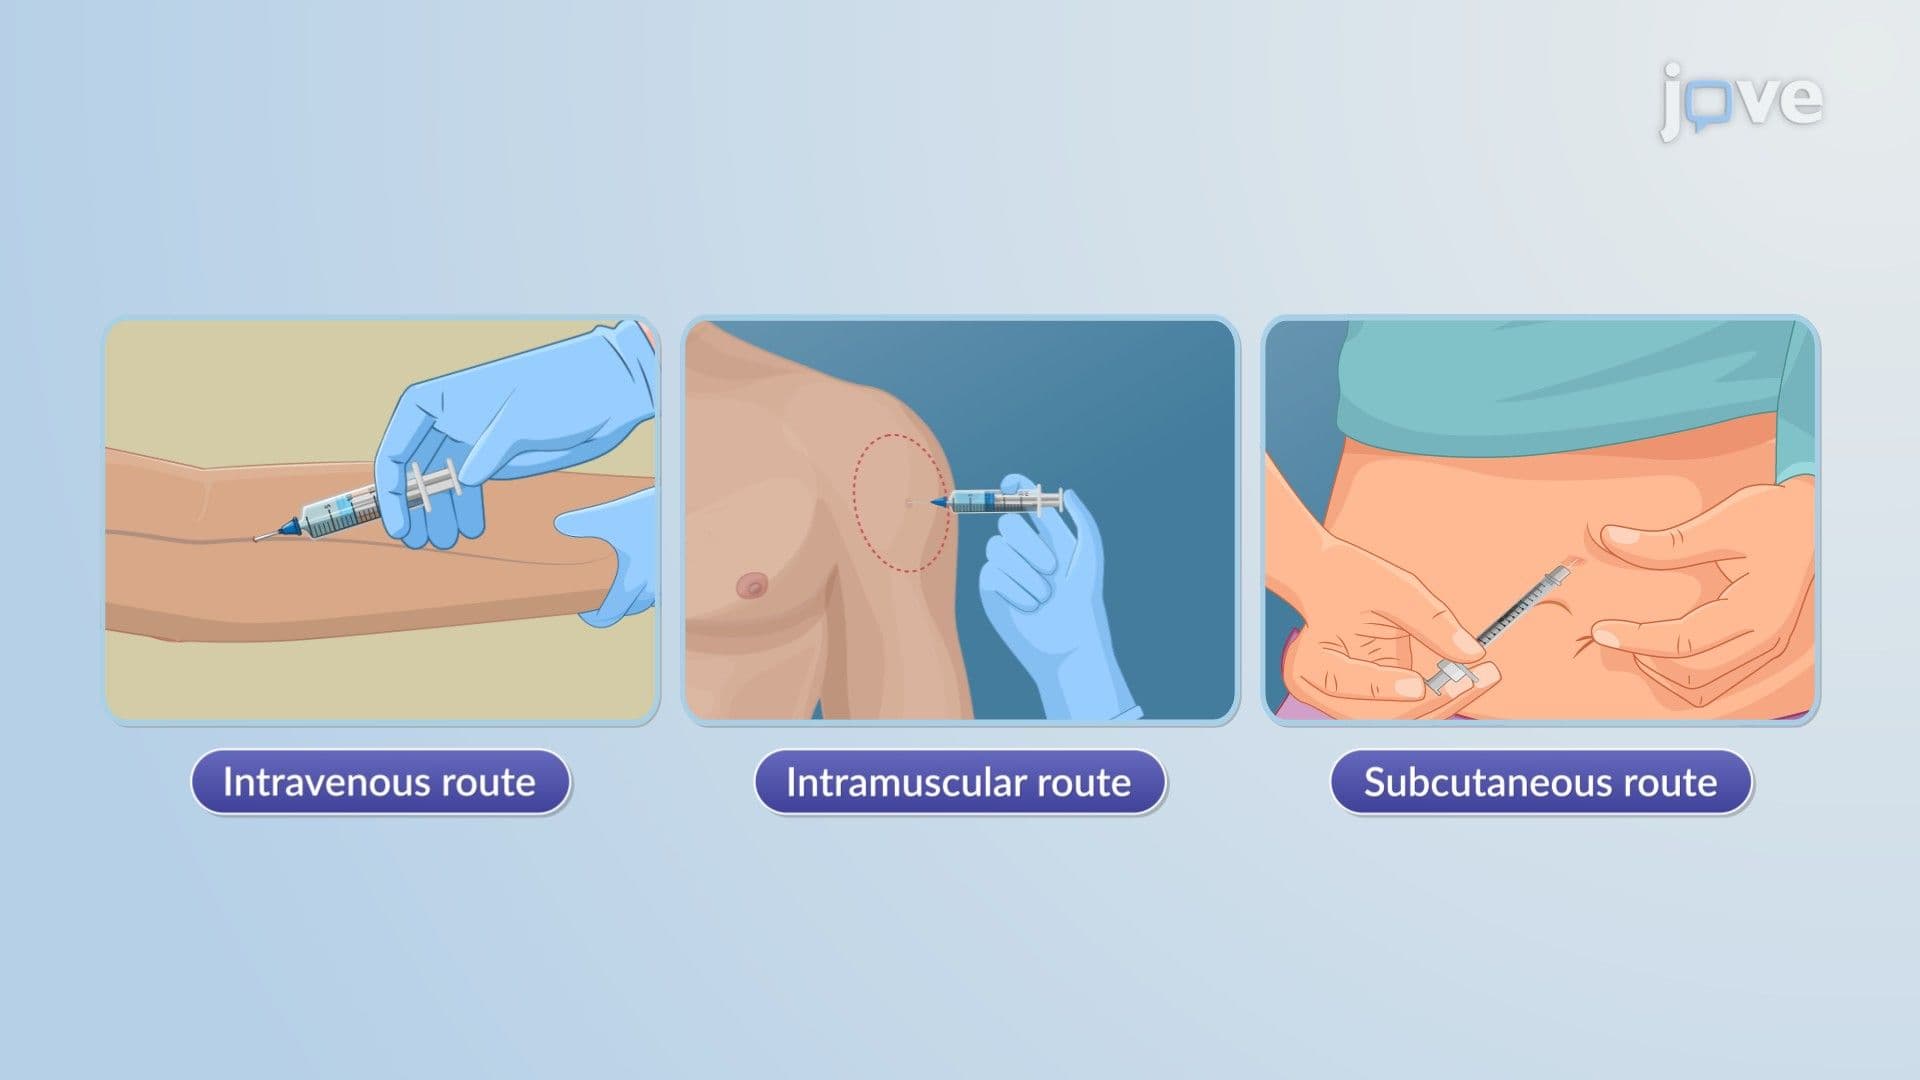
There are three primary parenteral routes: intravenous (IV), intramuscular (IM), and subcutaneous (SC). The IV route introduces the drug directly into the bloodstream, ensuring immediate action. The IM route...
 01:22
Drug Delivery: Miscellaneous Routes
Oral inhalation and nasal sprays swiftly transfer drugs across the respiratory epithelium's mucosal layer. Inhaled glucocorticoids and bronchodilators directly target lung conditions such as asthma, while fluticasone nasal spray mitigates allergic rhinitis.
Transdermal patches transport drugs...
 01:21
Drug Accumulation During Multiple Dosing: Repetitive IV Injections
 01:26
Methods Of Healthcare Delivery System
Managed Care System:
The managed care system is designed to control the cost while maintaining the quality of care. The patient's care from admission to discharge is planned by the primary care provider or the case manager, also known as the gatekeeper. In a managed care system, the number of care providers is...