Related Experiment Video
Updated: Jun 30, 2026
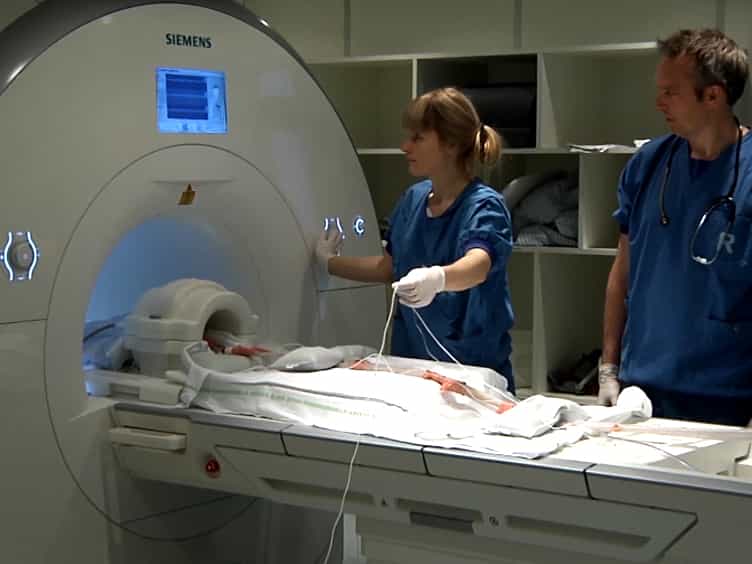

A Piglet Model of Neonatal Hypoxic-Ischemic Encephalopathy
Published on: May 16, 2015
Shared Frailty Survival Analysis of Neonatal Hypothermia and Its Predictors Among Neonates Admitted to the Neonatal
Aboma Tolessa Denta1, Yonas Shuke Kitawa2, Gezahagn Mekonnen Woldemedihn2
1Department of Statistics, College of Natural and Computational Science Oda Bultum University Chiro Ethiopia.

Background:
Neonatal hypothermia is a major public health concern that threatens the survival and well-being of newborns, particularly those admitted to neonatal intensive care units. In Ethiopia, where the burden of neonatal hypothermia remains high, it contributes substantially to neonatal morbidity and mortality. This study aimed to model the time to recovery from neonatal hypothermia and identify its predictors using a shared frailty survival analysis among neonates admitted to the neonatal intensive care unit at Pawe General Hospital.
Methods:
A retrospective follow-up study was conducted among 425 neonates admitted with hypothermia to the NICU of Pawe General Hospital. Time to recovery was analyzed using survival analysis techniques. Non-parametric methods were used to compare recovery experiences across demographic and clinical characteristics, and parametric accelerated failure time and shared frailty models were fitted to identify significant predictors while accounting for unobserved heterogeneity. Model selection was based on Akaike Information Criterion (AIC) and Bayesian Information Criterion (BIC).
Results:
The log-logistic gamma shared frailty model was identified as the best-fitting model. The frailty effect at the level of place of childbirth was statistically significant (θ = 1.228; χ² = 84.24, p < 0.001), indicating substantial unobserved heterogeneity with moderate intra-cluster dependence (τ = 0.38). Maternal age 20-29 years (AF = 0.842) and 30-39 years (AF = 0.707), urban residence (AF = 0.823), and above-average family income (AF = 0.834) were associated with shorter recovery times. Female neonates had slightly prolonged recovery (AF = 1.110). Very low and low birth weight, as well as preterm and post-term gestational ages, were associated with delayed recovery. Early initiation of breastfeeding (AF = 0.365) and skin-to-skin contact (AF = 0.801) accelerated recovery, whereas CPR at birth (AF = 0.857) and admission-related complications, including prematurity, low birth weight, sepsis, respiratory distress syndrome, asphyxia, and congenital malformations, were strong predictors of prolonged recovery time from neonatal hypothermia.
Conclusion:
The findings indicate that recovery from neonatal hypothermia is influenced by maternal, socioeconomic, neonatal, clinical, and contextual factors. The significant frailty effect underscores the importance of accounting for clustering by place of childbirth when modeling recovery time. Interventions aimed at improving early breastfeeding practices, promoting skin-to-skin contact, and strengthening neonatal care, particularly for preterm and low birth weight infants, may substantially reduce recovery time and improve neonatal outcomes.
More Related Videos
 07:36
Modeling Encephalopathy of Prematurity Using Prenatal Hypoxia-ischemia with Intra-amniotic Lipopolysaccharide in Rats
Published on: November 20, 2015
 05:15
Amplitude-Integrated EEG in Infants at Risk of Hypoxic-Ischemic Encephalopathy: A Feasibility Study in Road and Air Transport in Western Australia
Published on: June 21, 2024
