Related Experiment Video
Updated: Apr 24, 2026

Comparative Proteomic Analysis of Whole Kidney, Medulla, and Cortical Tubules in Diabetic Pathogenesis of Kidney Injury in Mice
Published on: May 2, 2025
Beyond BMI: The integrated impact of obese-metabolic-anthropometric phenotypes on chronic kidney disease risk
Zihan Xu1, Yingbai Wang1, Jiaofeng Xiang1
1Clinical Research Service Center, Affiliated Hospital of Guangdong Medical University, Zhanjiang 524001, China; Guangdong Engineering Technology Research Center of Collaborative Innovation of Clinical Medical Big Data Cloud Service in Medical Consortium of West Guangdong, Affiliated Hospital of Guangdong Medical University, Zhanjiang 524001, China.

Background:
Chronic kidney disease (CKD) is a global health challenge. Body mass index (BMI) fails to capture the heterogeneity of fat distribution and metabolic status in obesity. We aimed to investigate whether integrated obese-metabolic-anthropometric phenotypes, which simultaneously consider adiposity, metabolic health, and body shape, provide a superior framework for identifying individuals at high risk of CKD.
Methods:
This prospective cohort study included 343,993 participants from the UK Biobank without pre-existing CKD. Obese-metabolic-anthropometric phenotypes were defined by integrating BMI, a metabolic health score, and body shape (based on A Body Shape Index and Hip Index). Cox proportional hazards models were used to estimate hazard ratios (HRs) and 95% confidence intervals (CIs) for incident CKD. Population attributable risk (PAR) was calculated to quantify the CKD burden attributable to different phenotypes. K-modes cluster analysis classified individuals into four distinct subtypes.
Results:
Over a mean follow-up of 13.6 years, 16,037 incident CKD cases were recorded. Compared to the reference group (metabolically healthy non-obese with slim shape), both metabolically unhealthy obese wide-shaped (MUOW) and apple-shaped (MUOA) phenotypes demonstrated substantially elevated CKD risk, with fully adjusted HRs of 2.26 (95% CI: 2.10-2.43) and 2.68 (95% CI: 2.48-2.89), respectively. PAR analysis revealed that the integrated phenotype contributed most to the population-level CKD burden (PAR: 29.3%, 95% CI: 20.8-38.3%), far exceeding the contribution of any single component. Cluster analysis further delineated a high-risk cluster characterized by co-existing obesity and metabolic dysfunction, which exhibited an 89% increased risk of CKD (HR: 1.89, 95% CI: 1.80-1.97).
Conclusion:
The confluence of obesity, metabolic dysfunction, and an adverse body shape synergistically substantially elevates CKD risk. Moving beyond BMI to multidimensional phenotyping enables precision identification of high-risk individuals for targeted preventive strategies.
More Related Videos
 06:16
White and Brown Adipose Grafts: An Approach to Correct Reproductive, Metabolic, and Renal Deficits in Black and Tan Brachyury (BTBR) Obese Mice
Published on: September 9, 2025
 07:22
Glycemic Impact on Knee Osteoarthritis Symptoms on Physical, Radiographic, and Inflammatory Markers among Individuals Aged 50 and Over with Diabetes
Published on: March 7, 2025
Related Concept Videos
 01:20
Pharmacokinetics in Obese Patients: Drug Metabolism and Excretion
 01:25
Pharmacokinetics in Obese Patients: Drug Absorption and Distribution
 01:21
Drug Dosing: Obese Patients
 01:25
Chronic Kidney Disease I: Introduction
 01:21
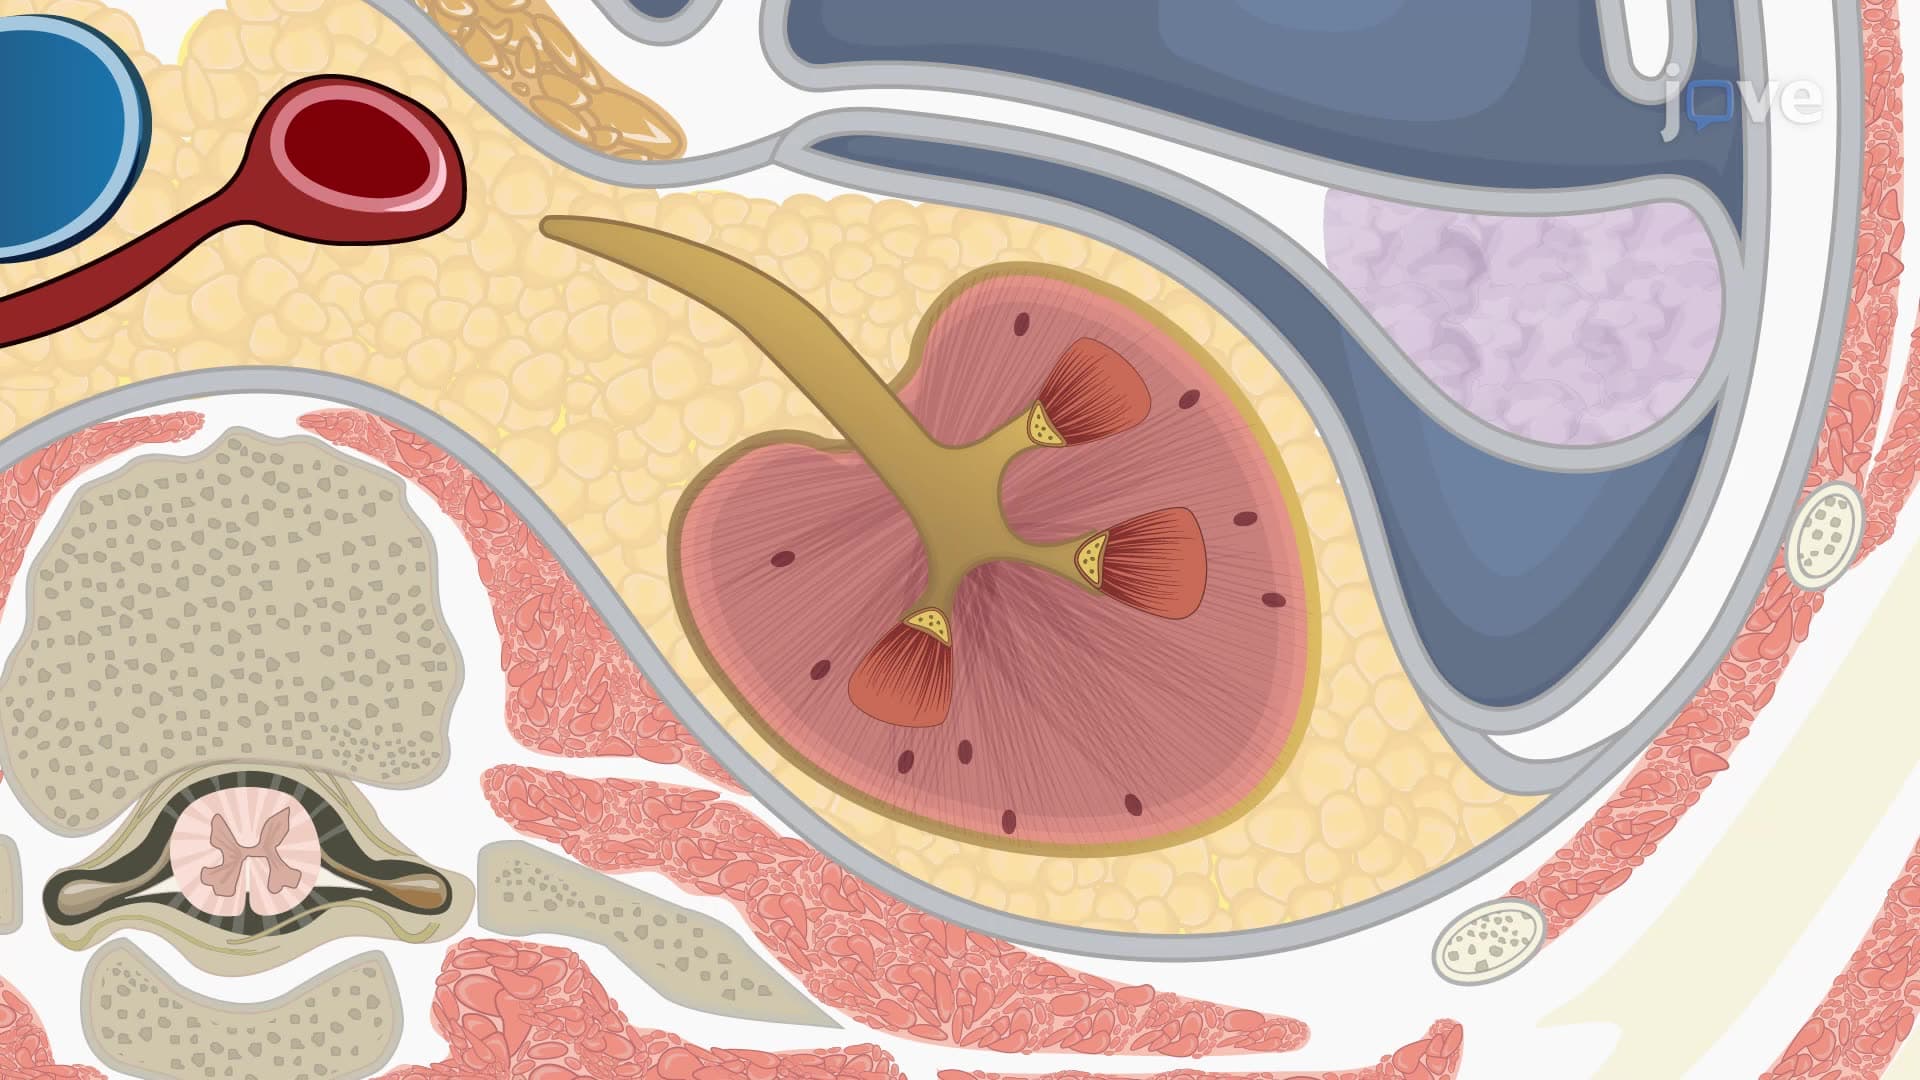
External Anatomy of the Kidney
The kidneys are located in the retroperitoneal space on either side of the vertebral column, protected posteriorly by the 11th and 12th ribs. The right kidney sits slightly lower than the left owing to the presence of the liver...
 01:24
Obesity