Related Experiment Video
Updated: Apr 24, 2026
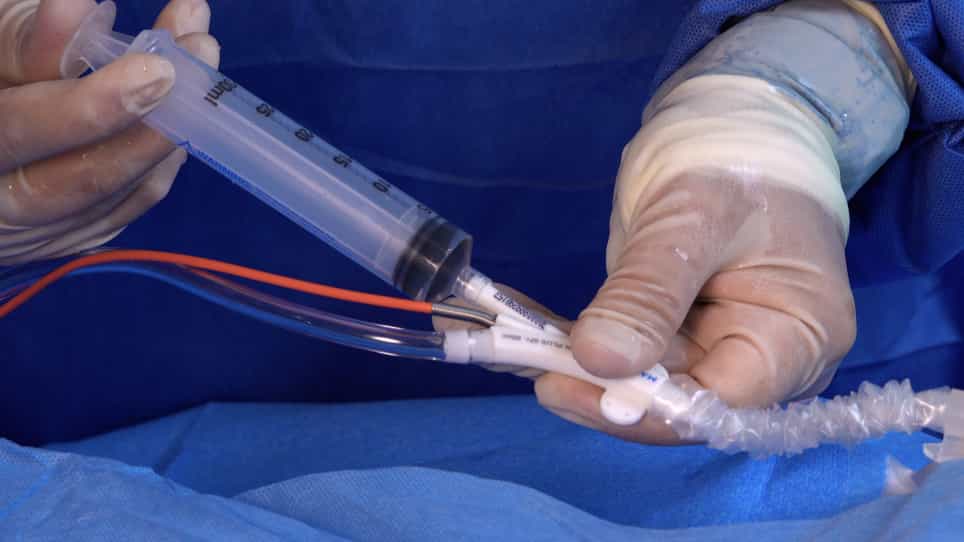

The Intra-Aortic Balloon Pump
Published on: February 5, 2021
Escalation From Intra-Aortic Balloon Pump to Extracorporeal Membrane Oxygenation may be Associated With Poor Outcomes
Liangshan Wang1, Kexin Wang1, Huiruo Liu1
1Center for Cardiac Intensive Care, Beijing Anzhen Hospital, Capital Medical University, People's Republic of China.

Insights
Escalating from intra-aortic balloon pump (IABP) to venoarterial extracorporeal membrane oxygenation (VA-ECMO) is linked to worse outcomes in cardiogenic shock patients. This IABP-ECMO strategy shows higher in-hospital mortality and complications.
Area of Science:
- Cardiology
- Critical Care Medicine
- Mechanical Circulatory Support
Background:
- Venoarterial extracorporeal membrane oxygenation (VA-ECMO) is increasingly used for refractory cardiogenic shock (CS).
- Intra-aortic balloon pump (IABP) use in CS is being de-emphasized, yet escalation to VA-ECMO (IABP-ECMO) remains frequent.
- The outcomes associated with the IABP-ECMO strategy require further investigation.
Purpose of the Study:
- To investigate the association between escalating from IABP to VA-ECMO and patient outcomes.
- To compare outcomes between patients receiving IABP before VA-ECMO and those receiving direct VA-ECMO.
- To identify potential risks associated with the IABP-ECMO approach.
Main Methods:
- Retrospective analysis of adult patients from the Chinese Extracorporeal Life Support (CSECLS) registry (January 2017–August 2022).
- Patients were categorized into IABP-ECMO group (received IABP before VA-ECMO) and direct ECMO group (did not receive IABP).
- Primary outcome was in-hospital mortality; secondary outcomes included on-support mortality and limb ischemia.
Main Results:
- Out of 4,607 patients, 655 (14.2%) were in the IABP-ECMO group.
- The IABP-ECMO group was older and more likely to have acute myocardial infarction but less likely to have cardiac arrest prior to ECMO.
- In-hospital mortality was higher in the IABP-ECMO group (57.1% vs. 51.4%, p=0.007), persisting after multivariable adjustment (aOR 1.34).
- IABP-ECMO was also associated with increased on-support mortality (aOR 1.50) and limb ischemia (aOR 2.20).
Conclusions:
- Escalation from IABP to VA-ECMO in adults with cardiogenic shock is associated with increased in-hospital mortality.
- The IABP-ECMO strategy may also lead to higher rates of on-support mortality and limb ischemia.
- These findings suggest caution when considering IABP as a bridge to VA-ECMO.
Background & Aim:
Venoarterial extracorporeal membrane oxygenation (VA-ECMO) has been increasingly used for refractory cardiogenic shock (CS). Although guidelines have downgraded the recommendations for intra-aortic balloon pump (IABP) in CS, escalation from IABP to ECMO (IABP-ECMO) remains common in patients with CS. This study aims to determine the association between IABP-ECMO and outcomes for patients undergoing VA-ECMO.
Method:
Adults who received IABP before VA-ECMO (IABP-ECMO group) or did not receive IABP before ECMO (direct ECMO group) from 1 January 2017, through 31 August 2022 were extracted from the Chinese Extracorporeal Life Support (CSECLS) registry. The primary outcome was in-hospital mortality.
Results:
Among 4,607 patients meeting study inclusion, 655 (14.2%) received IABP before VA-ECMO. Patients in the IABP-ECMO group were older (age 61 vs 55 years), were more likely to have acute myocardial infarction (68.7% vs 39.1%), and were less likely to have cardiac arrest before ECMO (25.8% vs 41.4%) (all p<0.001). In-hospital mortality (57.1% vs 51.4 %; p=0.007) occurred more frequently in the IABP-ECMO group which persisted in multivariable modelling (adjusted odds ratio [aOR] 1,34; 95% confidence interval [CI] 1.08-1.67; p=0.008). Escalation from IABP to ECMO was also associated with on-support mortality (aOR 1.50; 95% CI 1.19-1.88; p=0.001) and limb ischaemia (adjusted OR 2.20; 95% CI 1.62-2.99; p<0.001).
Conclusions:
Among adults receiving VA-ECMO, escalation from IABP to ECMO may be associated with poor in-hospital outcomes.
More Related Videos
 03:40
Point-of-Care Ultrasound for Peripheral Veno-Arterial Extracorporeal Membrane Oxygenation Without Left Ventricular Venting
Published on: January 17, 2025
 06:10
Utilizing Percutaneous Ventricular Assist Devices in Acute Myocardial Infarction Complicated by Cardiogenic Shock
Published on: June 12, 2021
Related Concept Videos
 01:25
Cardiopulmonary Resuscitation IV: Pharmacological Management
 01:22
Cardiopulmonary Resuscitation II: ACLS Airway Management
 01:22
Heart Failure VI: Adjunct Therapies