Related Experiment Video
Updated: Apr 24, 2026
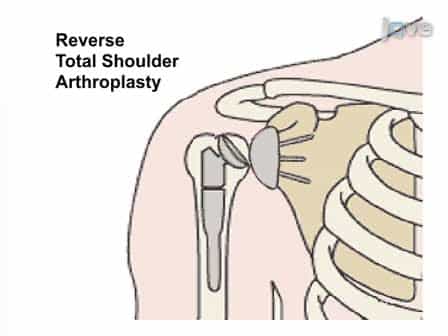
Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
Anterior deltoid atrophy after reverse shoulder arthroplasty: a preliminary prospective study on surgical approach
Yaiza Lopiz1,2, Alberto Rodrígiez-González3, Eduardo Ossuna-Juntadez3
1Shoulder and Elbow Unit, Department of Traumatology and Orthopaedic Surgery, Clínico San Carlos Hospital, Madrid, Spain. mlopiz@ucm.es.

Purpose:
To assess the incidence of anterior deltoid atrophy following reverse total shoulder arthroplasty (RTSA) for rotator cuff arthropathy (RCA), to investigate its association with the surgical approach and neurophysiological injury of the anterior branch of the axillary nerve, and to determine its impact on postoperative shoulder flexion.
Methods:
Prospective observational cohort study of 31 patients (mean age 77.9 ± 5.4 years; 85% female) with RCA undergoing RTSA at a single tertiary centre (2014-2017). Two approaches were used: deltopectoral (DP, n = 20) and superolateral (SL, n = 11). Neurophysiological evaluation (electroneurography + quantitative needle EMG) of the axillary and suprascapular nerves was performed preoperatively and at three and six months postoperatively by a single experienced neurophysiologist. Anterior deltoid atrophy was assessed at 12 months using a pre-specified standardised clinical inspection protocol: visible anterior deltoid contour concavity at rest, confirmed on active elevation against gravity, graded as present or absent by a single blinded examiner. Convergent support was provided by the observed difference in shoulder flexion between groups and by the EMG data. Shoulder flexion and the Constant-Murley Score (CMS) were recorded at baseline and 12 months.
Results:
Preoperative axillary nerve injury was present in 77.4% of patients, predominantly affecting the anterior branch (48.4%). Acute postoperative axillary nerve injury occurred in 25.8% of the overall cohort. At 12 months, anterior deltoid atrophy was identified in 13/31 patients (41.9%), with a significantly higher rate in the SL group (72.7% vs 25%; p = 0.021). The rate of acute postoperative injury to the anterior axillary nerve branch did not differ significantly between patients with and without deltoid atrophy (23.1% vs 22.2%; p = n.s.). Patients with atrophy achieved a mean anterior flexion of 115° (SD 8.7°) versus 137° (SD 7.4°) in those without (difference 22°; 95% CI 1.5-31.2; p = 0.066; Cohen's d = 0.87). Both groups improved significantly from baseline.
Conclusion:
Anterior deltoid atrophy is common after RTSA (42%) and is significantly associated with the superolateral approach. The absence of a neurophysiological correlate is consistent with a mechanical aetiology related to deltoid reinsertion technique, although causality cannot be established from this observational study. These findings generate a testable hypothesis warranting prospective evaluation of bony acromial flap reinsertion in future comparative studies.
More Related Videos
 04:27
Anterior Capsular Reconstruction with Human Dermal Allograft for Irreparable Subscapularis Tears
Published on: May 9, 2025
 07:22
Arthroscopic Management of Massive Irreparable Rotator Cuff Tears: Whole Rotator Cable Reconstruction Using Proximal Biceps Tendon Autograft
Published on: June 6, 2025
Related Concept Videos
 01:23
Muscles of the Shoulder
Anterior Thoracic Muscles
The anterior thoracic muscles include the serratus anterior, subclavius, and...
 01:31
Muscles that Move the Arm
The pectoralis major has two origins. Its clavicular head originates on the medial half of the clavicle. In contrast, the sternocostal head originates on the costal cartilages of ribs 1-6, the sternum, and the aponeurosis of the external oblique of the...