Related Experiment Video
Updated: Apr 25, 2026


Transesophageal Atrial Burst Pacing for Atrial Fibrillation Induction in Rats
Published on: February 14, 2022
Atrial Effective Refractory Periods in Patients With Frequent Premature Atrial Complexes: Implications for Atrial
Satoshi Higuchi1, Gaku Hatayama2, Satoshi Miyazawa3
1Department of Cardiology, Tokyo Women's Medical University, Tokyo, Japan; Clinical Research Division for Heart Rhythm Management Department of Cardiology, Tokyo Women's Medical University, Tokyo, Japan; Department of Cardiology, Sendai Cardiovascular Center, Miyagi, Japan.

Background:
Recent animal models show that frequent premature atrial complexes (PACs) induce atrial remodeling through conduction slowing without altering the atrial effective refractory period (AERP), suggesting a mechanism distinct from atrial fibrillation (AF)-induced remodeling. However, the impact of frequent PACs on human AERP remains unclear.
Objectives:
The purpose of this study was to compare AERP characteristics in patients with isolated frequent PACs and those with AF.
Methods:
This prospective study included patients undergoing ablation for isolated frequent PACs, paroxysmal atrial fibrillation (PAF), or persistent AF. After a 6-beat 600-ms drive train (S1), the S2 interval was increased in 10-ms steps until atrial capture occurred; the longest noncapturing S2 was defined as AERP. AERPs were measured at 9 sites, including 4 pulmonary veins (PVs), and 5 extra-PV regions. Interatrial conduction time was measured from P-wave onset to latest activation on the coronary sinus catheter.
Results:
A total of 143 patients were included (PAC: n = 21, burden 36 ± 17%; PAF: n = 65; persistent AF: n = 57). In the PVs, AERP was longest in PAC, intermediate in PAF, and shortest in persistent AF (PAC: 254.9 ± 22.4 vs PAF: 229.5 ± 38.6 vs persistent AF: 205.4 ± 29.1 ms; P < 0.001). In extra-PV regions, AERPs were similar between PAC and PAF, whereas persistent AF showed significantly shorter values (256.0 ± 21.7 vs 260.9 ± 28.2 vs 225.7 ± 24.2ms; P < 0.001). Interatrial conduction time was comparable between PAC and PAF but prolonged in persistent AF (122 ± 12 vs 118 ± 20 vs 131 ± 23 ms; P = 0.004). Multivariable regression demonstrated arrhythmia type as an independent determinant of both PV and extra-PV AERP (standardized β = -0.54 and -0.62, respectively; P < 0.001). Within PAC patients, AERPs did not differ by PAC origin.
Conclusions:
Isolated frequent PACs were characterized by preserved AERP in both PV and extra-PV regions. Shorter AERPs in the PVs in PAF and more widespread AERP shortening in persistent AF may reflect the transition from PACs to PAF and then progression to persistent AF.


Related Concept Videos
 01:25
ECG Interpretation of Arrhythmias II: Atrial, Junctional and Ventricular Arrhythmias
 01:18
Dysrhythmias IV: Characteristics of Bradyarrhythmias
 01:29
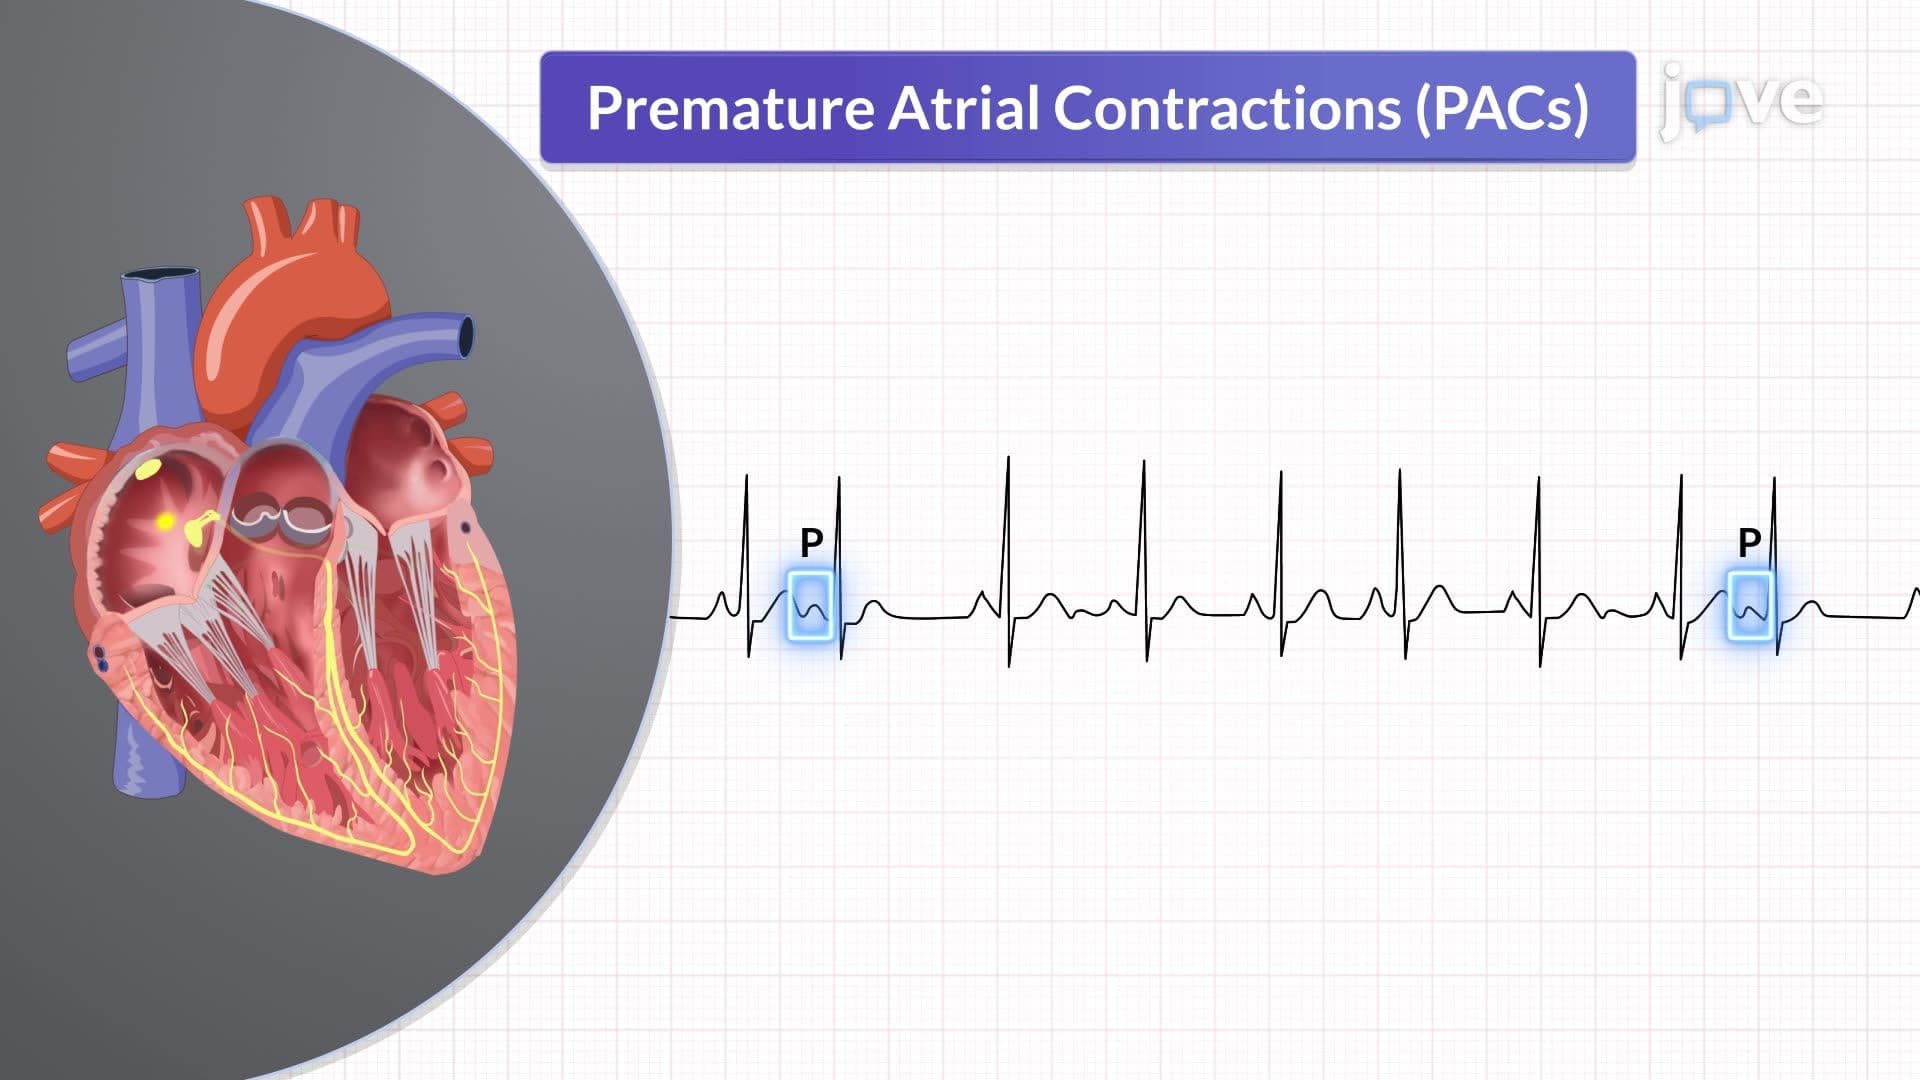
Dysrhythmias III: Characteristics of Dysrhythmias
 01:29
Disturbances in Heart Rhythm
Arrhythmias are categorized by their speed, rhythm, and origin. A slow heart...
 01:30
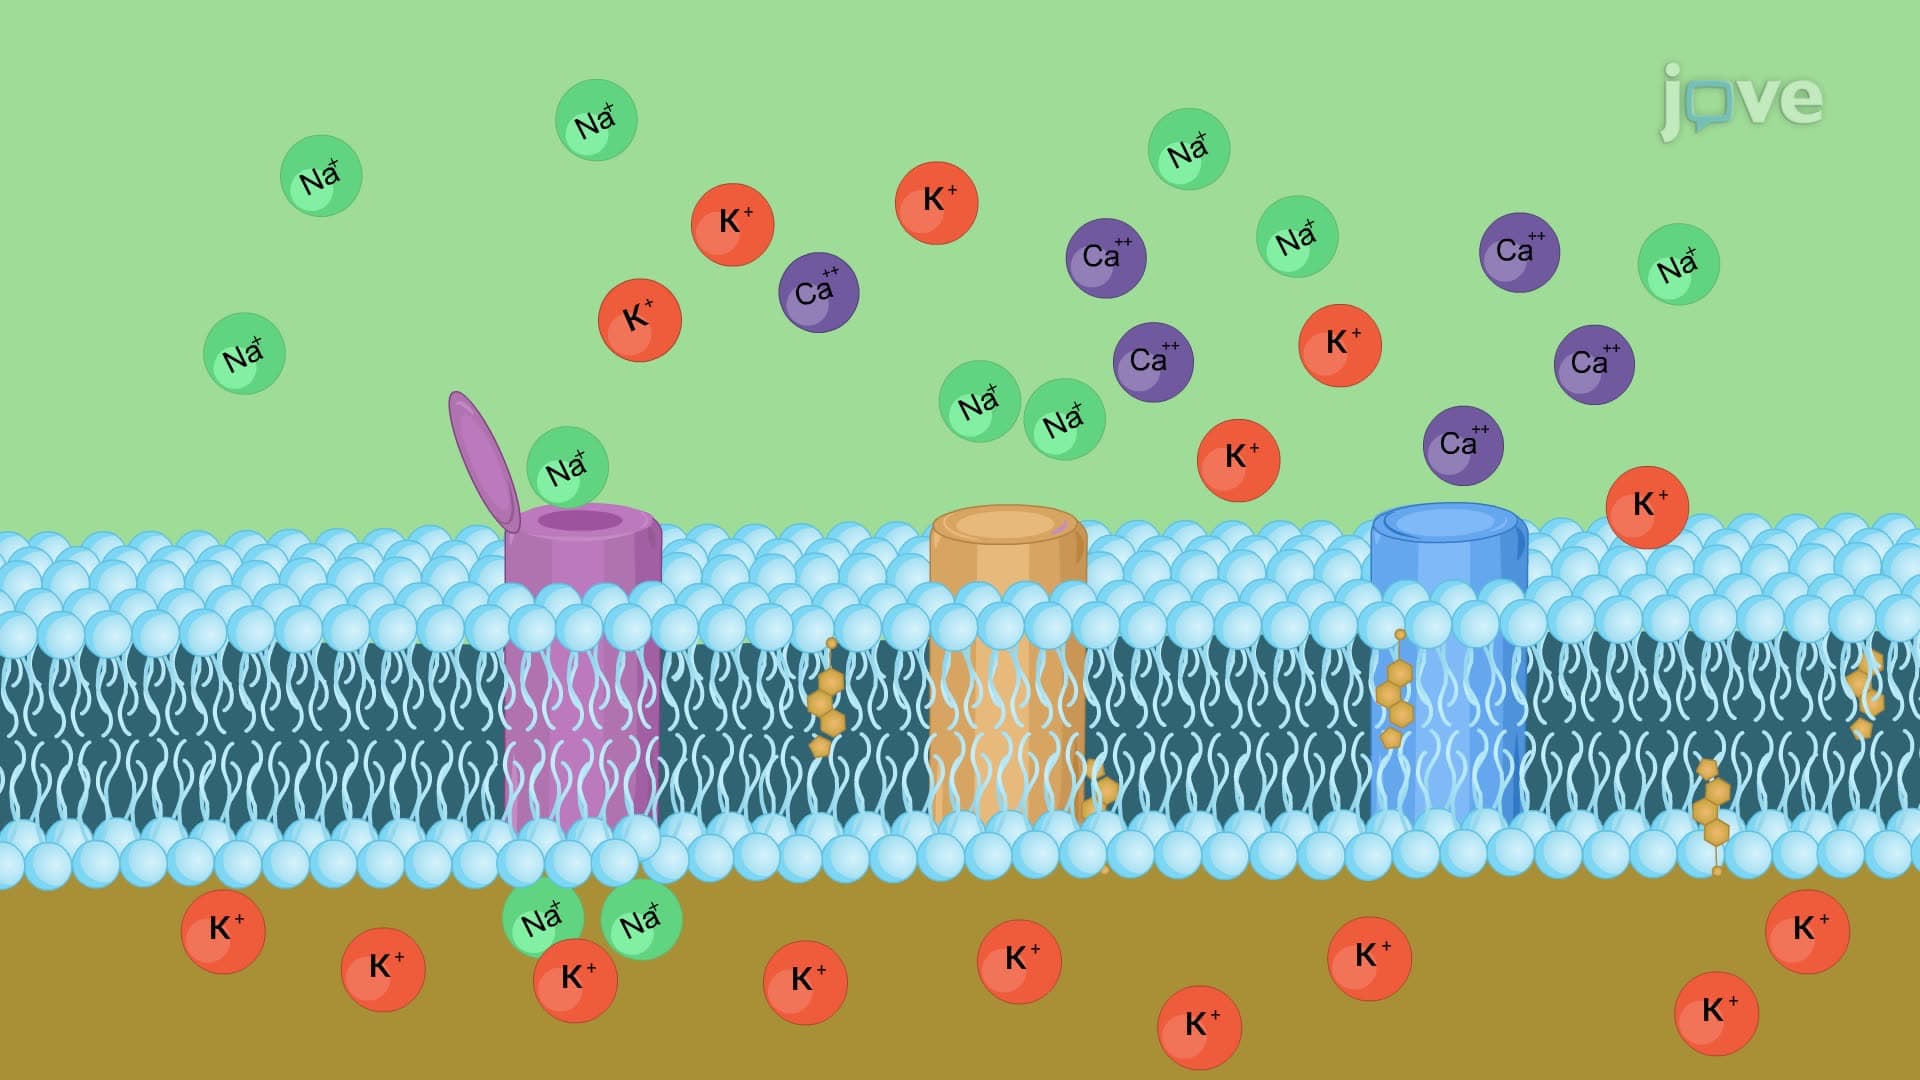
Cardiac Action Potential
The cardiac action potential process involves a series of phases characterized by the movement of ions across the cardiac cell membranes, leading to the depolarization and repolarization of the cardiac myocytes.
Ionic Basis of Cardiac Action Potentials
 01:25
Dysrhythmias VI: Management of Dysrhythmias