Related Experiment Video
Updated: Apr 25, 2026

Halogenated Agent Delivery in Porcine Model of Acute Respiratory Distress Syndrome via an Intensive Care Unit Type Device
Published on: September 24, 2020
Airway Secretion Volume and Physiological Effects of High-Flow Nasal Cannula in Acute Respiratory Failure Caused by
Nicolás Colaianni-Alfonso1, Guillermo Montiel1, Catalina Siroti1,2
1Mr. Colaianni-Alfonso, Dr. Montiel, Ms. Siroti, and Mr. Castro-Sayat are affiliated with the Respiratory Intermediate Care Unit, Hospital General Agudos Juan A. Fernández, Ciudad Autonoma de Buenos Aires, Argentina.

Background:
Acute respiratory failure (ARF) in bronchiectasis is frequently accompanied by excessive airway secretions. High-flow nasal cannula (HFNC) delivers heated, humidified gas and may improve respiratory mechanics, but quantitatively measured secretion burden during HFNC in bronchiectasis-related ARF is poorly described.
Methods:
We conducted a prospective, single-center pilot cohort study in a respiratory intermediate care unit including adults with computed tomography-confirmed bronchiectasis admitted with ARF and treated with HFNC as first-line therapy. The primary outcome was cumulative secretion volume (operationally defined as supervised collection of expectorated sputum, with measures to minimize saliva contamination) during the first 3 days of HFNC exposure. Physiologic variables, gas exchange, dyspnea, and clinical outcomes were assessed descriptively.
Results:
Twenty-six subjects were enrolled (median age 67 years, 54% female), predominantly with moderate-to-severe bronchiectasis. Median cumulative secretion volume over 72 h was 510 mL (436-743), and daily secretion volume increased from Day 1 to Day 3 (P < .001). Breathing frequency, oxygenation, dyspnea (Borg scale), and selected gas-exchange variables changed significantly over time. No subject required escalation to noninvasive ventilation or endotracheal intubation. In-hospital mortality was 11.5% (3/26), occurring exclusively in subjects with preestablished do-not-intubate directives.
Conclusions:
In this pilot cohort of bronchiectasis-related ARF, structured quantification of secretion volume during HFNC was feasible and documented a large early secretion burden over 72 h. Given the uncontrolled design, these findings are descriptive and should not be interpreted as evidence of treatment effect.
More Related Videos
 06:22
Surfactant Depletion Combined with Injurious Ventilation Results in a Reproducible Model of the Acute Respiratory Distress Syndrome ARDS
Published on: April 7, 2021
 08:25
Combining Volumetric Capnography And Barometric Plethysmography To Measure The Lung Structure-function Relationship
Published on: January 8, 2019
Related Concept Videos
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...
 01:19
Factors Affecting Pulmonary Ventilation
Alveolar Surface Tension
The alveolar fluid lines the luminal surface of the alveoli and exerts a force called surface tension. This force is caused by the polar water molecules in the liquid being more strongly attracted to each...
 01:29
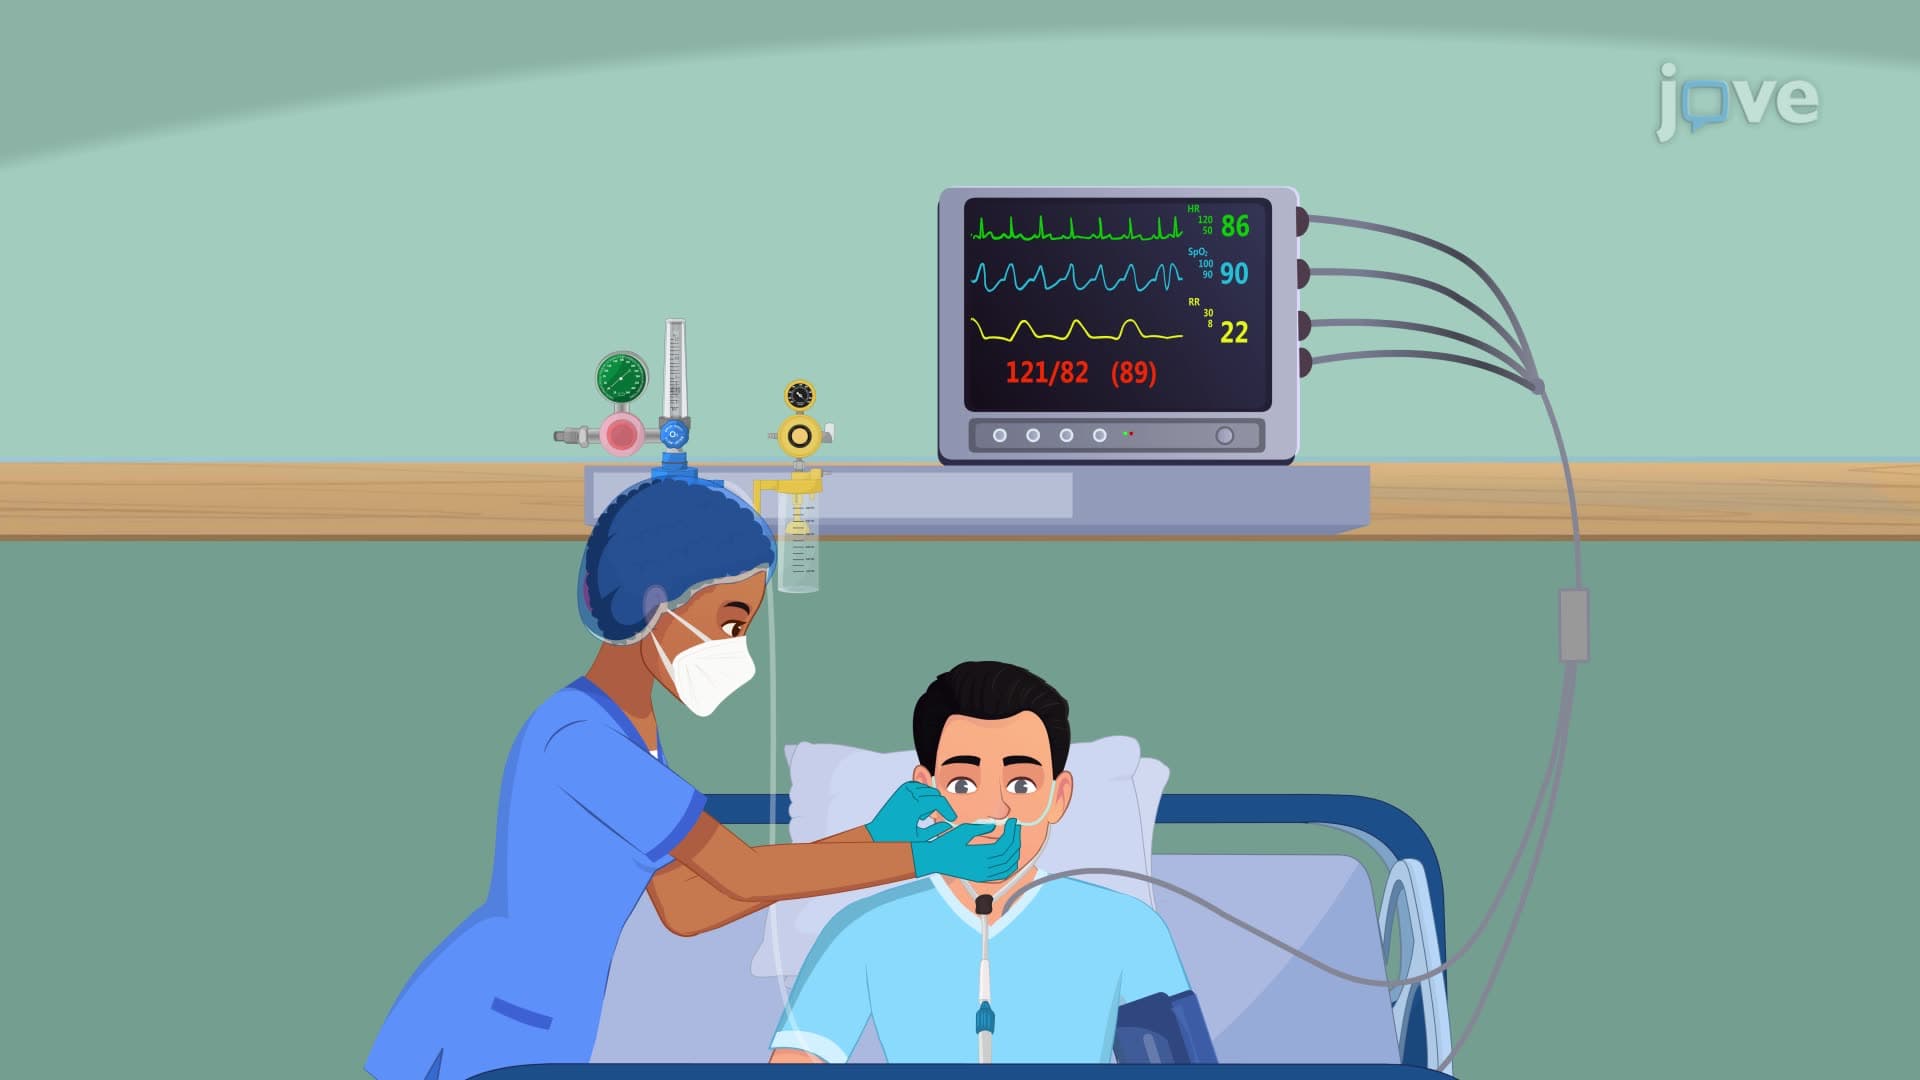
Administering Oxygen by Nasal Cannula
Nasal Cannulas
A nasal cannula is a lightweight tube split into two prongs placed in the nostrils,...
 01:30
Acute Respiratory Failure-III
 01:26
Oxygen Delivering System I: Nasal Cannula and Face Mask
Nasal Cannula
A nasal cannula is a lightweight tube split at one end into two prongs and placed in the nostrils. It is typically used to deliver low to medium levels of oxygen.
Suggested flow rate: The suggested flow rate for a nasal cannula typically ranges between 1 and 6 L/min.
Oxygen percentage setting:...
 01:24
Chronic Obstructive Pulmonary Disease III: Chronic Bronchitis Features