Related Experiment Video
Updated: Apr 25, 2026
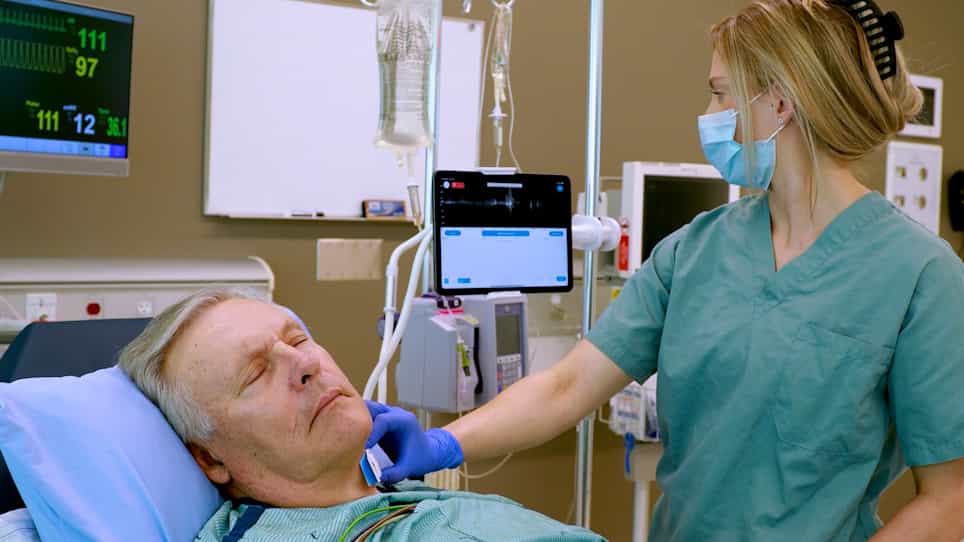

Continuous Venous-Arterial Doppler Ultrasound During a Preload Challenge
Published on: January 20, 2023
Use of preload responsiveness tests in pediatric intensive care units: A nationwide prospective clinical practice
Julien Gotchac1,2,3, Alice Lecomte3, Yaniss Belaroussi4
1Department of Pediatric and Congenital Cardiology, M3C National Reference Center, Bordeaux University Hospital, Bordeaux, France.

Insights
Preload-responsiveness tests are frequently used in pediatric intensive care units (PICU) but often misused. This study highlights the need for improved adherence to validity criteria for these crucial fluid responsiveness assessments.
Area of Science:
- Pediatric Intensive Care
- Critical Care Medicine
- Hemodynamics
Background:
- Fluid overload is a risk in pediatric intensive care units (PICU).
- Preload-responsiveness tests can guide fluid administration but have strict validity conditions.
- The actual use and misuse of these tests in PICU have not been previously evaluated.
Purpose of the Study:
- To assess the utilization of preload-responsiveness tests before volume expansion (VE) in PICU.
- To identify clinical factors associated with the use of these tests.
- To document the misuse of preload-responsiveness tests when validity criteria are not met.
Main Methods:
- A prospective, nationwide observational study was conducted in 34 French PICUs.
- Data on 471 volume expansions (VE) in children aged ≤15 years were collected.
- Physicians completed bedside questionnaires on test use and validity criteria were assessed.
Main Results:
- Preload-responsiveness tests were used before 62.8% of VE.
- Inferior vena cava visual analysis and respiratory variability of peak aortic velocity (ΔVPeak) were common tests.
- Misuse of tests was observed in 63.9% of cases, particularly with dynamic indices.
- Test use was associated with mechanical ventilation and catecholamine support.
Conclusions:
- Preload-responsiveness tests are routinely used in PICU, especially in severe patients.
- However, a significant proportion of these tests are either unreliable or misused.
- This underscores a critical gap in the appropriate application of fluid responsiveness assessments in pediatric critical care.
Background:
To avoid unnecessary volume expansions (VE), several preload-responsiveness tests exist in children but most have strict validity conditions, or are time-consuming. Although underuse or misuse of these tests could lead to inappropriate VE and fluid overload, their actual use in pediatric intensive care units (PICU) has never been evaluated. This study aimed to assess the use of preload-responsiveness tests before VE in PICU, identify clinical factors associated with their use, and document misuse when validity conditions, as defined in the literature, were not met.
Methods:
We conducted a prospective nationwide observational study in 34 French PICU. VE prescriptions to children ≤15 years were collected during a 6-week period. Exclusion criteria were preterm neonates, mechanical circulatory support, and single-ventricle physiology. For each VE, physicians completed a questionnaire at bedside, focusing on preload-responsiveness test use before VE. Relevant data to interpret tests validity were also collected, including spontaneous breathing and ventilation parameters. The use of preload-responsiveness test, their misuse and the characteristics associated with their use were analyzed. Misuse of a test was defined as its application when validity criteria were not met, regardless of the method used to perform the test which was not recorded.
Results:
A total of 471 VE were analyzed, prescribed to children with a median age of 7.9 months, on catecholamine support in 202/471 (42.9%) cases, and intubated in 292/471 (62.0%) cases. The median volume was 10 ml.kg-1. A preload-responsiveness test was performed before 296/471 (62.8%) VE (95%CI=[58.5%-67.2%]). Inferior vena cava visual analysis was the most common test, performed before 165 VE, followed by the respiratory variability of the peak aortic velocity (ΔVPeak), a dynamic index, measured before 92 VE. Among 294 dynamic indices (i.e., based on respiratory variation in hemodynamic signals) or preload challenges performed, misuse was observed in 188/294 (63.9%) cases. Performing a preload-responsiveness test was independently associated with mechanical ventilation (OR = 3.73, 95%CI=[1.95-7.15], p < 0.001) and catecholamine support (OR=4.08, 95%CI=[2.00-8.31], p < 0.001).
Conclusions:
In this large national prospective study, preload-responsiveness tests were routinely used before VE in PICU, especially in severe patients. However, the selected tests were often either poorly reliable or misused.
More Related Videos
 11:27
A Modified Sonographic Algorithm for Image Acquisition in Life-Threatening Emergencies in the Critically Ill Newborn
Published on: April 7, 2023
 06:04
Objective Nociceptive Assessment in Ventilated ICU Patients: A Feasibility Study Using Pupillometry and the Nociceptive Flexion Reflex
Published on: July 4, 2018
Related Concept Videos
 01:25
Pulmonary Function Tests
Pulmonary Function Tests are crucial diagnostic tools for assessing respiratory function, particularly in patients with chronic respiratory disorders. They comprehensively evaluate lung volumes, ventilatory function, breathing mechanics, diffusion, and gas exchange. These tests help diagnose pulmonary diseases and play a significant role in monitoring disease progression, evaluating disability, and assessing response to therapy.
PFTs involve using a spirometer, a...
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...