Related Experiment Video
Updated: Apr 25, 2026


Author Spotlight: Improving Percutaneous Vertebroplasty Surgical Accuracy and Efficiency Through Advanced Puncture Techniques
Published on: August 9, 2024
Biomechanical study of robot-navigated targeted cross-puncture percutaneous vertebroplasty for Kümmell's disease:
Haibin Zhou1,2, Chunjiu Gao1, Xiaoyuan Zhang1,2
1Department of Orthopedics, The Second Affiliated Hospital of Xuzhou Medical University, Xuzhou, China.

Objective:
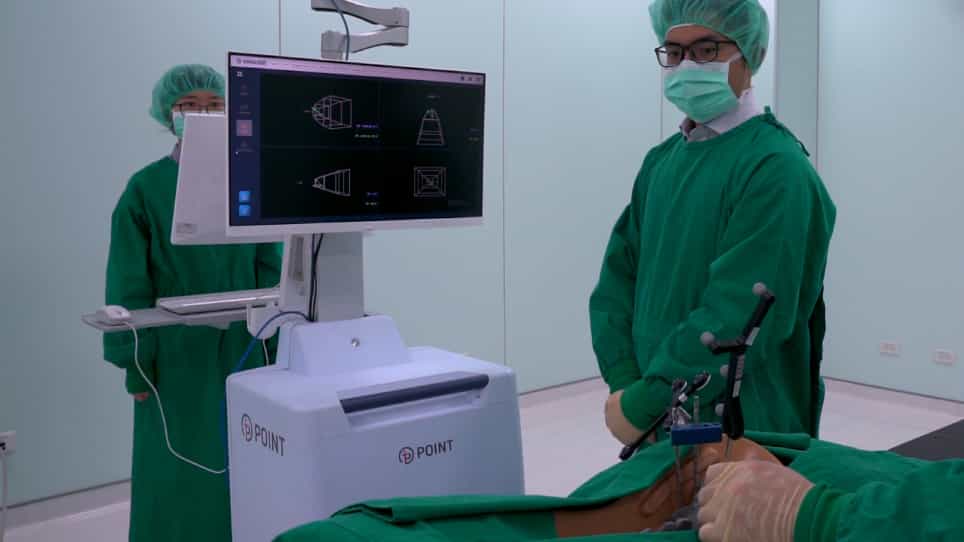
The objective of this study is to utilize finite element analysis (FEA) to compare the biomechanical advantages and disadvantages of bone cement distribution patterns during robot-navigated targeted cross-puncture percutaneous vertebroplasty (PVP) for osteoporotic vertebral compression fractures (OVCF) complicated by Kümmell's disease.
Method:
A patient-specific finite element model of the T12-L2 segment was developed from CT data to simulate L1 Kümmell's disease with an intravertebral vacuum cleft (IVC). The model simulated two surgical approaches: conventional percutaneous vertebroplasty (CPVP; cement filling was limited to the IVC) and robot-navigated targeted cross-puncture PVP (RPVP; incorporating a subjacent cancellous bone cement anchor). Material properties were assigned, and the lower surface of the L2 vertebral body was fully constrained to define the boundary conditions. Subsequently, six physiological loading conditions (flexion, extension, left/right lateral bending, and left/right axial rotation) were applied under a combined load of 500 N compressive preload and 7.5 N·m moment. Biomechanical outcomes included the von Mises stress distribution in the bone cement, vertebral body, and T12 inferior endplate, as well as the relative displacements.
Results:
Compared to CPVP, RPVP demonstrated superior biomechanical stability, evidenced by significantly reduced cement displacement and improved segmental stability in the T12-L2 functional spinal unit. RPVP also lowered peak vertebral stress in the vertebral body of L1, suggesting enhanced load distribution. A trade-off was observed: RPVP increased stress concentrations within the cement itself and at the T12 inferior endplate. Critically, lateral bending induced the greatest instability in both techniques, highlighting the necessity for postoperative movement restrictions in this plane.
Conclusion:
RPVP significantly reduces cement migration risk during Kümmell's disease treatment through optimized cement distribution. This biomechanical optimization establishes RPVP as a viable alternative to CPVP, enhancing surgical precision and stability while expanding clinical options for vertebral augmentation.