Related Experiment Video
Updated: Apr 25, 2026
Micropatterned Surfaces to Study Hyaluronic Acid Interactions with Cancer Cells
Published on: December 22, 2010
Transient Glycocalyx Remodeling by Intravenous Hyaluronidase in Atherosclerosis: A Hypothesis-Generating Review
Andreas Pfützner1,2,3, Tobias Gantner4, Harald Burgard5
1Pfützner Science & Health Institute, PSHI Praxis GmbH, Haifa-Alle 18, D-55128 Mainz, Germany.

Insights
Hyaluronidase may temporarily remodel the endothelial glycocalyx to aid reverse cholesterol transport (RCT) in atherosclerosis. However, evidence is limited, and risks like endothelial dysfunction are significant, requiring further research.
Area of Science:
- Cardiovascular Biology
- Vascular Biology
- Atherosclerosis Research
Background:
- Atherosclerosis is a leading global cause of death, driven by impaired cholesterol elimination via reverse cholesterol transport (RCT).
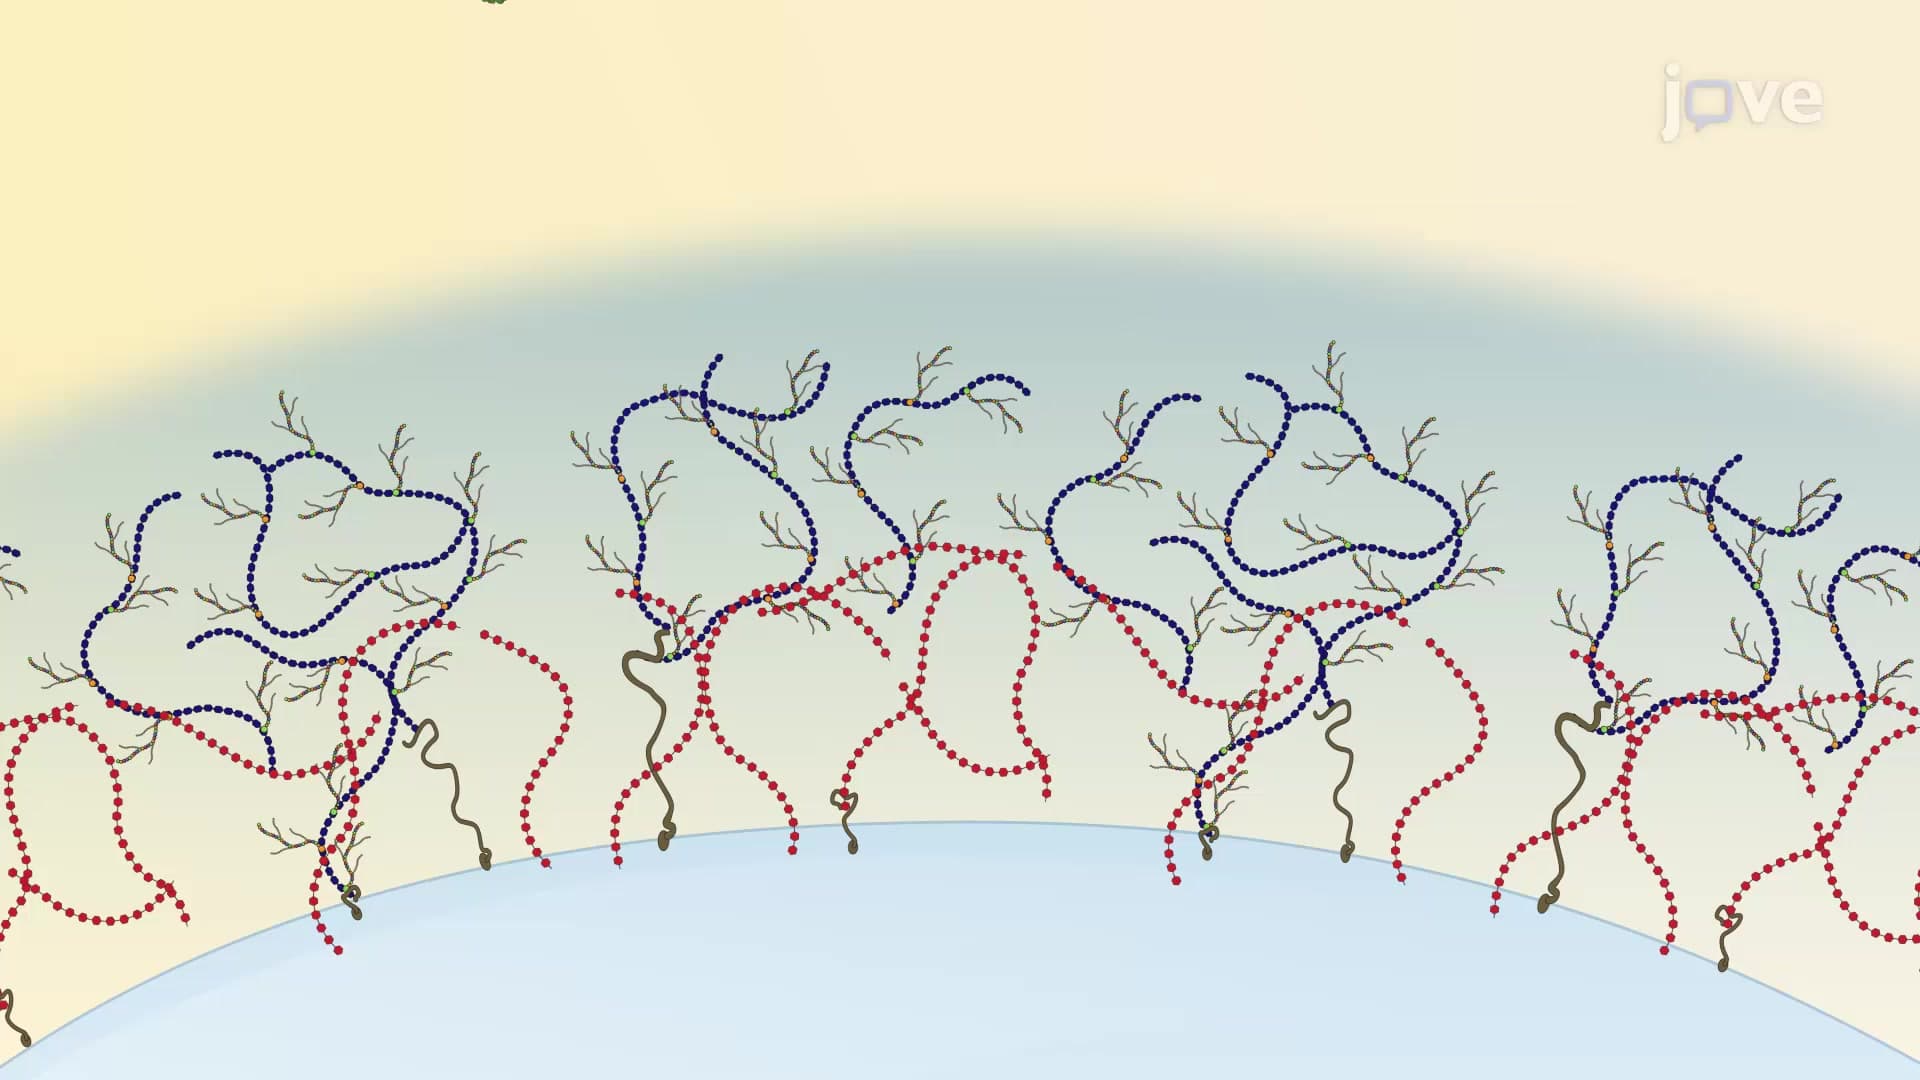
- The endothelial glycocalyx, a layer of proteoglycans and glycosaminoglycans, influences vascular barrier function and macromolecular transport.
- Alterations in glycocalyx structure during atherosclerosis may affect lipoprotein entry and cholesterol efflux pathways.
Purpose of the Study:
- To propose a mechanistic hypothesis for hyaluronidase's potential role in remodeling the glycocalyx to facilitate RCT.
- To critically evaluate the theoretical link between glycocalyx remodeling and enhanced cholesterol efflux from atherosclerotic lesions.
- To assess the current evidence, uncertainties, and risks associated with hyaluronidase therapy for atherosclerosis.
Main Methods:
- Mechanistic hypothesis generation.
- Literature review and synthesis of existing evidence on glycocalyx, RCT, and hyaluronidase.
- Evaluation of preclinical and clinical data, including pharmacokinetic and safety considerations.
Main Results:
- The hypothesis suggests transient hyaluronidase could remodel the glycocalyx, potentially improving RCT.
- Direct in vivo evidence linking glycocalyx as a barrier to RCT is limited.
- Hyaluronidase degradation is associated with endothelial dysfunction, inflammation, and thrombosis, potentially worsening atherosclerosis.
Conclusions:
- The proposed benefit of hyaluronidase on RCT via glycocalyx remodeling remains theoretical and lacks robust in vivo validation.
- Significant uncertainties and potential risks, including endothelial dysfunction and thrombosis, accompany hyaluronidase use.
- A translational research agenda focusing on mechanistic studies, biomarkers, imaging, and early-phase clinical trials is needed to clarify hyaluronidase's role in atherosclerosis.
Abstract:
Atherosclerosis remains the leading cause of death worldwide and imposes a major healthcare burden. Physiologically, elimination of cholesterol from the arterial wall depends on reverse cholesterol transport (RCT). RCT requires access to HDL and apolipoprotein A-I (ApoA-I) to lesional macrophages/foam cells. The endothelial glycocalyx is a dynamic and injury-sensitive layer of proteoglycans and glycosaminoglycans (including hyaluronan). It contributes to vascular barrier properties, leukocyte adhesion, mechanotransduction, and macromolecular transport. In atherosclerosis, glycocalyx structure and function are altered; this may facilitate entry/retention of atherogenic lipoproteins and may also alter transport conditions relevant to cholesterol efflux pathways. This article presents a mechanistic hypothesis: short, transient, systemic hyaluronidase exposure could temporarily remodel glycocalyx/extracellular matrix components and thereby facilitate conditions permissive for regulated transport processes relevant to RCT. However, the proposed link between glycocalyx remodeling and improved lesional cholesterol efflux remains theoretical. Direct in vivo evidence that the endothelial glycocalyx is a dominant barrier limiting HDL- or ApoA-I-mediated cholesterol efflux from plaque macrophages is currently limited. Moreover, glycocalyx degradation is widely associated with endothelial dysfunction, increased permeability, inflammation, and thrombosis, all of which could aggravate rather than ameliorate atherosclerosis. Human pharmacokinetic data indicate a very short plasma half-life of circulating hyaluronidase activity, suggesting that any systemic enzymatic effect is brief. Nevertheless, the biological consequences of repeated degradation-regeneration cycles, especially in high-risk states such as diabetes, inflammation, oxidative stress, or chronic kidney disease, remain incompletely understood. Evidence supporting clinical benefit in atherosclerosis is currently limited to heterogeneous animal experiments, historical uncontrolled reports, and a small number of anecdotal case observations, whereas randomized trials have only been performed in other settings such as acute myocardial infarction and do not establish efficacy for plaque regression. We therefore provide a balanced evaluation of knowns, uncertainties, alternative interpretations, potential risks, dosing unknowns, and a translational research agenda including mechanistic preclinical studies, biomarker development, imaging, and carefully designed early-phase clinical investigation.

Related Concept Videos
 01:14
Glycocalyx and its Functions
 01:16
Clot Retraction and Fibrinolysis
 01:30
Atherosclerosis I: Introduction
 01:16
Vascular Spasm
 01:26
Coronary Artery Disease II: Pathophysiology
 01:26
Atherosclerosis III: Management