Related Experiment Video
Updated: May 1, 2026
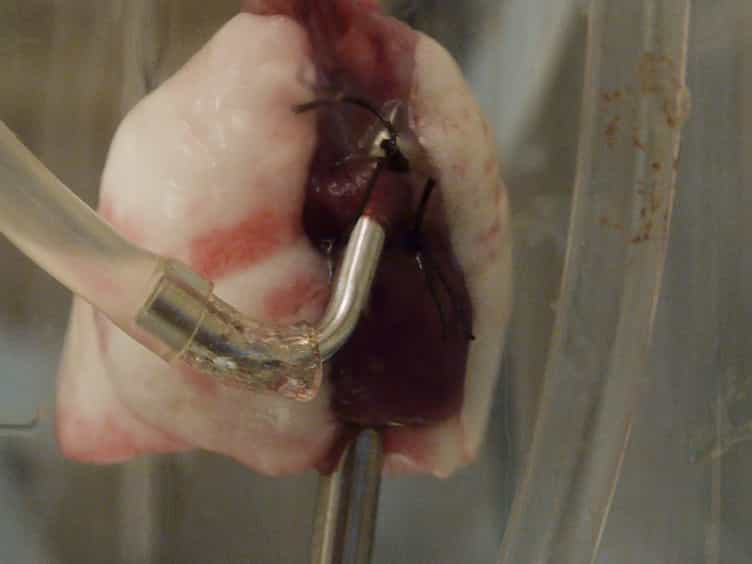

Method of Isolated Ex Vivo Lung Perfusion in a Rat Model: Lessons Learned from Developing a Rat EVLP Program
Published on: February 25, 2015
FILONEX - A prospective, randomized controlled pilot safety study evaluating the addition of hemodiafiltration to
Panja M Boehm1, Sophia Auner1, Oya Berezhinskiy1
1Department of Thoracic Surgery, Medical University of Vienna, Vienna, Austria.

Background:
The lack of physiologic clearance mechanisms during ex vivo lung perfusion (EVLP) may lead to electrolyte imbalances, accumulation of toxic metabolites and disturbances in starling forces. The integration of dialysis may help to maintain perfusate physiology. The FILONEX trial investigates the feasibility and safety of this strategy.
Methods:
This single-center prospective randomized controlled study included 30 marginal donor lungs randomized 1:1 at procurement. Normothermic acellular EVLP was performed for six hours. After one hour, hemodiafiltration (HDF) was added to the EVLP circuit in the treatment group, whereas the control group received EVLP without any adjunct therapy. Primary endpoints were suitability for transplantation after EVLP, and primary graft dysfunction (PGD) grade 3 at 72 h after transplantation.
Results:
Donor and recipient characteristics were similar between the groups. Electrolyte levels, lactate and pH remained within physiological ranges only in the treatment group. Acceptance rate was 47% (n=7) in the control and 80% (n=12) in the treatment group. PGD grade 3 at ICU admission was 57% (n=4) in the control and 25% (n=3) in the treatment group (p=0.093). There were no cases of PGD grade 3 at 72 h in either group. In 3 (43%) control patients, VA-ECMO was prolonged postoperatively compared to 1 (8%) patient in the treatment group (p=0.075). Length of mechanical ventilation, ICU stay, hospital stay and short-term mortality were comparable among the groups.
Conclusion:
This prospective randomized trial demonstrates that integrating HDF into the EVLP circuit is feasible and safe during six hours of perfusion, without adverse effects on EVLP performance or short-term outcomes after lung transplantation.


