Related Experiment Video
Updated: Apr 26, 2026
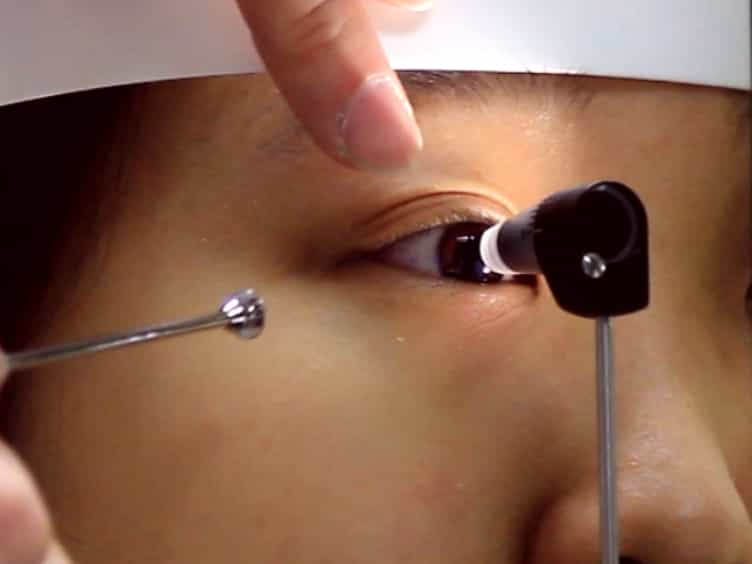

Trabecular Meshwork Response to Pressure Elevation in the Living Human Eye
Published on: June 20, 2015
Intraocular Pressure Fluctuations and the Role of the Valsalva Maneuver in Young Professional Musicians
Veronica Noya-Padin1, Filipe Da Silva2, Ângelo Martingo3
1GI-2092 Optometry, Department of Applied Physics (Optometry Area), Faculty of Optics and Optometry, University of Santiago de Compostela, Santiago de Compostela, Spain; Health Research Institute of Santiago de Compostela (IDIS), Santiago de Compostela, Spain.

Purpose:
(1) To determine whether intraocular pressure (IOP) fluctuations while playing musical instruments is specific to the instrument type; (2) to investigate the role of the Valsalva maneuver as an underlying mechanism; and (3) to evaluate relationships between IOP values and demographic and environmental factors.
Design:
Cross-sectional study.
Participants:
Sixty-five musicians were enrolled. Of these, 2 were excluded due to glaucoma history and intolerance to IOP measurements. The final sample consisted of 63 young professional musicians (34 wind instrumentalists and 29 nonwind instrumentalists).
Methods:
Participants underwent tonometry (iCare IC100) and otoscopy (Dino-Lite Basic EarScope) and completed a self-administered questionnaire on demographic and environmental factors. Tonometry and otoscopy procedures were performed simultaneously at 4 time points: before playing, while playing a low-pitched note and a high-pitched note, and after playing.
Main Outcome Measures:
Intraocular pressure and tympanic membrane movement.
Results:
No differences in IOP were observed between wind and nonwind instrumentalists at baseline, during low-pitch playing, or after playing (Mann-Whitney U test, all P ≥ 0.052). However, IOP differed while high-pitch playing (Mann-Whitney U test, P = 0.007), with both high- and low-resistance wind instrumentalists showing higher IOP than nonwind instrumentalists (Mann-Whitney U test, both P ≤ 0.041). Intraocular pressure change relative to baseline (ΔIOP) similarly revealed differences during high-pitch playing and additionally detected differences during low-pitch playing (Mann-Whitney U test, both P ≤ 0.025). Within the wind category, no differences in IOP were found between high- and low-resistance (Mann-Whitney U test, all P ≥ 0.323), and the same pattern was observed for ΔIOP (Mann-Whitney U test, all P ≥ 0.112). The Valsalva maneuver was not detected for any instrument or under any measurement conditions. In addition, no relationships were found with demographic or environmental factors and IOP fluctuations (Pearson's or Spearman's correlation, all P ≥ 0.273), although baseline IOP positively correlated with age at which wind instrumentalists began playing their instrument (Pearson's correlation, r = 0.348, P = 0.048).
Conclusions:
Intraocular pressure fluctuations during musical instrument performance occur specifically in wind instrumentalists (both low- and high-resistance), and are not due to involuntary Valsalva maneuvers during playing. Moreover, basal IOP correlated with age of instrument debut in wind instrumentalists, whereas no other demographic or environmental factors related to IOP measurements or its fluctuations.
Financial Disclosure(S):
The author(s) have no proprietary or commercial interest in any materials discussed in this article.
More Related Videos
 14:28
Software for Analysis of Heart Rate and Blood Pressure Time-series Data from the Valsalva Maneuver
Published on: June 27, 2025
 08:55
Translaminar Autonomous System Model for the Modulation of Intraocular and Intracranial Pressure in Human Donor Posterior Segments
Published on: April 24, 2020
Related Concept Videos
 01:27
Open Angle Glaucoma: Treatment
Drugs such as carbonic anhydrase inhibitors, α2- and...
 01:25
Glaucoma: Overview
 01:29
Increased Intracranial Pressure ll: Pathophysiology
 01:14
Increased Intracranial Pressure l: Introduction
 01:28
Angle Closure Glaucoma: Treatment
 01:28
Special considerations while measuring blood pressure
Monitoring Both Arms:
Monitoring BP in both arms during the initial assessment is advisable, as the systolic value may differ by five to ten mm Hg between arms. For subsequent BP assessments, use the arm with the higher reading.