Related Experiment Video
Updated: Apr 26, 2026
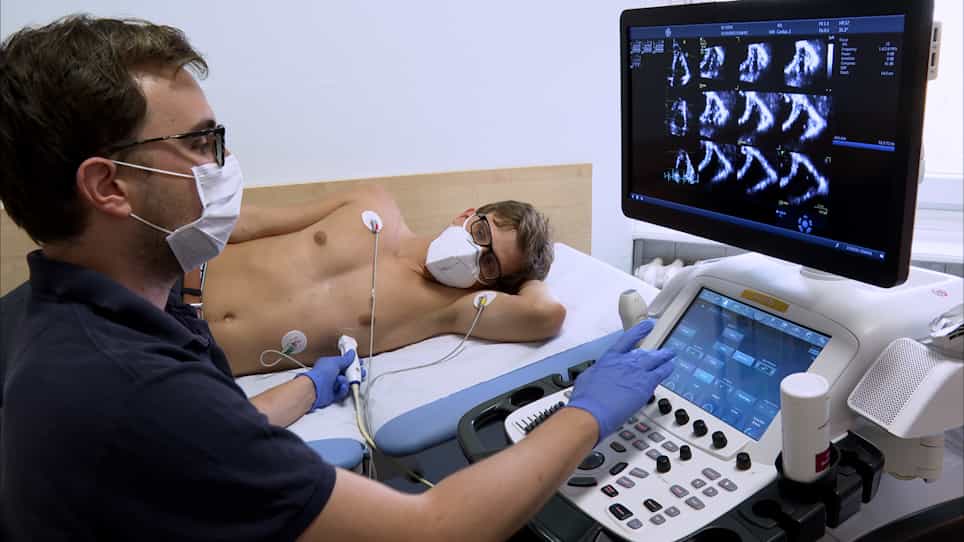

Morphological and Functional Assessment of the Right Ventricle Using 3D Echocardiography
Published on: October 28, 2020
Why TAPSE and FAC fall short: RVEF remains the gold standard for assessing RV function after cardiac surgery in
Oceane Zanchiello1, Milan Prsa2,3
1University of Lausanne, Lausanne, Switzerland.

Insights
Tricuspid annular plane systolic excursion (TAPSE) and right ventricular (RV) fractional area change (FAC) are unreliable for assessing RV systolic function in children after heart surgery. True RV systolic function is best evaluated by RV ejection fraction (RVEF) using cardiac MRI.
Area of Science:
- Pediatric Cardiology
- Cardiovascular Imaging
- Cardiac Surgery
Background:
- Tricuspid annular plane systolic excursion (TAPSE) and right ventricular (RV) fractional area change (FAC) are common surrogates for RV systolic function.
- Their accuracy in pediatric patients post-pericardiotomy is uncertain.
Purpose of the Study:
- To assess the validity of TAPSE and FAC as markers of global RV systolic function in pediatric patients with and without prior pericardiotomy.
Main Methods:
- Retrospective analysis of 120 pediatric patients undergoing cardiac MRI.
- Patients categorized into post-pericardiotomy (n=85) and no prior surgery (n=35) groups.
- Measured TAPSE z-scores, RV FAC, and RV ejection fraction (RVEF); performed correlation analyses.
Main Results:
- Post-pericardiotomy group: Decreased TAPSE z-score, no correlation with RVEF; preserved RV FAC with weak RVEF correlation.
- No prior surgery group: Normal TAPSE z-score with weak RVEF correlation; moderate RV FAC-RVEF correlation.
- No significant differences in correlation strengths between groups.
Conclusions:
- TAPSE and RV FAC demonstrate limited reliability for assessing RV systolic function in pediatric patients, particularly after pericardiotomy.
- RV ejection fraction (RVEF) derived from cardiac MRI is the recommended measure for true RV systolic function post-pediatric cardiac surgery.
Background:
Tricuspid annular plane systolic excursion (TAPSE) and right ventricular (RV) fractional area change (FAC) are often used as surrogate measurements of RV systolic function. However, their reliability in children following cardiac surgery involving pericardiotomy remains unclear. The goal of this study was to evaluate whether TAPSE and FAC are valid surrogate markers of global RV systolic function in paediatric patients with and without prior pericardiotomy.
Methods:
We retrospectively analysed 120 paediatric patients who underwent ferumoxytol-enhanced, motion-resolved five-dimensional whole-heart cardiac MRI between 2020 and 2024. Patients were divided into two groups: those who had previous pericardiotomy (n=85) and those who had no previous surgery (n=35). TAPSE z-scores, RV FAC and RV ejection fraction (RVEF) were measured and compared between the two groups and correlation analyses were performed.
Results:
In the post-pericardiotomy group, TAPSE z-score was significantly decreased (-5.32±2) and did not correlate with RVEF (r=0.04), while RV FAC was preserved (41.3%) but correlated only weakly with RVEF (r=0.39). In patients without previous cardiac surgery, TAPSE z-score was within the normal range (0.17±1.48) but demonstrated a weak correlation with RVEF (r=0.28), while RV FAC was moderately correlated with RVEF (r=0.57). Differences in the correlation strengths between the two groups were not statistically significant.
Conclusions:
TAPSE and RV FAC showed limited reliability as surrogate markers of global RV systolic function in paediatric patients especially following surgery involving pericardiotomy. Only RVEF, measured by cardiac MRI, should be used to evaluate true RV systolic function after paediatric cardiac surgery.
More Related Videos
 09:40
Induction of Right Ventricular Failure by Pulmonary Artery Constriction and Evaluation of Right Ventricular Function in Mice
Published on: May 13, 2019
 06:04
Author Spotlight: Establishment and Confirmation of a Postnatal Right Ventricular Volume Overload Mouse Model
Published on: June 9, 2023
Related Concept Videos
 01:21
Cardiac Catheterization II: Right Heart Catheterization
 01:28
Cardiomyopathy VII: Pre and Post Operative Nursing Management