Related Experiment Video
Updated: Apr 27, 2026

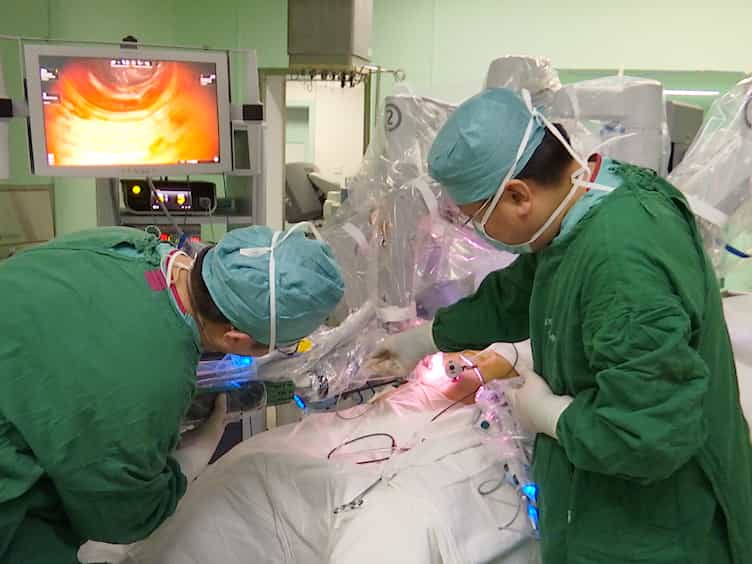
Treatment of Middle-segment Pancreatic Benign Tumor Using Laparoscopic Central Pancreatectomy with End-to-end Pancreatic Duct Reconstruction
Published on: January 2, 2026
Hypervascular solid-appearing serous cystadenoma as a mimic of nonfunctioning pancreatic neuroendocrine tumour: a
Mario Annecchiarico1, Giuseppe Loiaco2,3, Giulio Argenio1
1General and Oncological Surgery Unit, AORN "San Pio", 82100, Benevento, Italy.

Background:
Solid pancreatic serous cystadenoma (SCA) may present as a hypervascular mass and mimic nonfunctioning pancreatic neuroendocrine tumour (NF-pNET), potentially leading to pancreatic resection for benign disease. We synthesized the available evidence on this diagnostic pitfall.
Methods:
A PRISMA 2020-aligned systematic review searched MEDLINE, Embase, and Web of Science (1 January 2000-1 December 2025). We included comparative cohorts of pathology-proven SCA versus NF-pNET reporting CT/MRI discriminative features and case reports/series of pathology-proven SCA preoperatively interpreted as NF-pNET. Comparative cohorts and case reports/series were synthesized separately; no meta-analysis was performed.
Results:
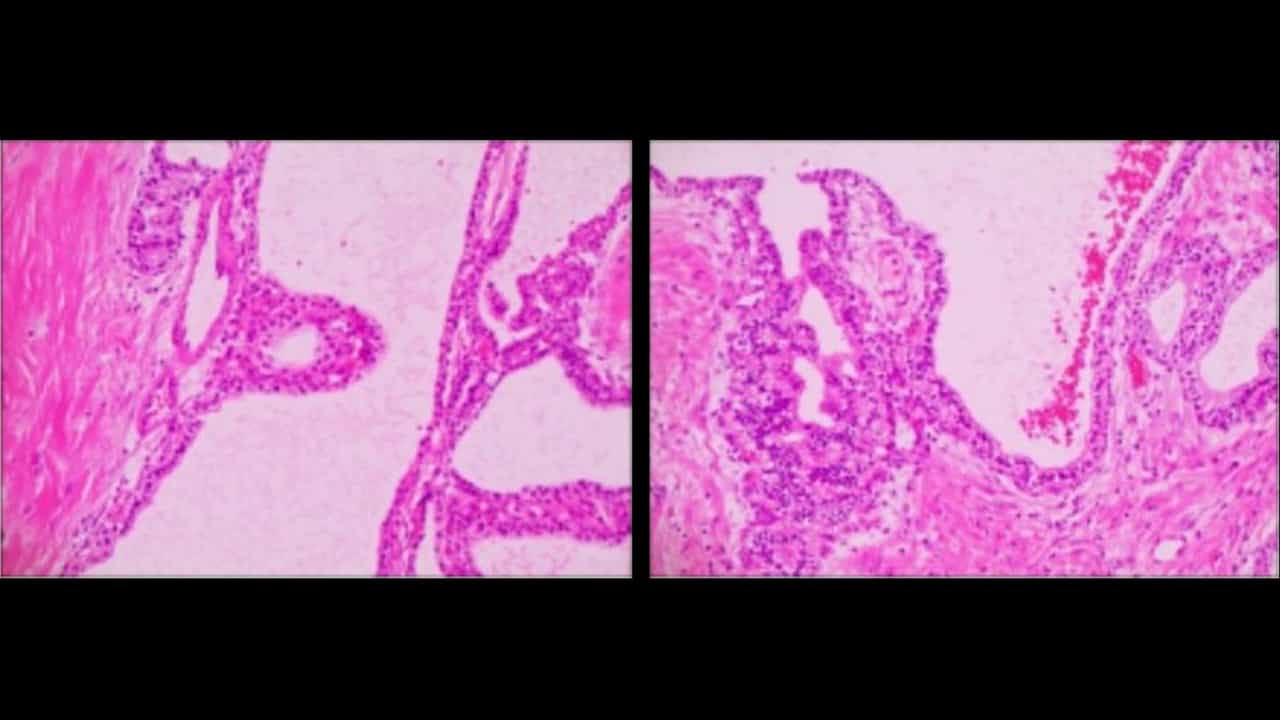
Thirty-five publications were included: four retrospective single-center comparative cohorts (50 SCA and 89 NF-pNET patients) and 31 case reports/series (39 SCA patients). In comparative cohorts, unenhanced CT attenuation was consistently lower in SCA than in NF-pNET (18.5-29.6 vs. 38.8-48.4 HU), with study-specific ROC-derived cutoffs in the low 30-HU range; attenuation ratios performed similarly. Diffusion-weighted MRI showed higher ADC values in SCA, with reported study-specific cutoffs of > 1.36 × 10- 3 mm2/s and > 1.99 × 10- 3 mm2/s. In case reports/series, arterial hyperenhancement occurred in 32/33 (97.0%), 68Ga-DOTA-peptide uptake in 17/39 (43.6%), and EUS-guided sampling was diagnostic in 9/17 (52.9%).
Conclusions:
NF-pNET-mimicking SCA is an uncommon but clinically consequential benign mimic. In the available retrospective comparative cohorts of resected, pathology-proven lesions, lower unenhanced CT attenuation (and attenuation ratios) and higher DWI-ADC values consistently favored SCA over NF-pNET, whereas arterial hyperenhancement and positive somatostatin receptor imaging uptake were not specific. These findings may support cautious multiparametric assessment in selected hypervascular solid-appearing pancreatic lesions, but should not be applied as definitive diagnostic thresholds without external validation.