Related Experiment Video
Updated: Apr 27, 2026
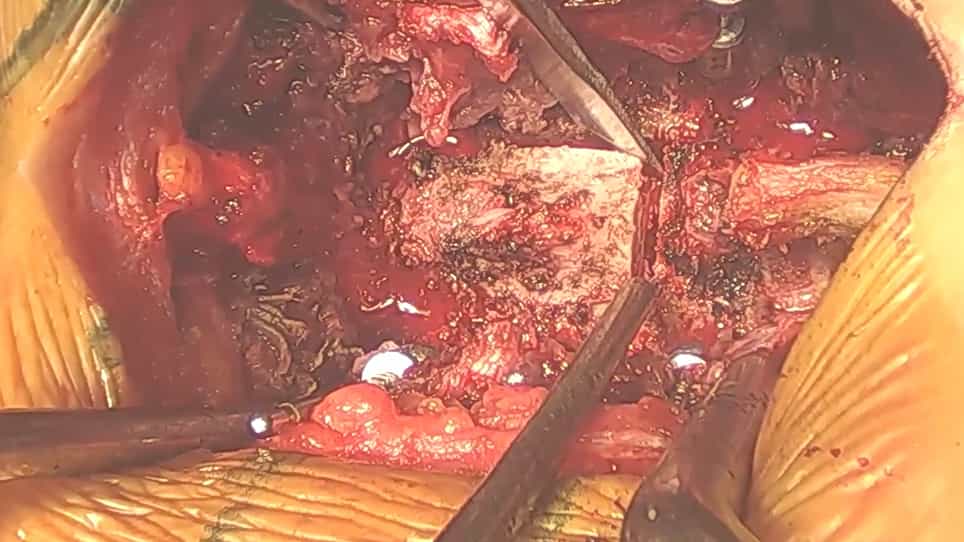

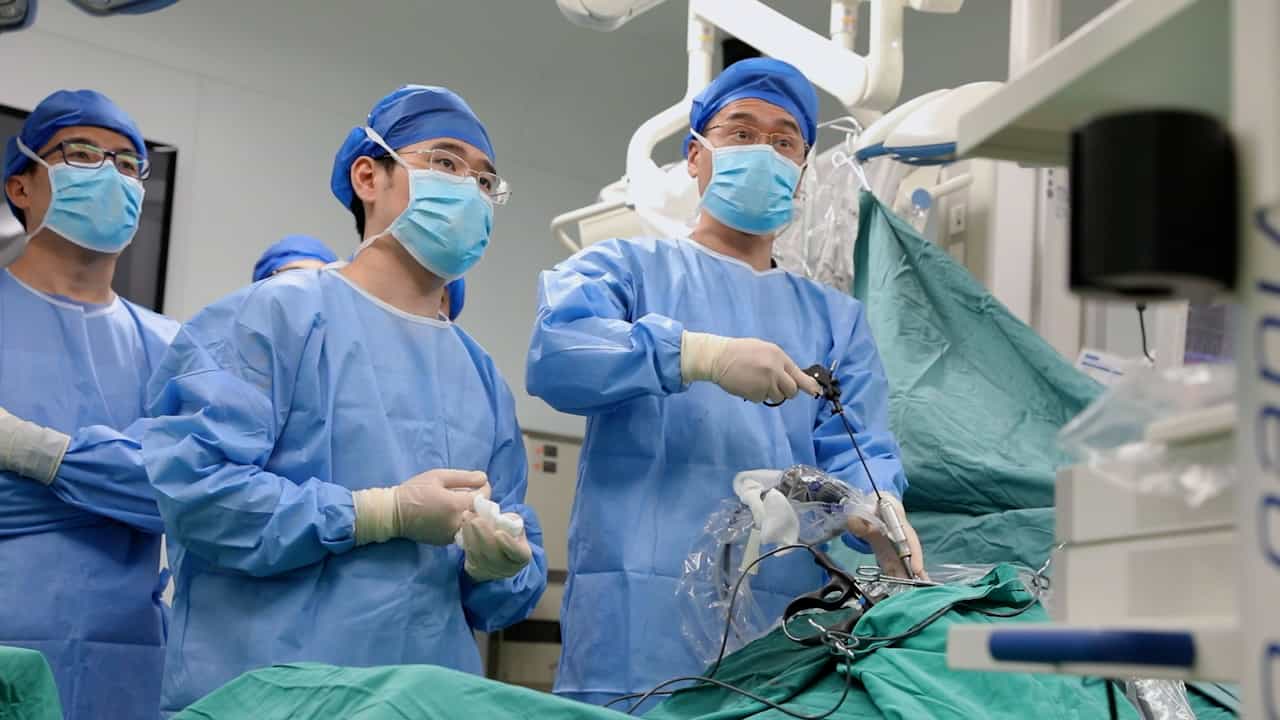
Laminectomy for the Removal of Thoracic Ossification of the Ligamentum Flavum TOLF Using Ultrasonic and Conventional Osteotomes
Published on: April 21, 2023
Percutaneous spinal endoscopic surgery for thoracic ossification of the posterior longitudinal ligament: a noval
Xingchen Li1, Luyang Wang1, Yiping Zheng1
1Department of Orthopedics, The First Affiliated Hospital of Zhengzhou University, Zhengzhou, China.

Objective:
To investigate the feasibility and clinical efficacy of bilateral crossover decompression technique under percutaneous spinal endoscopic surgery for thoracic ossification of the posterior longitudinal ligament (T-OPLL).
Methods:
A retrospective analysis was conducted on 18 patients with T-OPLL who underwent bilateral crossover percutaneous spinal endoscopic surgery between January 2020 and December 2023. There were 10 males and 8 females, with a mean age of 54.8 years. Surgical levels included T6/7 (4 cases), T7/8 (3 cases), T8/9 (4 cases), T9/10 (2 cases), T10/11 (2 cases), T11/12 (1 cases), and T12/L1 (2 cases). Total operative time, intraoperative blood loss, length of hospital stay, and complications were recorded. Neurological function was evaluated using the modified Japanese Orthopaedic Association (mJOA) score and the Oswestry Disability Index (ODI) preoperatively, at 3 days and 6 months postoperatively, and at the final follow-up. Clinical efficacy at the last follow-up was assessed using the modified MacNab criteria, and the excellent-to-good rate was calculated. Sagittal canal diameter and canal area were measured to evaluate spinal cord decompression.
Results:
The mean total operative time was 102.39 min (range: 90-130 min), intraoperative blood loss was 40.61 ml (range: 30-55 ml), and mean hospital stay was 10.22 days (range: 8-14 days). All patients were followed up for a mean duration of 16.78 months (range: 12-24 months). Compared with the preoperative period, mJOA scores significantly improved at 3 days, 6 months, and at the final follow-up (p < 0.05), with further improvement observed at the final follow-up compared with 3 days and 6 months postoperatively (p < 0.05). Similarly, ODI scores were significantly reduced at 3 days, 6 months, and at the final follow-up compared with preoperative scores (p < 0.05). According to the modified MacNab criteria at the final follow-up, 9 cases were rated as excellent, 7 as good, and 2 as fair, yielding an excellent-to-good rate of 88.89%. Compared with preoperative measurements, both the sagittal canal diameter and canal area were significantly increased at 3 days, 6 months, and at the final follow-up (p < 0.05). Complications included intercostal neuralgia in 2 patients, dural tear in 2 patients, and transient postoperative muscle weakness in 1 patient; no cases of epidural hematoma, neck pain, or iatrogenic neurological injury were observed.
Conclusion:
Bilateral crossover decompression percutaneous spinal endoscopic surgery is a safe and effective minimally invasive technique for the treatment of T-OPLL, with satisfactory short-term clinical outcomes.