Related Experiment Video
Updated: Apr 28, 2026

Handwriting Analysis Indicates Spontaneous Dyskinesias in Neuroleptic Naïve Adolescents at High Risk for Psychosis
Published on: November 21, 2013
Clinical features and genetic analysis of paroxysmal kinesigenic dyskinesia in children
Li-Ping Zheng1,2, Yun-Peng Ye1, Su-Ping Wang1
1Fujian Medical University Union Hospital, Fuzhou, China.

Insights
This study details clinical features and genetic variations in pediatric paroxysmal kinesigenic dyskinesia (PKD). PRRT2 and KCNMA1 gene mutations were identified, with carbamazepine and oxcarbazepine proving effective treatments.
Area of Science:
- Neurology
- Genetics
- Pediatrics
Background:
- Paroxysmal kinesigenic dyskinesia (PKD) is a rare movement disorder characterized by brief, recurrent episodes of involuntary movements.
- Understanding the clinical spectrum and genetic underpinnings of pediatric PKD is crucial for accurate diagnosis and management.
Purpose of the Study:
- To summarize the clinical features and genetic variation spectrum of children with PKD.
- To provide references for clinical diagnosis and genetic counseling in pediatric PKD cases.
Main Methods:
- Retrospective analysis of clinical data from 6 pediatric PKD patients.
- Whole-exome sequencing (WES) for gene mutation detection, followed by Sanger sequencing.
- Pathogenicity assessment of variants according to ACMG guidelines.
Main Results:
- Six pediatric patients (5 male, 1 female; onset 5-12 years) were analyzed.
- Five patients had PRRT2 mutations (point mutations or exon deletions), and one had a KCNMA1 mutation.
- Carbamazepine or oxcarbazepine effectively controlled dyskinetic attacks in all treated patients.
Conclusions:
- Pediatric PKD presents with typical paroxysmal features, primarily linked to PRRT2 gene mutations, but KCNMA1 mutations are also implicated.
- Carbamazepine and oxcarbazepine are effective treatments for childhood PKD.
- Genetic testing is essential for definitive diagnosis and genetic subtyping.
Objective:
To summarize the clinical features and genetic variation spectrum of children with paroxysmal kinesigenic dyskinesia (PKD) admitted to the Children's Medical Center of Union Hospital Affiliated to Fujian Medical University and to provide references for clinical diagnosis and genetic counseling.
Methods:
A retrospective analysis was conducted on the clinical data of 6 pediatric patients diagnosed with PKD in our hospital from November 2018 to August 2025. The data included medical history, triggering factors, clinical manifestations, auxiliary examinations, and treatment responses. Whole-exome sequencing (WES) was employed to detect gene mutations, followed by Sanger sequencing for verification. The pathogenicity of the identified variants was assessed according to the guidelines of the American College of Medical Genetics and Genomics (ACMG).
Results:
The study cohort included 5 males and 1 female, with an age of onset ranging from 5 to 12 years. Two cases were familial, while four were sporadic. All paroxysmal episodes were induced by sudden movement, postural change, or anxiety. The clinical manifestations included unilateral or bilateral limb posturing, tremor, athetosis, dystonia, and weakness, without impairment of consciousness. The attacks were brief (duration ≤50 s) and occurred with a frequency ranging from 1-2 per month to 5-6 per day. A history of febrile seizures was present in three patients. The magnetic resonance imaging (MRI) scan of the brain of one child showed a lacune in the right frontal lobe, and video electroencephalogram (VEEG) of another child revealed abnormal epileptic discharges during the interictal period. Genetic analysis via whole-exome sequencing (WES) identified pathogenic variants in all six patients: five harbored PRRT2 mutations (including point mutations c.649dupC, c.972delA, and c.1141delC, or exon deletions), and one had a KCNMA1 mutation (c.946G>A). Regarding treatment, four patients administered low-dose carbamazepine and two received low-dose oxcarbazepine, all of whom achieved complete or substantial control of the dyskinetic attacks.
Conclusion:
The clinical features of pediatric PKD align with typical paroxysmal manifestations. The PRRT2 gene is the primary pathogenic gene, although cases associated with KCNMA1 mutations were also identified. Both carbamazepine and oxcarbazepine demonstrated efficacy in treating childhood PKD. Genetic testing facilitates definitive diagnosis and genetic subtyping.
More Related Videos
 10:41
Implantation of Osmotic Pumps and Induction of Stress to Establish a Symptomatic, Pharmacological Mouse Model for DYT/PARK-ATP1A3 Dystonia
Published on: September 12, 2020
 05:32
High-speed Video Microscopy Analysis for First-line Diagnosis of Primary Ciliary Dyskinesia
Published on: January 19, 2022
Related Concept Videos
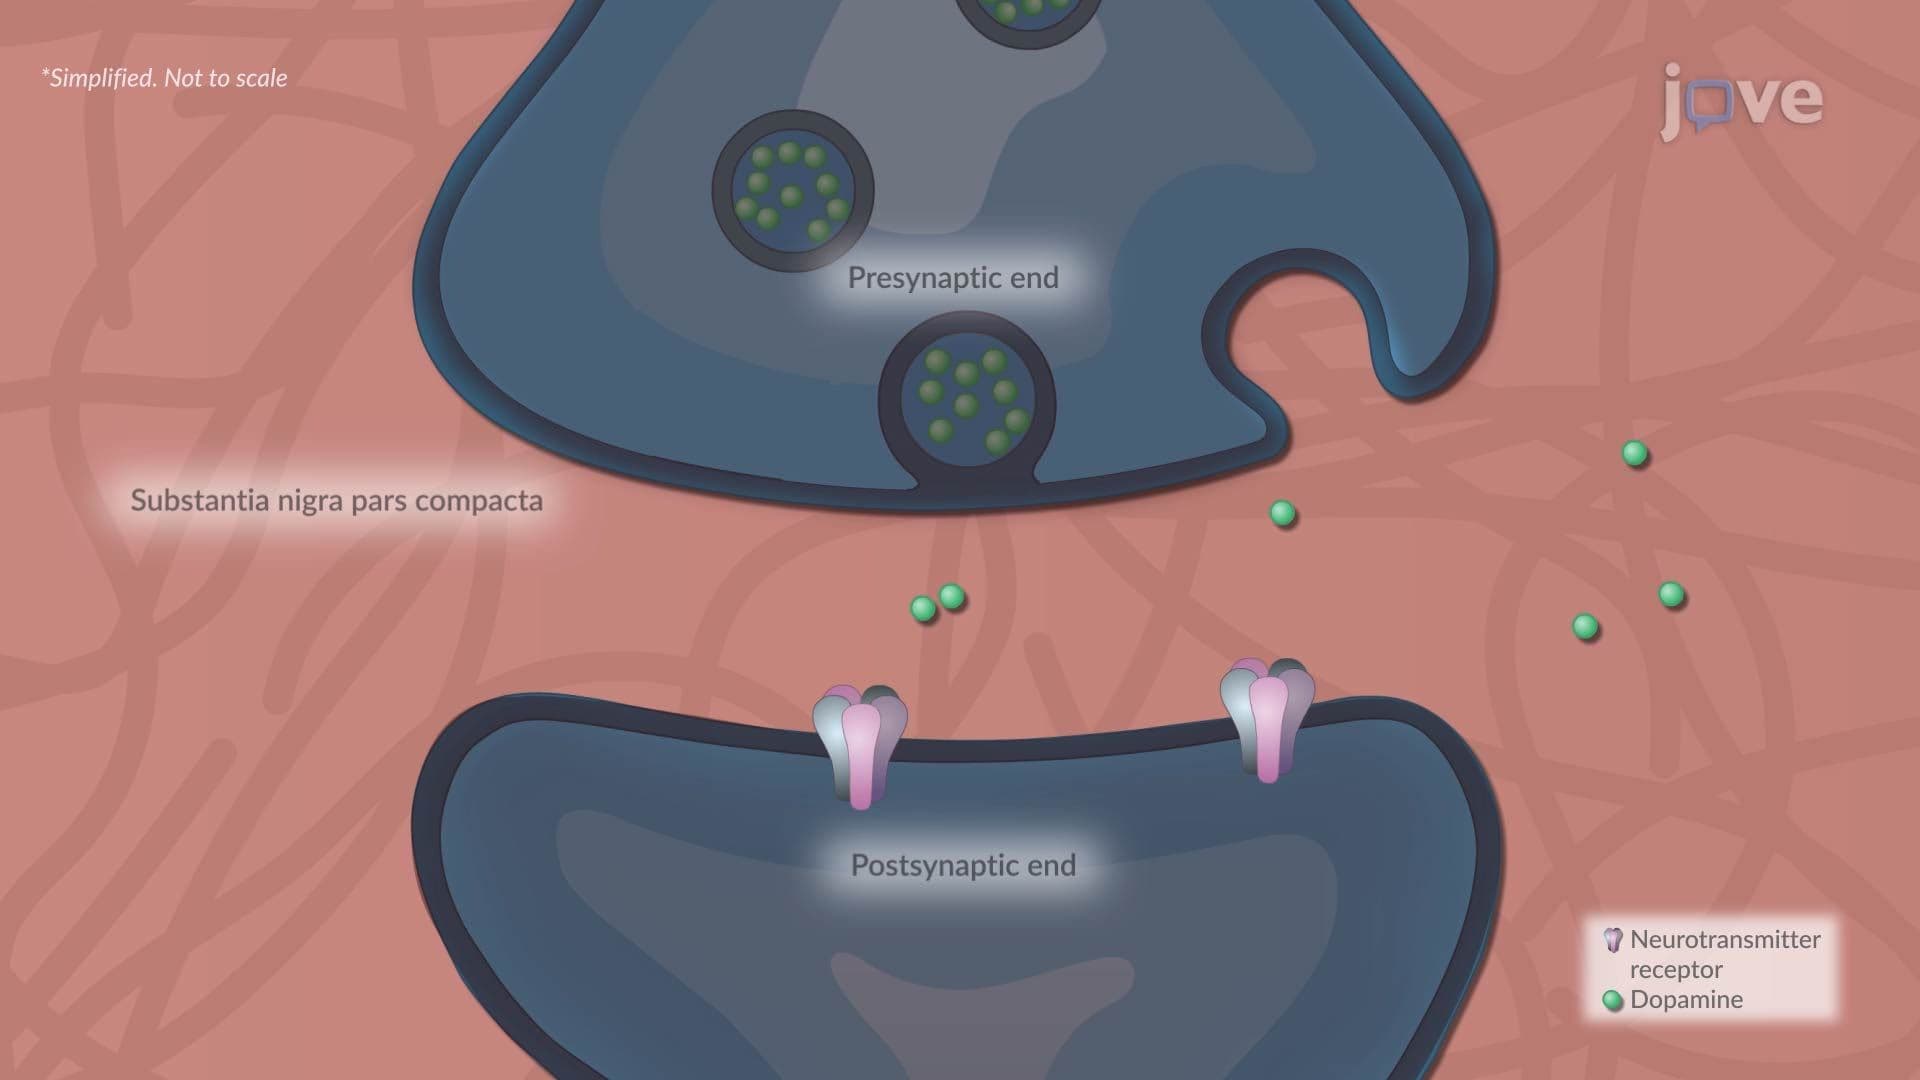 01:24
Parkinson Disease l: Introduction
 01:12
Alterations in Muscle Tone ll
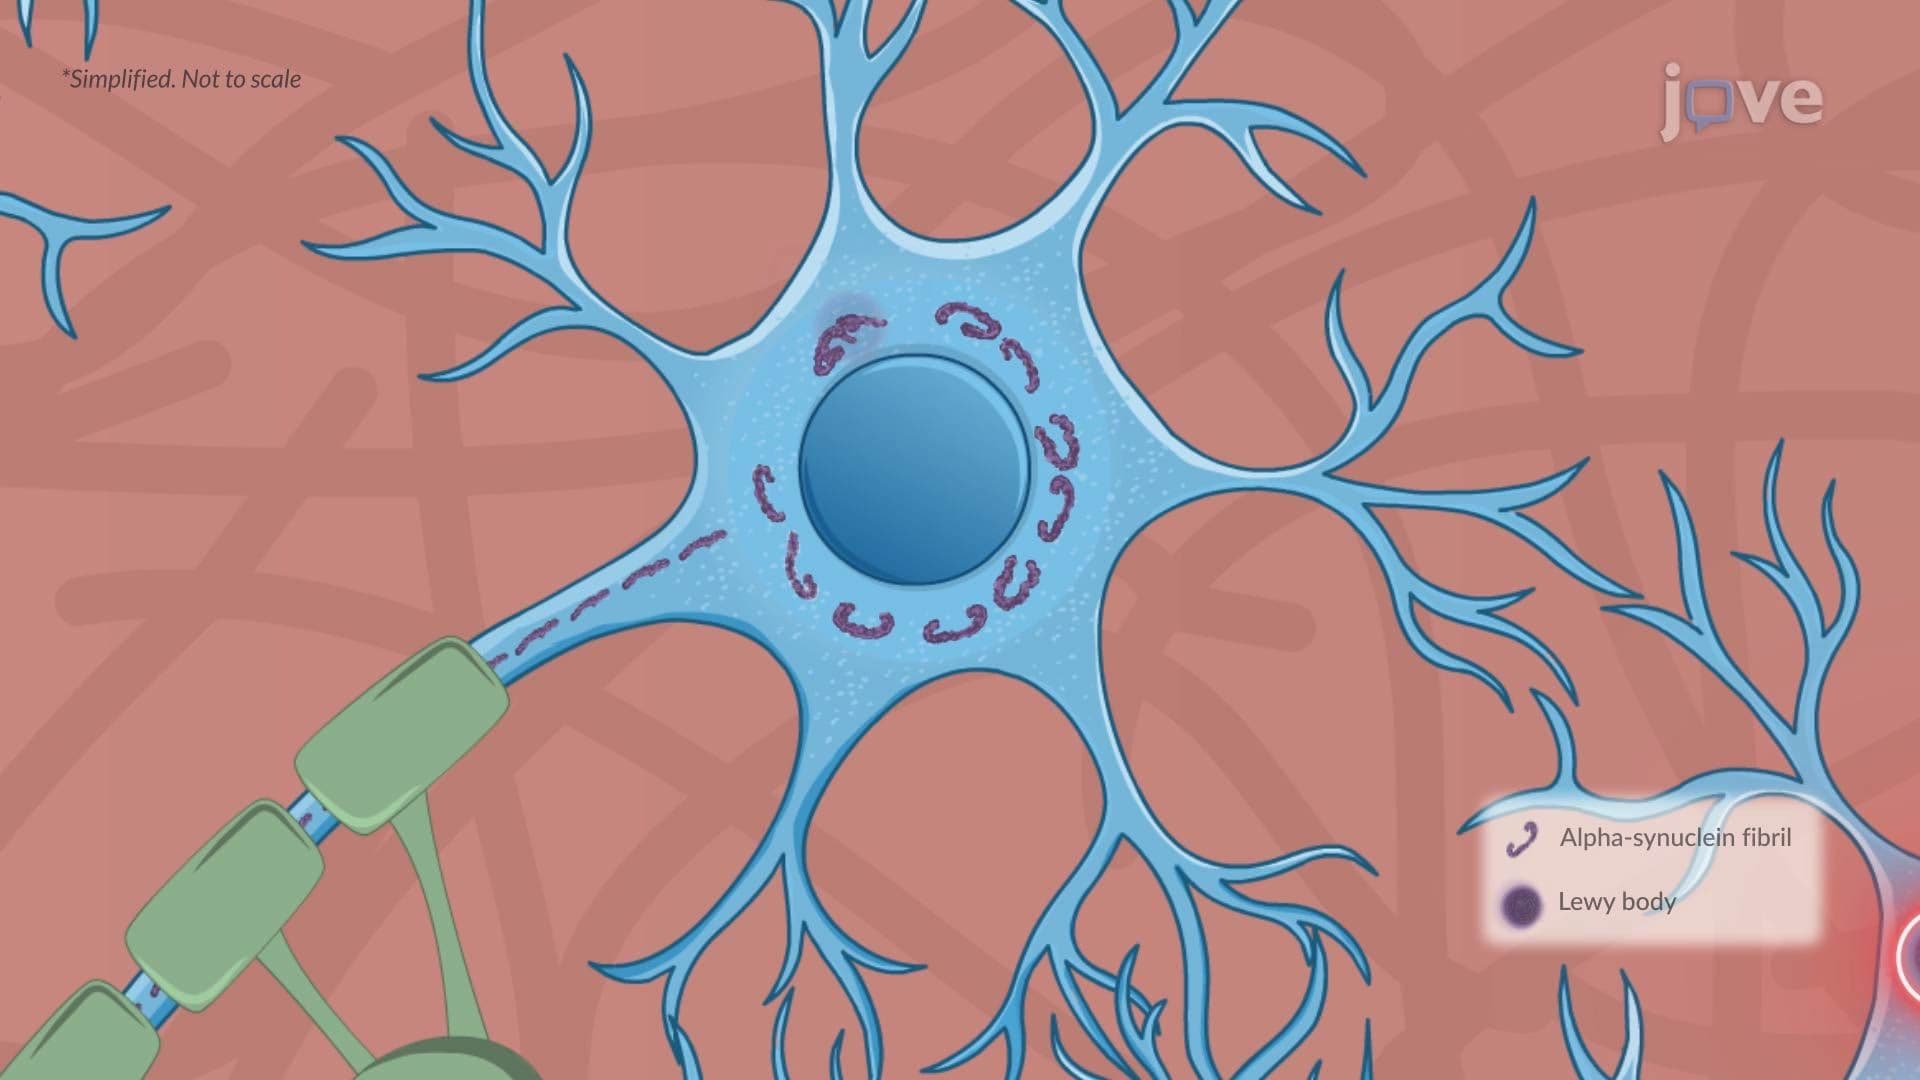 01:24
Parkinson Disease ll: Pathophysiology
 01:15
Parkinson's Disease: Overview
 01:21
Huntington Disease l: Introduction
 01:11
Alterations in Muscle Tone lll