Related Experiment Video
Updated: Apr 29, 2026

The Creation of a Rat Model for Osteosarcopenia via Ovariectomy
Published on: February 21, 2025
Sarcopenia in pediatric gastroenterology and hepatology: an updated review
Toshifumi Yodoshi1,2,3
1Division of Gastroenterology, Hepatology and Nutrition, Cincinnati Children's Hospital Medical Center, Cincinnati, OH, USA.

Insights
Pediatric sarcopenia, the loss of muscle mass and strength in children, is linked to chronic diseases and predicts poor outcomes. Early diagnosis and management, including nutrition and exercise, are crucial for improving prognosis.
Area of Science:
- Pediatric Gastroenterology and Hepatology
- Muscle Physiology
- Clinical Outcomes Research
Background:
- Sarcopenia, the loss of skeletal muscle mass and strength, is increasingly recognized in pediatric gastroenterology and hepatology.
- Secondary sarcopenia in children results from chronic inflammation, malnutrition, inactivity, corticosteroids, endocrine issues, and anabolic resistance.
- Pediatric definitions are heterogeneous due to growth and puberty influencing body composition; diagnosis uses size-adjusted muscle indices against age/sex curves.
Purpose of the Study:
- To review the epidemiology, pathophysiology, diagnosis, and management of pediatric sarcopenia in gastrointestinal and liver diseases.
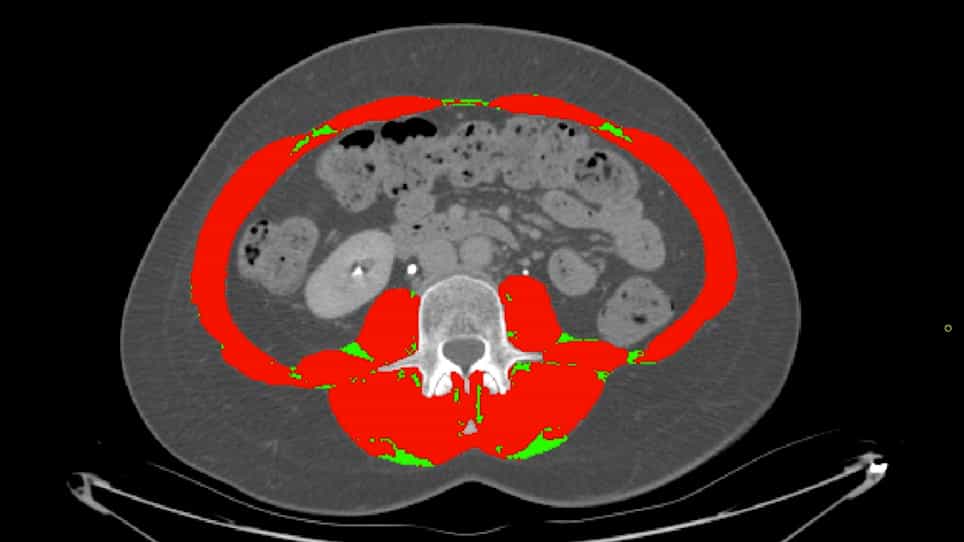
- To discuss diagnostic tools like imaging, DXA, BIA, and grip strength, noting their pros and cons.
- To propose a diagnostic algorithm and management strategies beyond caloric supplementation.
Main Methods:
- Literature review of current evidence on pediatric sarcopenia in GI and liver diseases.
- Analysis of diagnostic tools including CT/MRI, DXA, BIA, and grip strength.
- Development of a pragmatic diagnostic algorithm and management outline.
Main Results:
- Sarcopenia is a clinically meaningful predictor of adverse outcomes in pediatric liver transplantation, cirrhosis, and inflammatory bowel disease.
- It correlates with higher waitlist mortality, longer ICU stays, more infections post-transplant, aggressive disease, earlier biologic escalation, and increased surgical risk.
- Body mass index is insufficient for diagnosis; sarcopenic obesity and MASLD may show normal/elevated weight with muscle depletion.
Conclusions:
- Early recognition of pediatric sarcopenia is vital for risk stratification and improving functional outcomes.
- Management should include adequate protein, resistance exercise, and optimizing underlying GI/liver disease.
- Effective management can improve the long-term prognosis for children with chronic gastrointestinal and liver diseases.
Abstract:
Sarcopenia-the pathologic loss of skeletal muscle mass and strength-is increasingly recognized in pediatric gastroenterology and hepatology as an important determinant of clinical outcomes. Although historically linked to aging, secondary sarcopenia in children arises from chronic inflammation, malnutrition, physical inactivity, corticosteroid exposure, endocrine disturbances, and anabolic resistance. Unlike adult medicine, where diagnostic frameworks are more established, pediatric definitions remain heterogeneous because growth and puberty substantially influence body composition and muscle function. Diagnosis therefore relies on size-adjusted muscle indices, usually normalized to height squared, interpreted against age- and sex-specific reference curves. Body mass index alone is insufficient because muscle depletion and abnormal fat distribution may be present despite normal or elevated body weight, particularly in children with sarcopenic obesity and metabolic dysfunction-associated steatotic liver disease. Accumulating evidence suggests that pediatric sarcopenia is not simply a marker of frailty but a clinically meaningful predictor of adverse outcomes. In pediatric liver transplantation and cirrhosis, sarcopenia is associated with higher waitlist mortality, longer intensive care stays, and more posttransplant infections. In pediatric inflammatory bowel disease, reduced muscle mass correlates with aggressive disease, earlier biologic escalation, and increased surgical risk. This review summarizes current evidence on the epidemiology, pathophysiology, diagnosis, and management of pediatric sarcopenia in gastrointestinal and liver diseases. We discuss available diagnostic tools, including computed tomography/magnetic resonance imaging, dual-energy x-ray absorptiometry, bioelectrical impedance analysis, and grip strength, highlighting their practical advantages and limitations. We also propose a pragmatic diagnostic algoririthm and outline management strategies that extend beyond caloric supplementation, emphasizing adequate protein intake, resistance exercise, and optimization of underlying disease. Early recognition of sarcopenia may improve risk stratification, functional outcomes, and long-term prognosis in children with chronic gastrointestinal and liver diseases.
Related Concept Videos
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:15
Enteral Nutrition II: Nasointestinal and Gastrostomy Feeding
Nasointestinal Feeding
Nasointestinal feeding involves placing a tube...
 01:21
Overview of Protein Metabolism
Amino acids play various roles in the body once they are absorbed into cells. They are restructured...
 01:20
Inborn Errors of Metabolism
 01:22
Lysosomal Hydrolases