Early lung ultrasound for clinical risk stratification in acute coronary syndrome: a prospective cohort study
Begoña Hernández-Meneses1, María J Cristo-Ropero2, Antonio P Rivas-García3
1Coronary Care Unit, Cardiology Department, Hospital Universitario Virgen Macarena, Seville, Spain. bhdezmeneses@gmail.com.

Abstract:
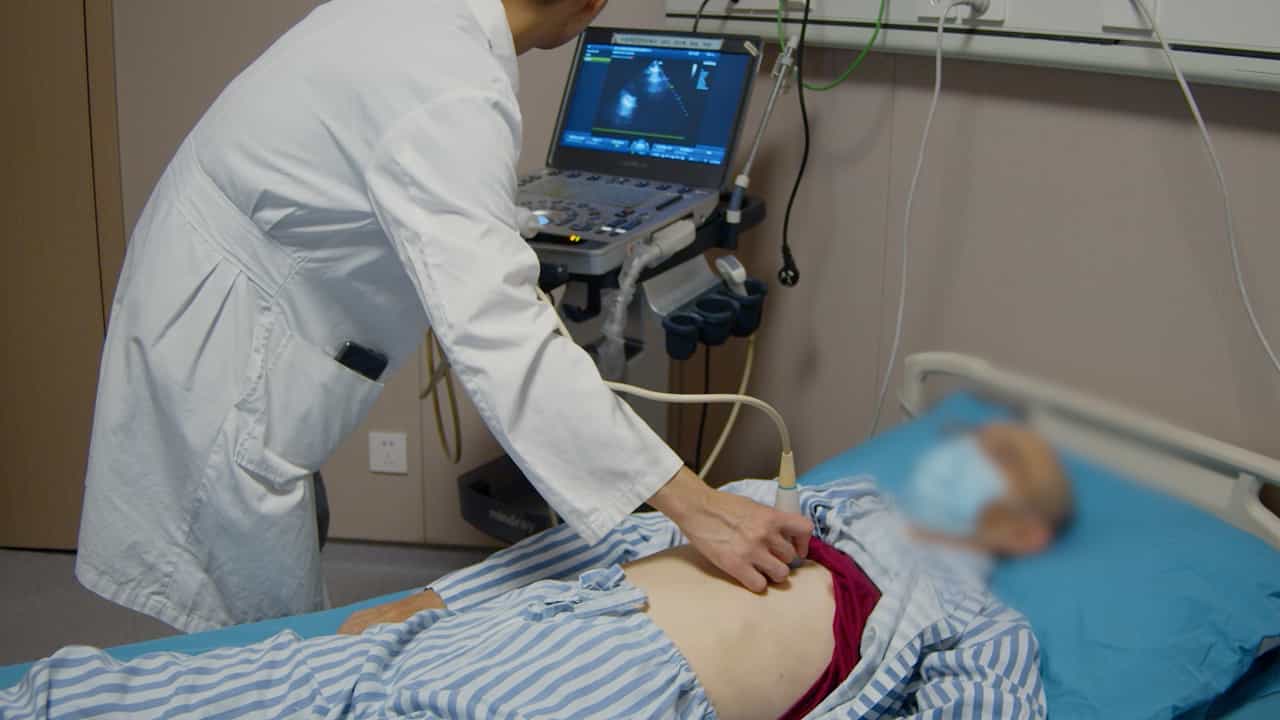
Early identification of pulmonary congestion in acute coronary syndrome (ACS) remains challenging and is associated with adverse outcomes. Lung ultrasound (LUS) is a rapid bedside tool that may improve early clinical risk stratification. We conducted a prospective observational cohort study including 189 patients with type-1 ACS. LUS was performed within 24 h of admission; LUS positivity was defined as ≥ 3 B-lines in ≥ 2 zones per hemithorax. The number of lung segments with ≥ 3 B-lines was analyzed as a continuous variable. NT-proBNP and CA125 were also measured within 24 h of admission. The primary in-hospital outcome was acute heart failure (AHF), defined as the need for intravenous diuretics or mechanical ventilatory support. The long-term outcome was a 1-year composite of all-cause death, stroke, reinfarction, or hospitalization for heart failure. LUS positivity was present in 15.9% of patients. AHF occurred in 90% of LUS-positive patients compared with 20.8% of LUS-negative patients (p < 0.001). After multivariable adjustment, LUS positivity remained strongly associated with AHF. Each additional LUS-positive lung segment independently increased the odds of AHF (OR 1.59 per segment, 95% CI 1.29–1.97, p < 0.001). Receiver operating characteristic analysis showed good discrimination for NT-proBNP (AUC 0.84) and LUS-positive segments (AUC 0.78) in identifying AHF, while CA125 showed moderate discrimination (AUC 0.71). During 1-year follow-up, 27 patients experienced the composite endpoint. LUS positivity independently predicted the outcome (adjusted HR 8.2, 95% CI 3.1–21.6, p < 0.001), and each additional LUS-positive segment increased event risk (adjusted HR 1.4 per segment, 95% CI 1.2–1.7, p < 0.001). LUS findings provided incremental prognostic value beyond clinical variables and NT-proBNP. Early lung ultrasound provides robust and independent prognostic information in ACS for both early heart failure deterioration and 1-year outcomes. LUS, together with NT-proBNP and CA125, may improve early clinical risk stratification using a simple bedside approach.

Related Concept Videos
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
 01:25
Imaging Studies for Cardiovascular System VI: Calcium -Scoring CT
 01:20
Imaging Studies for Cardiovascular System III: X-Ray
Definition and Purpose
An X-ray, or radiograph, is a non-invasive method that uses ionizing radiation to take images of internal structures. It is mainly used in cardiac imaging to examine the heart, lungs, and major blood vessels, aiming to identify abnormalities in the heart's size, shape, and position, such as heart failure, congenital defects, and vascular...
 01:17
Imaging Studies for Cardiovascular System I:Echocardiography
Indications: Echocardiography is utilized to diagnose heart failure, valve disorders, and myocardial infarction. It also assesses cardiac structures' size, shape, and motion,...
 01:20
Imaging Studies for Cardiovascular System II:Types of Echocardiography
Types of Echocardiography
Transthoracic Echocardiography (TTE)
TTE is the most common type of echocardiogram which involves placing a transducer on the patient's chest, emitting sound waves to create heart images. TTE is invaluable for evaluating the heart's size, structure, and motion, making it particularly useful for...