Related Experiment Video
Updated: Jun 29, 2026
06:59
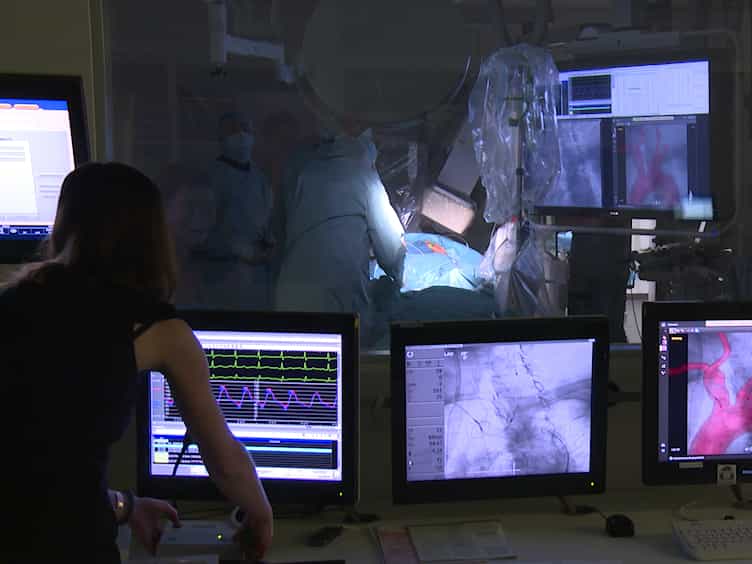
Improved Registration of 3D CT Angiography with X-ray Fluoroscopy for Image Fusion During Transcatheter Aortic Valve Implantation
Published on: June 3, 2018
9.7K
Intensive care utilization and clinical outcomes after transcatheter aortic valve implantation: a nationwide
Yusuke Mizobuchi1, Yoshitaka Aoki2, Kensuke Kobayashi1
1Department of Anesthesiology and Intensive Care Medicine, Hamamatsu University School of Medicine, 1-20-1 Handayama, Chuo-ku, Hamamatsu, 431-3192, Shizuoka, Japan.
Heart and Vessels
|April 28, 2026

Abstract
No abstract available in PubMed .

Related Concept Videos
 01:26
Cardiac Catheterization IV: Nursing Management
Nursing responsibilities before cardiac catheterization include:Assess for allergies and establish baseline health status.Before cardiac catheterization, assess the patient for allergies to contrast dye. Perform a comprehensive baseline assessment, including vital signs, heart and breath sounds, and a neurovascular assessment of the extremities, noting distal pulses, skin color, and temperature. Instruct the patient to fast for 8-12 hours before the procedure. Evaluate baseline laboratory...
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
Aortic valve regurgitation (AR) occurs when the aortic valve fails to close properly, allowing blood to flow backward from the aorta into the left ventricle. This backflow can result in two distinct clinical presentations: acute and chronic AR, each characterized by its own set of symptoms and physical findings.Acute Aortic RegurgitationAcute AR presents with a sudden onset of severe symptoms. Patients typically experience profound dyspnea (shortness of breath), chest pain, and signs of left...
 01:25
Aortic Regurgitation III: Medical Management
Aortic regurgitation (AR) is when the aortic valve does not close or seal properly, leading to backward blood circulation from the aorta into the left ventricle during diastole. Common causes of AR include rheumatic heart disease, congenital valve defects, and aortic root dilation. Managing AR requires a multifaceted approach to alleviate symptoms, preserve left ventricular function, and address the underlying cause of the regurgitation. Patients with symptomatic AR or significant left...
 01:30
Acute Coronary Syndrome III: Diagnostic Studies
Diagnosing acute coronary syndrome or ACS begins with a thorough patient history. Notable symptoms include central, crushing chest pain radiating to the left arm, neck, jaw, or back, along with shortness of breath, sweating (diaphoresis), nausea, vomiting, dizziness, and palpitations.It is crucial to note any history of cardiac illnesses and assess risk factors, including age, gender, smoking, hypertension, diabetes, hyperlipidemia, and a sedentary lifestyle.During physical examination, vital...
 01:28
Acute Coronary Syndrome IV: Interprofessional Care
IntroductionThe management of Acute Coronary Syndrome (ACS) aims to minimize myocardial damage, preserve myocardial function, and prevent complications.Initial ManagementInpatient management involves continuous cardiac monitoring, preferably in an ICU, focusing on blood pressure, serum sodium, potassium, and creatinine levels, and urine output. Ongoing pharmacologic management is crucial for stabilizing the patient.Supplemental Oxygen: Administer supplemental oxygen if oxygen saturation is...
 01:29
Pulmonary Embolism II: Diagnostic Studies and Interprofessional Care
Diagnosing Pulmonary EmbolismDiagnosing pulmonary embolism (PE) involves clinical assessment and advanced imaging tests. The preferred diagnostic tool is the spiral (helical) CT scan or CT angiography (CTA), which uses intravenous contrast media to visualize the pulmonary vasculature and identify emboli.A ventilation-perfusion (V/Q) scan is an alternative for patients unable to receive contrast media. This scan includes both perfusion and ventilation scanning. Perfusion scanning involves...