Related Experiment Video
Updated: Apr 30, 2026
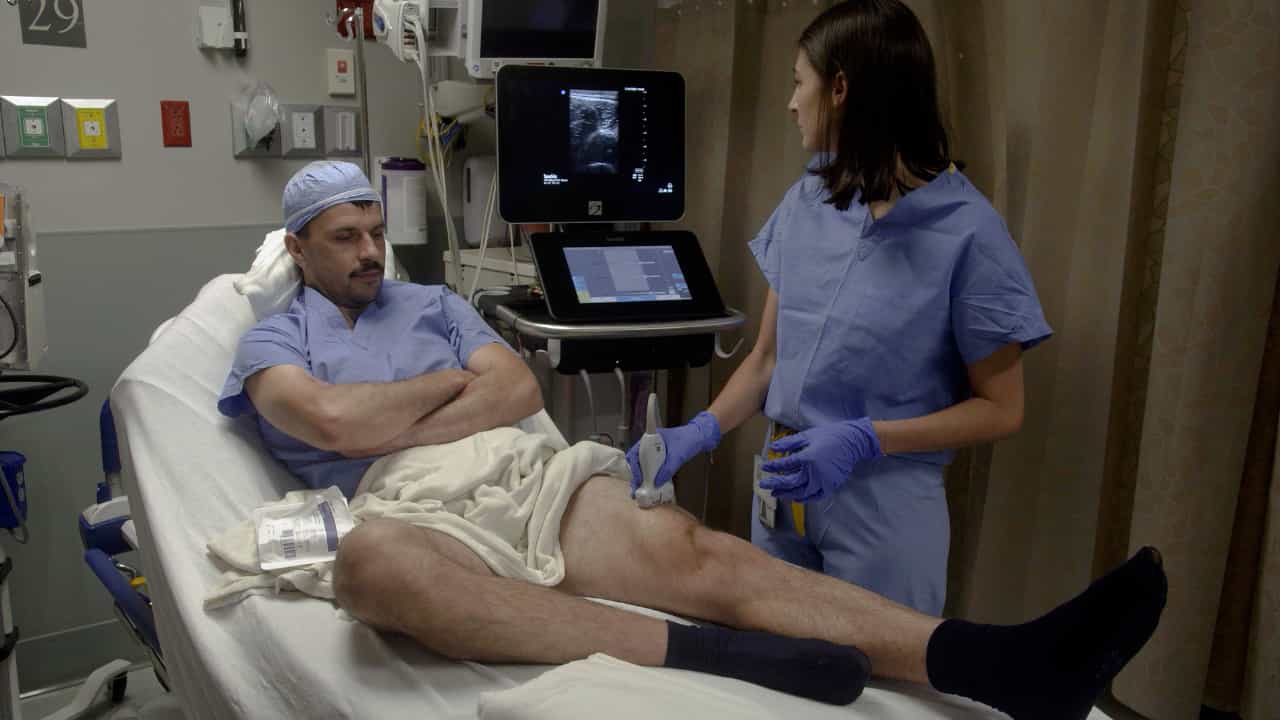
Author Spotlight: Assessing Surgical Frailty with Point-of-Care Ultrasound of Quadriceps Muscles
Published on: July 26, 2024
Construction and validation of a risk prediction model for oral frailty in elderly patients with chronic heart
Xue Song1, Rong Chai1, Jing Ye1
1Mianyang Central Hospital, School of Medicine, University of Electronic Science and Technology of China, Mianyang, China.

Objective:
To investigate the prevalence of oral frailty among hospitalized elderly patients with chronic heart failure (CHF), identify its associated risk factors, and construct and validate a risk assessment model to provide scientific evidence for early identification and intervention.
Methods:
A convenience sample of 343 hospitalized elderly patients with chronic heart failure was recruited from a tertiary general hospital in Mianyang, China, between May and November 2025. Data were collected using a general information questionnaire, the Oral Frailty Index-8 (OFI-8), Frailty Phenotype (FP), Mini Nutritional Assessment-Short Form (MNA-SF), heart function-related clinical indicators, the Geriatric Oral Health Self-Efficacy Scale, the Geriatric Oral Health Assessment Index (GOHAI), and the Geriatric Depression Scale-Short Form (GDS-SF). Logistic regression analysis was performed to identify factors associated with oral frailty. A visualized nomogram prediction model was developed using R software. Model discrimination and calibration were evaluated using the receiver operating characteristic (ROC) curve, area under the curve (AUC), Hosmer-Lemeshow goodness-of-fit test, and Bootstrap resampling. Decision curve analysis (DCA) was conducted to assess the clinical applicability of the model.
Results:
A total of 350 questionnaires were distributed, and 343 valid questionnaires were returned, yielding an effective response rate of 98.0%. Among the 343 patients, 176 cases of oral frailty were identified, with a prevalence of 51.3%. Logistic regression analysis showed that advanced age, smoking, physical frailty, malnutrition, polypharmacy, and oral health-related self-efficacy were significant predictors of oral frailty (all p < 0.05). The prediction model demonstrated good discrimination, with an AUC of 0.857. The Hosmer-Lemeshow test indicated good model fit (χ2 = 4.696, p = 0.790). After Bootstrap internal validation, the corrected concordance index (C-index) was 0.845, and the calibration curve showed good agreement between predicted and observed outcomes. Decision curve analysis indicated that the model provided a high net clinical benefit.
Conclusion:
The risk assessment model for oral frailty in elderly patients with chronic heart failure developed in this study demonstrates good discrimination and calibration. It may serve as a reliable tool for clinicians to identify and screen individuals at high risk of oral frailty at an early stage, thereby facilitating targeted prevention and intervention strategies.


Related Concept Videos
 01:30
Heart Failure IV: Classification and Diagnostic Evaluation
 01:22
Heart Failure VI: Adjunct Therapies
 01:26
Heart Failure III: Clinical Manifestations