Related Experiment Video
Updated: May 1, 2026
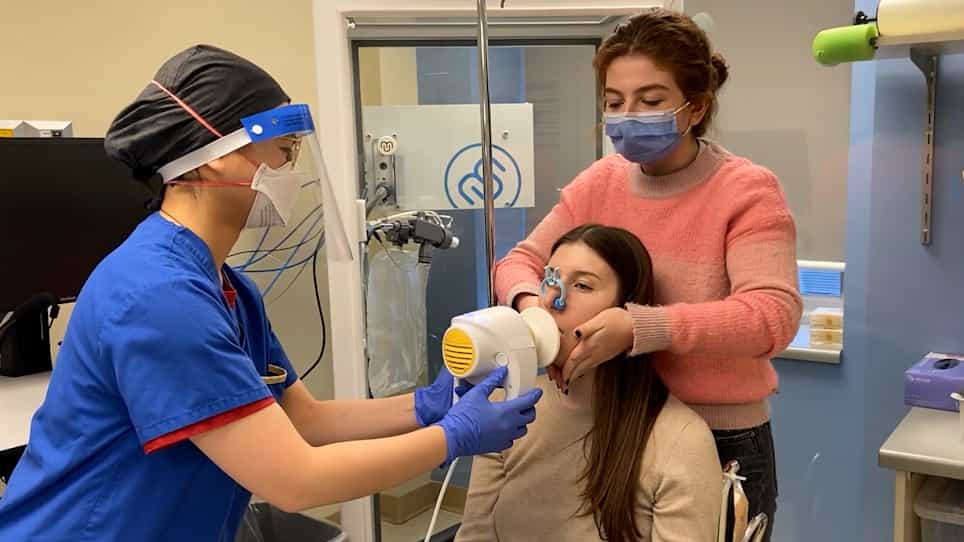

Conducting Respiratory Oscillometry in an Outpatient Setting
Published on: April 8, 2022
Feasibility and compliance with quality indicators for pediatric respiratory care in Jordanian emergency departments:
Islam E Alkhazali1, Ahmad Alrawashdeh2, Mohd Hashairi Fauzi3
1Department of Allied Medical Sciences, Faculty of Applied Medical Sciences, Al al-Bayt University, Mafraq, Jordan; School of Medical Sciences, Health Campus, USM, Kubang Kerian, 16150, Malaysia.

Insights
Prospective observation is superior to chart audits for measuring pediatric emergency department quality indicators (QIs). Direct observation captured all QIs, while audits missed many, revealing overuse of radiography and antibiotics.
Area of Science:
- Pediatric Emergency Medicine
- Healthcare Quality Improvement
- Clinical Data Management
Background:
- Evaluating and enhancing pediatric emergency care quality necessitates efficient data collection methods.
- This study addresses the need to assess quality indicators (QIs) for common pediatric respiratory illnesses in emergency departments (EDs).
Purpose of the Study:
- To evaluate the feasibility and compliance of pediatric asthma, bronchiolitis, and croup quality indicators (QIs) in emergency departments (EDs).
- To compare QI measurement accuracy between prospective direct observation and retrospective chart audits.
- To identify factors influencing QI feasibility and compliance.
Main Methods:
- A mixed-methods approach was employed in two EDs during September-October 2024.
- Assessed 26 QIs for pediatric asthma, bronchiolitis, and croup using prospective observation and chart audits.
- Conducted semi-structured interviews with pediatric residents to explore influencing factors.
Main Results:
- Prospective observation deemed all 26 QIs feasible, contrasting with chart audits capturing only 16 (61.5%).
- Higher QI compliance estimates were consistently observed via direct observation, with significant discrepancies in clinical assessment and treatment indicators.
- Overuse of radiography and antibiotics was noted across all three pediatric conditions.
Conclusions:
- QIs derived from electronic clinician orders were consistently captured by both methods.
- Chart audits failed to reliably capture QIs dependent on physical assessment and clinical documentation.
- While overall compliance was acceptable, lower rates for clinical evaluation and diagnostic indicators underscore the need for complementary data collection strategies.
Background:
Evaluating and improving the quality of care requires efficient and accurate data collection. This study aimed to evaluate the feasibility and compliance of quality indicators (QIs) for pediatric patients with asthma, bronchiolitis, and croup in emergency departments (EDs), to compare QI measurement using prospective direct observation and chart audit, and to explore factors influencing QI feasibility and compliance.
Methods:
A mixed-methods study was conducted in two EDs between September and October 2024. The feasibility and compliance of 26 QIs were assessed through prospective observation of ED care for asthma (n = 249), bronchiolitis (n = 91), and croup (n = 147), alongside retrospective chart audits. Semi-structured interviews with nine pediatric residents were conducted to explore factors influencing QI feasibility and compliance.
Results:
All 26 QIs were feasible during prospective observation, whereas only 16 (61.5%) were feasible using chart audits. Compliance varied across indicators, with consistently higher estimates observed using prospective observation and marked discrepancies for several clinical assessment and treatment indicators. Overuse of radiography and antibiotics was identified across all three conditions. Thematic analysis identified eight themes and 17 subthemes related to documentation practices, workload, and system-level challenges.
Conclusions:
QIs based on electronically recorded clinician orders were consistently captured using both methods, whereas those relying on physical assessment and clinical documentation were not reliably captured in chart audits. Compliance was generally acceptable but lower for clinical evaluation and diagnostic indicators, highlighting the need for complementary data collection methods.
More Related Videos
 07:52
Expired CO2 Measurement in Intubated or Spontaneously Breathing Patients from the Emergency Department
Published on: January 29, 2011
 06:15
Protocol and Guidelines for Point-of-Care Lung Ultrasound in Diagnosing Neonatal Pulmonary Diseases Based on International Expert Consensus
Published on: March 6, 2019
Related Concept Videos
 01:23
Assessment of Respiration
Subjective Assessment: Nurses interview the patient to gather information directly during the subjective assessment. It includes questions about the individual's medical history, medications, and symptoms, focusing on past respiratory conditions like...
 01:19
Respiratory Assessment: Purpose and Indications
Objectives and Importance:
The primary goal of respiratory assessment is to evaluate patients at early risk of clinical deterioration. Since respiratory distress often precedes other signs of declining health, breathing patterns and sounds become a...
 01:30
Assessment of Airway, Skin Color, and Use of Accessory Muscles
Introduction
The initial evaluation of a patient's respiratory system...
 01:30
Respiratory System Abnormal Finding I: Inspection and Percussion
Inspection Findings
During an inspection, several findings may suggest the presence of respiratory distress or disease. Pursed-lip breathing, where exhalation is slowed by...
 01:20
Assessment of Ventilation I: Respiratory Rate
A Ventilation assessment is critical for monitoring a patient's health status. Respiration, one of the most accessible vital signs, provides insights into the function of numerous body systems and can indicate serious health issues, such as brainstem injuries from head trauma.
Critical Guidelines for Assessing Ventilation:
 01:29
Acute Respiratory Failure-V
Ensure that patients are monitored continuously for their response to therapy, including changes in...