Related Experiment Video
Updated: May 1, 2026
Comparative Proteomic Analysis of Whole Kidney, Medulla, and Cortical Tubules in Diabetic Pathogenesis of Kidney Injury in Mice
Published on: May 2, 2025
Investigation of Renal Potassium Loss and Anion Gap Patterns in Diabetic Ketoacidosis: A Study From South India
Anjali Jayakumar1, Teny Mathew1, Sibin K Prasad1
1Department of General Medicine, Pushpagiri Institute of Medical Sciences and Research Centre, Tiruvalla, IND.

Objective:
This study aims to assess the extent and patterns of renal potassium loss and delineate anion gap profiles in patients with diabetic ketoacidosis (DKA) presenting to emergency departments in India. By characterizing these patterns, the study aims to optimize electrolyte replacement strategies and provide deeper insights into the unmeasured contributors to metabolic acidosis in DKA, thereby supporting improved clinical outcomes.
Methodology:
This cross-sectional observational study was conducted over 17 months in the Emergency Department of a tertiary care hospital in Kerala to assess electrolyte disturbances in DKA. Fifty-one adult patients with confirmed DKA were enrolled. Data were collected at presentation, prior to treatment, and included clinical parameters, serum electrolytes, anion gap, and urine indices. Renal potassium wasting was evaluated using FEK and urine potassium/creatinine ratio. Laboratory analyses followed standard protocols, and statistical analysis was performed using Statistical Package for the Social Sciences version 25 (IBM Corp., Armonk, NY).
Results:
Among the patients, 31 (60.8%) presented with an elevated anion gap >14 mEq/L, indicating high-anion-gap metabolic acidosis (HAGMA), with a mean of 18.19 ± 3.09 mEq/L. A total of 19 (37.3%) patients had a mildly elevated anion gap of 12-14 mEq/L, with a mean of 13.4 ± 0.54 mEq/L, while only one (2.0%) patient had a normal anion gap in the range of 10-12 mEq/L, with a value of 11.8 mEq/L. The difference in mean anion gap among these groups was statistically significant (analysis of variance: F = 39.73, p < 0.001). Renal potassium loss was evaluated in patients with hypokalemia. In mild hypokalemia cases, urine creatinine was 157 mg/dL and urine potassium was 65 mmol/L, resulting in a K⁺/creatinine ratio of 0.41 mmol/mg. In the single case of moderate hypokalemia, urine creatinine was 180 mg/dL and urine potassium was 55 mmol/L, yielding a K⁺/creatinine ratio of 0.31 mmol/mg. These findings indicate renal potassium wasting in both mild and moderate hypokalemia cases.
Conclusion:
The study found that while most DKA patients had normokalemia, significant cases of hyperkalemia and renal potassium loss were present. A strong positive correlation between serum potassium and magnesium indicated interdependent regulation. Elevated anion gaps confirmed HAGMA as a dominant pattern.
More Related Videos
 07:22
Glycemic Impact on Knee Osteoarthritis Symptoms on Physical, Radiographic, and Inflammatory Markers among Individuals Aged 50 and Over with Diabetes
Published on: March 7, 2025
 09:02
A Large Animal Model for Acute Kidney Injury by Temporary Bilateral Renal Artery Occlusion
Published on: February 2, 2021
Related Concept Videos
 01:22
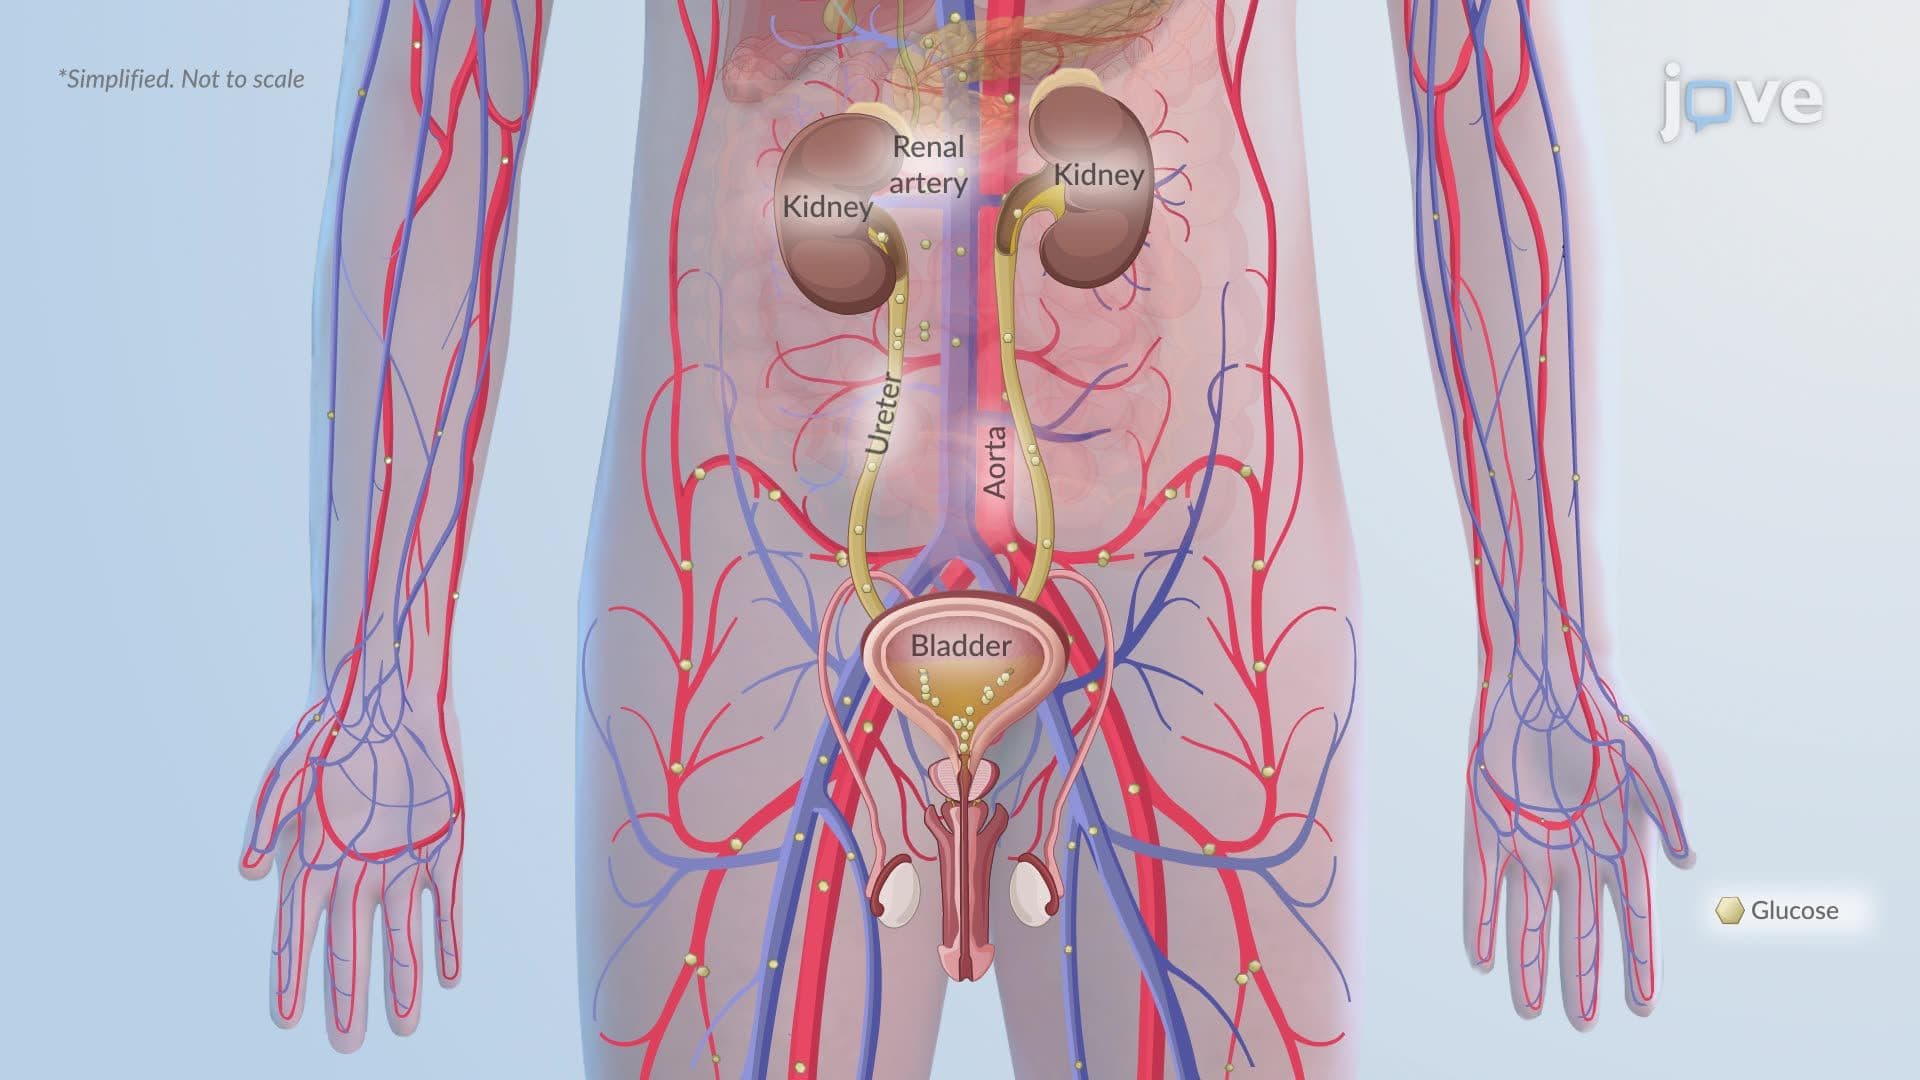
Diabetic Ketoacidosis ll: Pathophysiology
 01:25
Diabetic Ketoacidosis l: Introduction
 01:30
Acute Kidney Injury IV: Diagnostic Studies and Prevention
 01:28
Chronic Kidney Disease III: Interprofessional Care
 01:28
Diabetic Nephropathy
 01:29
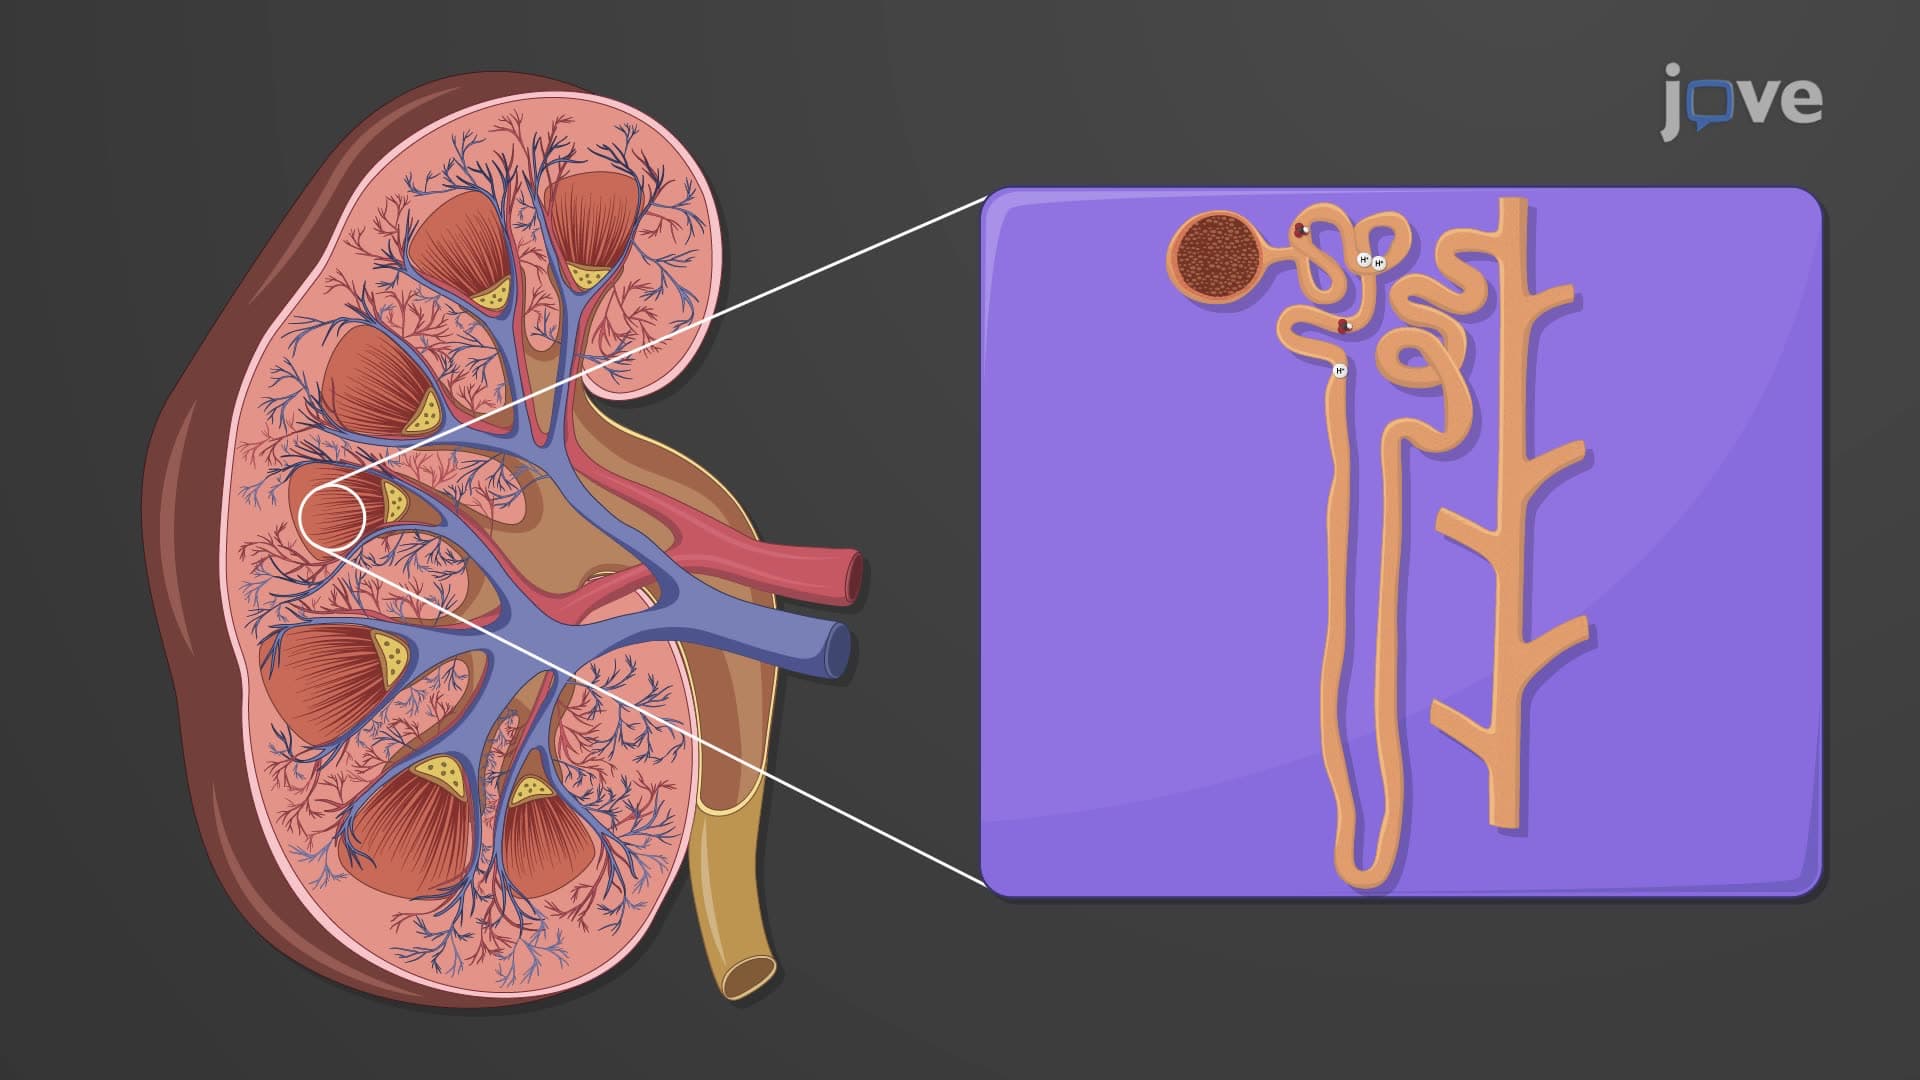
Renal Regulation of Acid-Base Balance
In the kidneys, cells within the proximal convoluted tubules (PCT) and the collecting ducts secrete hydrogen ions (H+) into the tubular fluid. Specifically, in the PCT, Na+/H+ antiporters secrete H+ while reabsorbing Na+.
However, the intercalated cells in...