Related Experiment Video
Updated: May 1, 2026


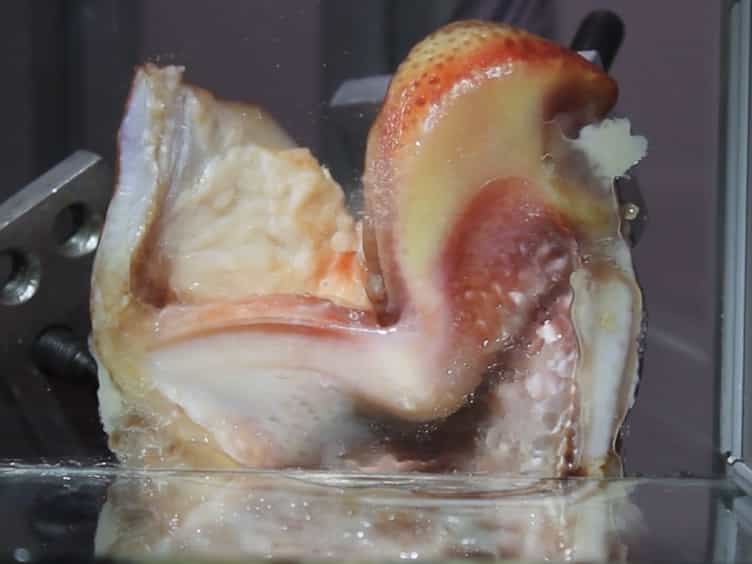
Synthetic, Multi-Layer, Self-Oscillating Vocal Fold Model Fabrication
Published on: December 2, 2011
Vocal Fold Vibratory Kinematics and Acoustic Correlates in Pressed and Breathy Phonation
Laura E Toles1,2, Avery Moore1,2, Melanie A Turner Tice1
1Department of Otolaryngology-Head and Neck Surgery, The University of Texas Southwestern Medical Center, Dallas.

Purpose:
The overall aims of this study were to (a) examine how vocal fold kinematics differ across typical, pressed, and breathy phonation in vocally healthy adults and (b) investigate the relationships between high-speed videoendoscopic-derived kinematic measures and acoustic measures of cepstral peak prominence (CPP) and the amplitude difference between the first two spectral harmonics (H1-H2) and whether the relationships vary by phonation type.
Method:
Forty vocally healthy adults (32 female, eight male, with a mean age of 26 years) underwent simultaneous transoral rigid high-speed videoendoscopy (HSV; 4,000 frames per second) and acoustic recording during sustained /i:/ in three phonation types: typical, pressed, and breathy. Primary HSV parameters included closing quotient (ClQ), speed index (SI), amplitude-to-length ratio (ALR), stiffness index (STI), and normalized maximum area declination rate (MADRn). Primary acoustic measures were CPP and H1-H2. Mixed analyses of variance were conducted for phonation type differences in HSV parameters with main effects of phonation type, sex, and their interaction. Then, multiple regression models with phonation type interactions were conducted to assess the relationships between HSV and acoustic measures.
Results:
Relative to typical phonation, simulated pressed phonation showed lower values of ClQ, higher MADRn, and higher STI with large effects, whereas simulated breathy phonation demonstrated higher ClQ and lower MADRn with medium effects. CPP was significantly negatively correlated with ClQ and positively correlated with MADRn, SI, and STI. H1-H2 was significantly positively correlated with ClQ and ALR and negatively correlated with MADRn, SI, and STI. There was a significant phonation type interaction with the correlations between H1-H2 and MADRn, SI, and STI; in each, breathy phonation had a strong, negative relationship and pressed phonation had a small or negligible relationship. ClQ consistently correlated with both acoustic measures across all phonation types.
Conclusions:
Vibratory patterns in pressed phonation were suggestive of increased vocal fold contact stress, as lower ClQ and higher MADRn values suggest more abrupt, faster glottal closure. CPP and H1-H2 can reflect underlying glottal physiology, but their predictive value depends on phonation type in most cases. However, findings suggest that ClQ could be a robust physiological parameter with stable acoustic correlates regardless of phonation type.

Related Concept Videos
 01:28
Physical Assessment of the Respiratory Tract IV: Auscultation
Breath Sounds
Breath sounds are categorized into vesicular, bronchovesicular, and bronchial.
 01:21
Larynx
Anatomy of the Larynx
The larynx consists of various components, including cartilage, muscles, and vocal cords. Its structure includes three large unpaired cartilages—the thyroid, cricoid, and epiglottis—and three smaller paired cartilages—the arytenoids,...
 01:31
Respiratory System Abnormal Finding II: Palpation and Auscultation
Palpation Findings
During a respiratory assessment, palpation can reveal several vital abnormalities:
 01:29
Physical Assessment of the Respiratory Tract III: Percussion
Percussion in Respiratory Assessment
Percussion evaluates underlying tissue composition with audible and tactile vibrations,...
 01:24
Physical Assessment of the Respiratory Tract II: Palpation
Thoracic Palpation
Thoracic palpation detects tenderness, masses, lesions, respiratory excursions, and vocal fremitus. The nurse assesses...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement: