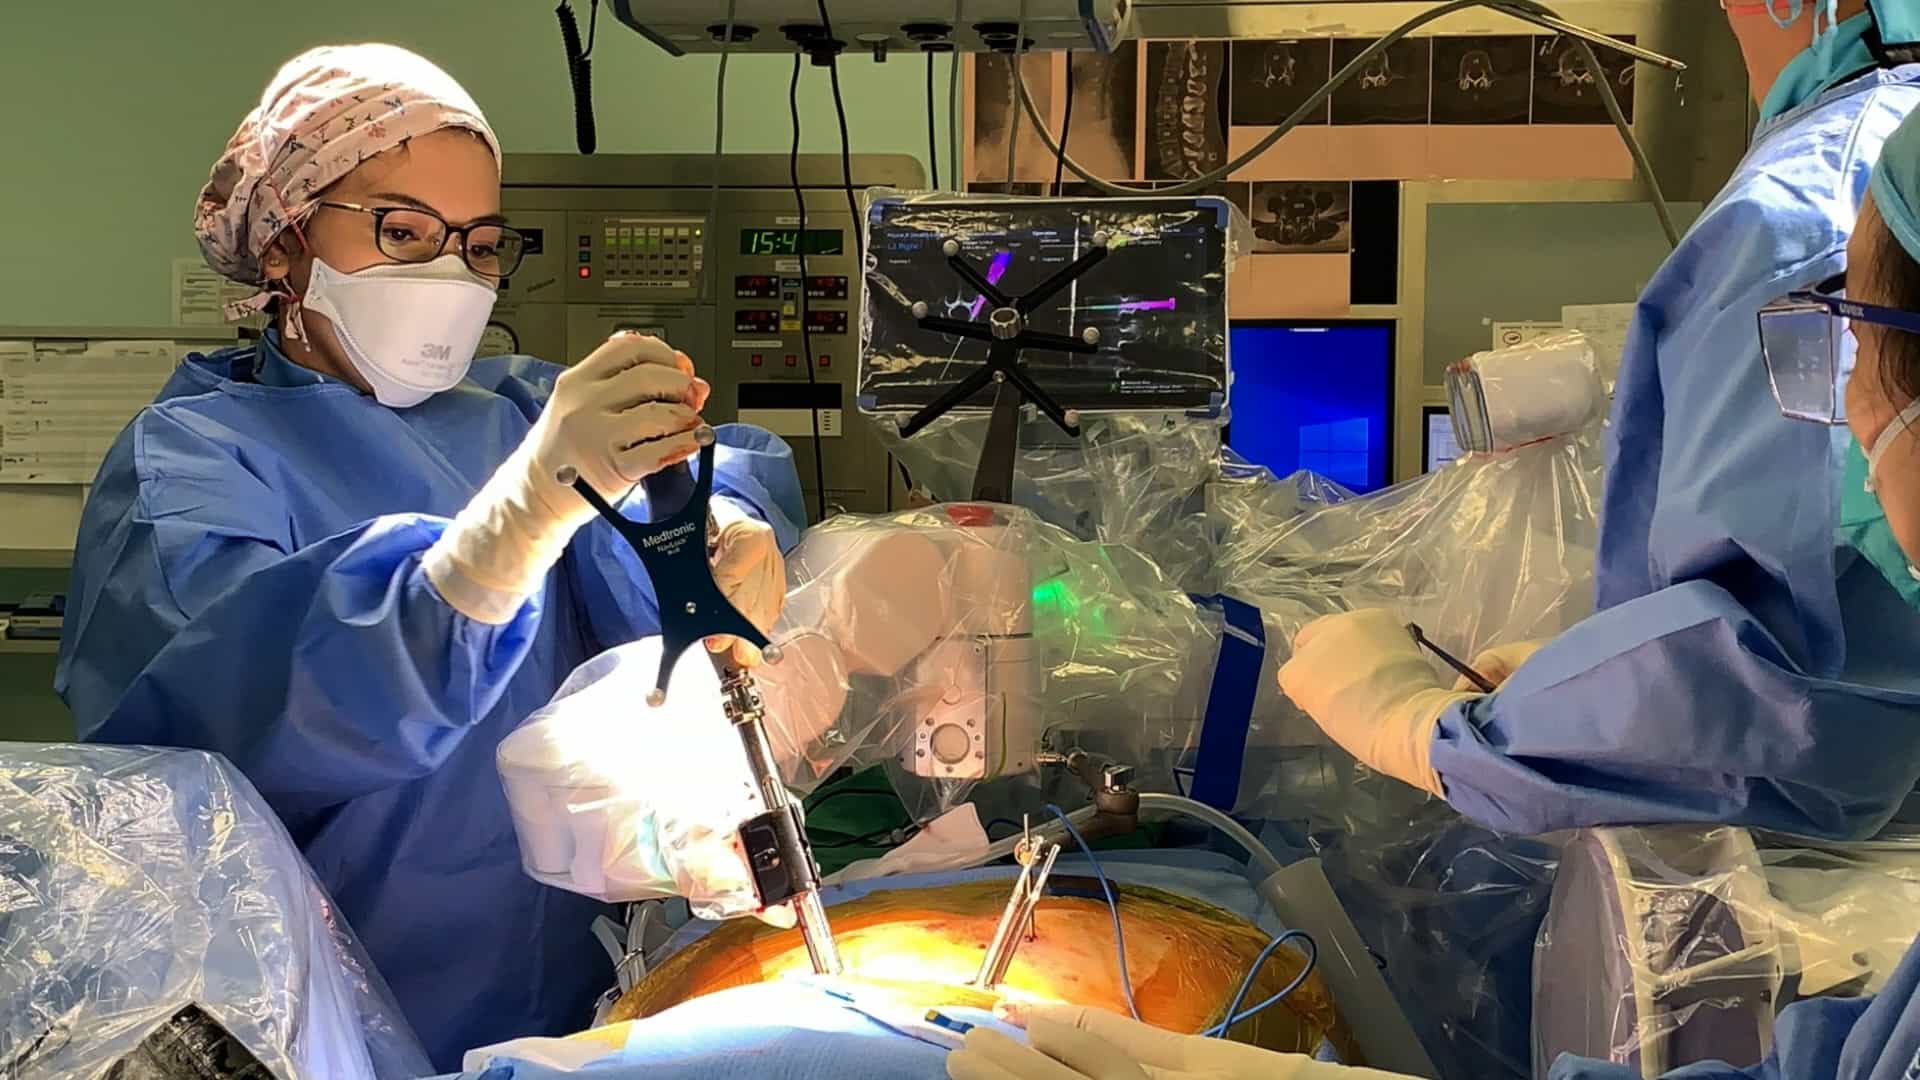
Related Experiment Video
Updated: May 2, 2026
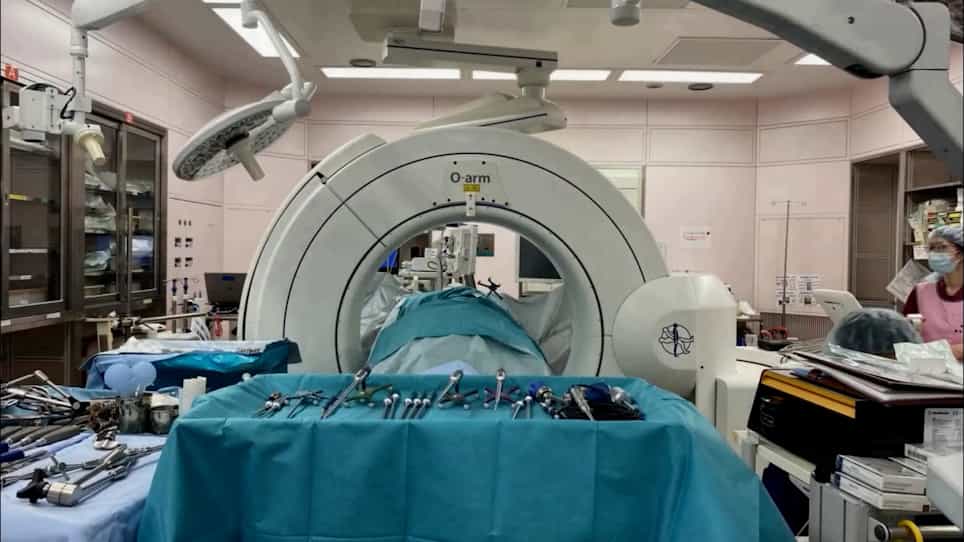
C-arm-Free Simultaneous OLIF51 and Percutaneous Pedicle Screw Fixation in a Single Lateral Position
Published on: September 16, 2022
Upright supine imaging can detect clinically relevant occult instability in degenerative lumbar spondylolisthesis - A
Tom Folkerts1,2, Julia Wimmer1,2, Lukas Schönnagel1
1Center for Musculoskeletal Surgery, Charité - Universitätsmedizin Berlin, Berlin, Germany.

Introduction:
Flexion-extension radiographs (FER) are widely used to assess segmental instability in degenerative lumbar spondylolisthesis (DLS) and guide surgical decision-making, as dynamic instability may be associated with suboptimal outcomes after decompression only. However, FER rely on patient effort, and pain or limited mobility can reduce reproducibility and underestimate instability. Upright-supine imaging (USI), comparing upright radiographs with supine MRI, may better capture slip dynamics, but its clinical value remains undefined.
Research Question:
To evaluate whether USI-derived segmental instability provides additional prognostic information beyond FER for predicting postoperative improvement in disability and low back pain (LBP) following decompression-only surgery for DLS.
Material And Methods:
This retrospective analysis of prospectively collected data included 92 DLS patients undergoing decompression-only surgery. Slip dynamics were quantified as between-position difference in relative translation (ΔRT) on FER and USI. Multivariable regression assessed associations between ΔRT and two-year outcomes (Oswestry Disability Index [ODI], LBP numeric rating scale). ROC analyses determined optimal ΔRT_USI cutoffs.
Results:
ΔRT_USI independently predicted postoperative improvement in ODI (p < 0.001) and LBP (p < 0.001), whereas ΔRT_FER was not associated with outcomes. ROC analysis identified a ΔRT_USI threshold of 7.9% as optimal (ODI: AUC = 0.87, sensitivity = 0.86, specificity = 0.81; LBP: AUC = 0.62, sensitivity = 0.9, specificity = 0.48). USI identified instability in 22.8% of patients, uncovering occult instability that FER missed. USI-unstable patients showed significantly less postoperative improvement (p < 0.001).
Discussion And Conclusion:
USI detects clinically relevant occult instability missed by FER and independently predicts outcomes after decompression-only surgery. A ΔRT_USI threshold of approximately 8% serves as a quantitative marker supporting USI for preoperative assessment in DLS.