Related Experiment Video
Updated: May 2, 2026
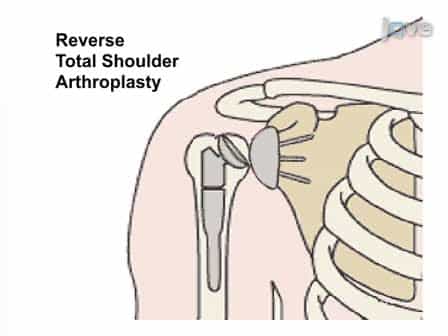

Reverse Total Shoulder Arthroplasty
Published on: July 5, 2011
Increased Risk of Medical and Implant-Related Complications in Patients With Atrial Fibrillation After Primary Total
Nishanth Muthusamy1, Adrien Canery1, Liam Edwards-Gaherty1
1Medicine, Renaissance School of Medicine, Stony Brook, USA.

Insights
Patients with atrial fibrillation (AF) face higher risks of medical and implant complications after total shoulder arthroplasty (TSA). This includes increased rates of stroke, pneumonia, VTE, and infection within two years post-surgery.
Area of Science:
- Orthopedic Surgery
- Cardiology
- Public Health
Background:
- Atrial fibrillation (AF) is a common comorbidity increasing surgical bleeding risks.
- Limited research exists on AF's impact on primary total shoulder arthroplasty (TSA) outcomes.
- Evaluating AF's association with postoperative complications after TSA is crucial.
Purpose of the Study:
- To assess the risk of 90-day and two-year medical complications following primary TSA in patients with AF.
- To determine the risk of implant-related complications after primary TSA in patients with AF.
- To compare complication rates between patients with and without preoperative AF diagnosis.
Main Methods:
- A multicenter database (TriNetX) queried patients undergoing primary TSA (2013-2023).
- Patients were divided into AF and non-AF cohorts, propensity-matched 1:1.
- Complications included medical events (stroke, pneumonia, VTE, MI, renal failure, transfusion, mortality) and implant issues (PJI, revision, dislocation).
Main Results:
- Propensity matching included 3,864 patients per cohort.
- Within 90 days, AF patients had higher risks of stroke, pneumonia, and VTE (p < 0.05).
- Within two years, AF patients showed increased risks for stroke, pneumonia, VTE, MI, renal failure, transfusion, mortality, total implant complications, and PJI (p < 0.05).
Conclusions:
- Preoperative AF diagnosis is linked to elevated 90-day and two-year medical and implant-related complication risks after TSA.
- Surgeons must recognize these heightened risks for patient optimization.
- Preoperative AF management may mitigate adverse outcomes in TSA patients.
Background:
Atrial fibrillation (AF) is a common cardiac comorbidity associated with increased risk of bleeding and complications following surgery. Few studies have evaluated the impact of preoperative diagnosis of AF on complications following primary total shoulder arthroplasty (TSA). The purpose of this study is to evaluate the risk of 90-day and two-year postoperative medical and implant-related complications in patients undergoing TSA with a diagnosis of AF.
Methods:
A multicentre database, TriNetX (TriNetX, LLC, Cambridge, MA, USA), was queried for patients who underwent primary TSA between 2013 and 2023. After exclusion criteria, patients were divided into two cohorts: those diagnosed with a preoperative diagnosis of AF prior to TSA and those without a preoperative diagnosis of AF (non-AF). The AF and non-AF cohorts were propensity-matched in a 1:1 ratio. Medical complications included sepsis, infection, stroke, pneumonia, renal failure, myocardial infarction (MI), venous thromboembolism (VTE), hemorrhage, blood transfusion, wound dehiscence, superficial surgical site infection (SSI), deep SSI, organ/space SSI, readmission, and mortality. Implant-related complications include revision TSA, periprosthetic joint infection (PJI), periprosthetic fracture, dislocation, and mechanical loosening.
Results:
Three thousand eight hundred sixty-four patients were included in each cohort after propensity matching, accounting for any significant differences in patient demographics or comorbidities. Within 90 days following primary TSA, patients with AF showed a significantly increased risk of stroke, pneumonia, and VTE compared to the non-AF cohort (p < 0.05). Within two years following TSA, patients with AF showed a significantly increased risk of stroke, pneumonia, VTE, MI, renal failure, blood transfusion, mortality, total implant-related complication rate, and PJI compared to the non-AF cohort (p < 0.05).
Conclusion:
Preoperative diagnosis of AF is associated with an increased risk of 90-day and two-year medical and implant-related complications following primary TSA. Surgeons should be aware of these risks to better optimize their patients.

