Related Experiment Video
Updated: May 2, 2026

Induction of Paralysis and Visual System Injury in Mice by T Cells Specific for Neuromyelitis Optica Autoantigen Aquaporin-4
Published on: August 21, 2017
ANCA-associated vasculitis with thoracic spinal canal dural involvement and hypertrophic cranial pachymeningitis: A
1School of Clinical Medicine, Shandong Second Medical University, Weifang, China.

Rationale:
Anti-neutrophil cytoplasmic antibody-associated vasculitis (AAV) is a group of small-vessel necrotizing vasculitides with minimal immune complex deposition. Hypertrophic cranial pachymeningitis, a rare complication of AAV, is characterized by focal/diffuse dural thickening and fibrosis, causing neurological dysfunction such as headache and optic nerve injury. While AAV-associated hypertrophic cranial pachymeningitis is well documented, reports of concurrent spinal dural involvement remain scarce. This case highlights the rare co-occurrence of cranial and spinal dural involvement in AAV, providing new clinical evidence to expand the understanding of AAV-related dural manifestations and improve diagnostic awareness among clinicians.
Patient Concerns:
A 57-year-old male presented with fever, headache, otalgia, and hearing loss, and was diagnosed with granulomatosis with polyangiitis based on positive anti-proteinase 3 antibodies (664.3), cytoplasmic anti-neutrophil cytoplasmic antibody (1:10). Symptoms resolved with glucocorticoids, disease-modifying antirheumatic drugs, and anti-infective therapy. He later developed recurrent headache and lumbodorsal pain.
Diagnoses:
Thoracic magnetic resonance imaging (MRI) revealed a T10 to 12 epidural lesion, which was surgically resected. Pathology confirmed epidural vasculitis with necrotic/fibrous tissue, granulation, and inflammatory cell infiltration. Methylprednisolone and cyclophosphamide relieved back pain, but headaches persisted. Cranial MRI showed dural thickening in the cerebellar, posterior fossa, and foramen magnum regions, consistent with pachymeningitis. Cerebrospinal fluid analysis showed elevated mononuclear cells (35.00 × 10⁶/L), nucleated cells (40.00 × 10⁶/L), and protein (1.49 g/L), with negative cultures. The final diagnosis was granulomatosis with polyangiitis complicated by concurrent cranial and spinal dural involvement.
Interventions:
Initial management included glucocorticoids, disease-modifying antirheumatic drugs, and anti-infective therapy, which resolved the patient's fever, otalgia, and hearing loss. Surgical resection was performed for the T10 to 12 epidural lesion, followed by immunosuppressive therapy with methylprednisolone and cyclophosphamide. After adjustment of the treatment regimen, the patient's headache improved.
Outcomes:
Initial therapy resolved the patient's fever, otalgia, and hearing loss. Surgical resection combined with immunosuppressive therapy relieved lumbodorsal pain but failed to resolve headaches initially; cranial MRI confirmed pachymeningitis, and cerebrospinal fluid analysis indicated inflammatory changes. After adjustment of the treatment regimen, the patient's headache improved, and he has remained clinically stable during follow-up.
Lessons:
This case demonstrates that AAV can involve both cranial and spinal dura mater. Clinicians should consider dural involvement in AAV patients presenting with lumbodorsal pain.
More Related Videos
Related Concept Videos
 01:22
Bacterial Meningitis I: Introduction
 01:26
Brain Abscess l: Introduction
 01:19
Cranial and Spinal Meninges
Cranial Meninges
These meningeal layers cover the cranium. The dura mater is the outermost layer of cranial meninges. It is a thick and durable membrane of dense...
 01:18
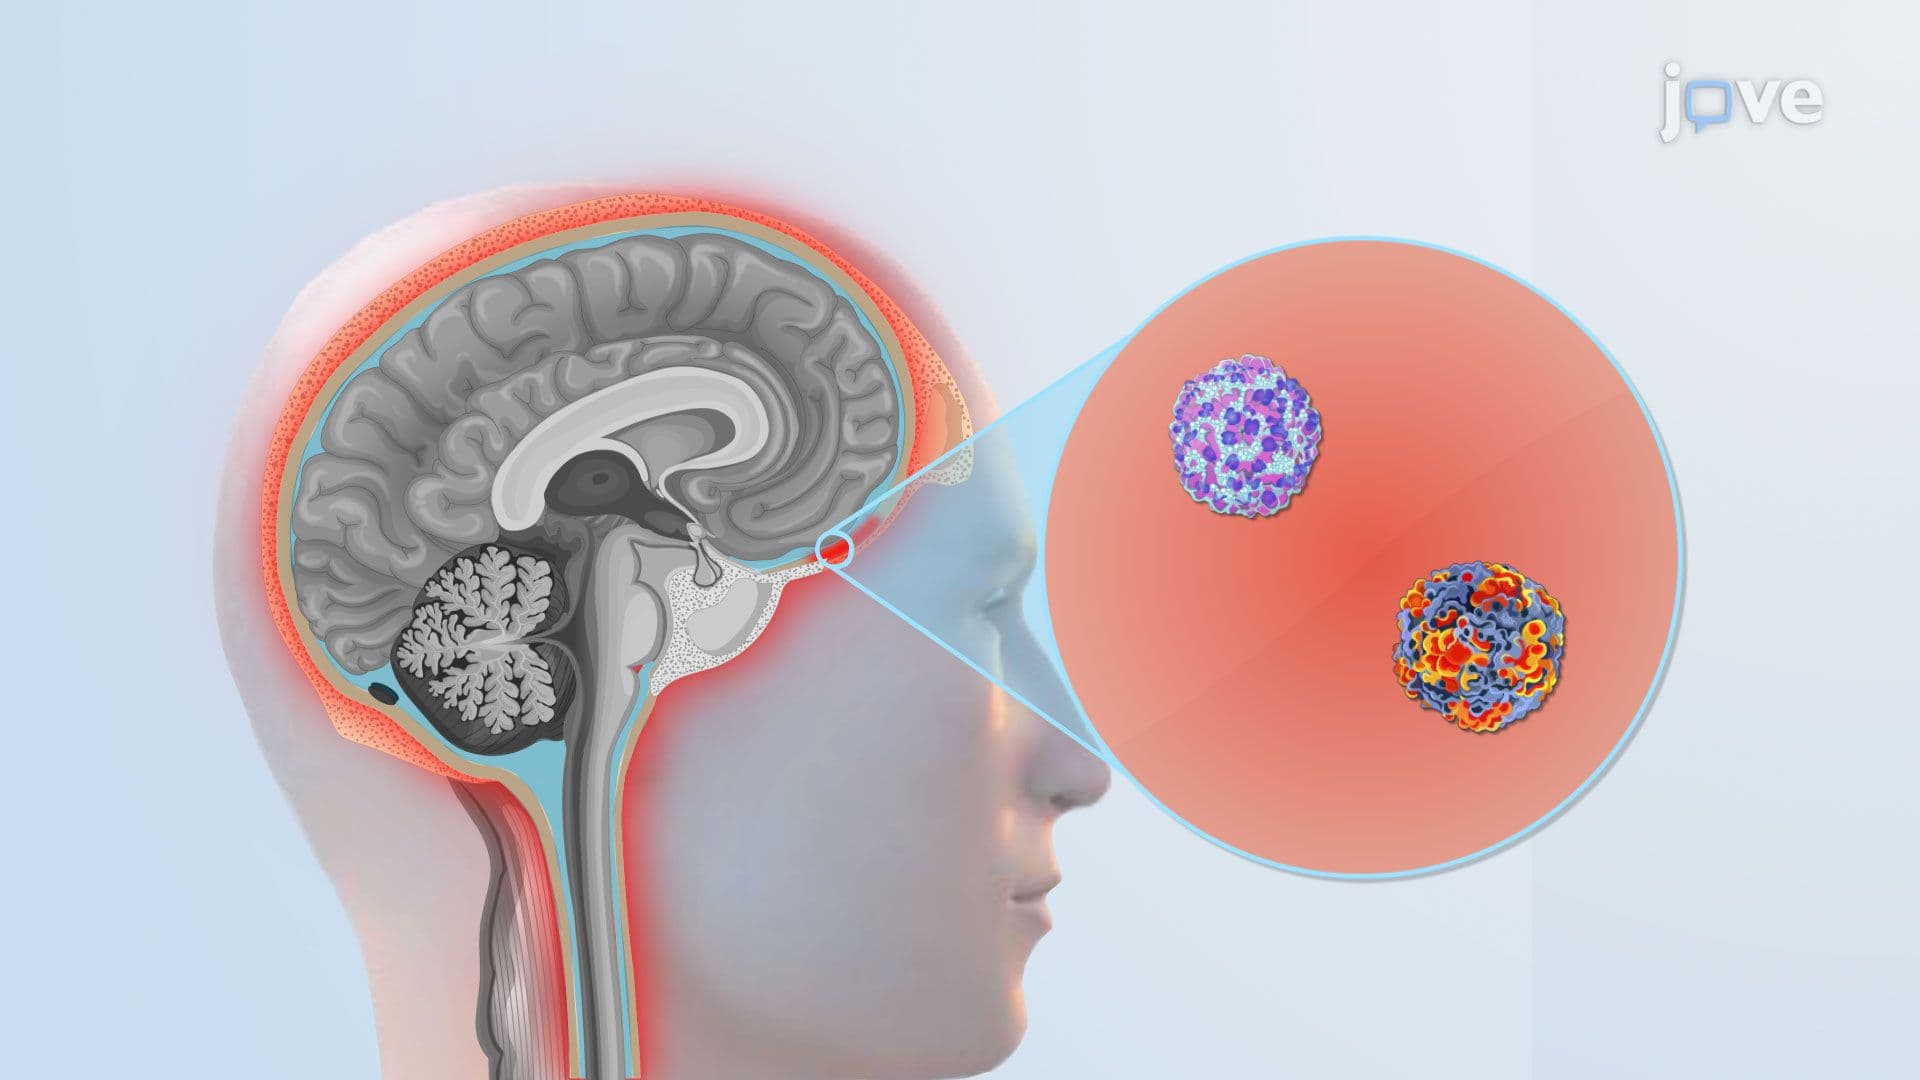
Viral Meningitis
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:30
Aneurysm I: Introduction