Related Experiment Video
Updated: May 5, 2026


Real-Time Cardiac Mapping with a Noninvasive Imageless Electrocardiographic Imaging System
Published on: April 11, 2025
Potential of R Wave in aVL Lead in Cardiovascular Risk Assessment
Juraj Jug1,2, Martina Lovrić Benčić2,3, Tomislav Bulum2,4
1Family Medicine Department, Health Center Zagreb-West, 10000 Zagreb, Croatia.

Insights
R wave amplitude in the aVL ECG lead (RaVL) is a valuable marker for cardiovascular risk and target organ damage in arterial hypertension. A threshold of RaVL > 0.40 mV indicates high cardiovascular risk, comparable to the SCORE 2 model.
Area of Science:
- Cardiology
- Hypertension Research
- Electrocardiography
Background:
- R wave amplitude in the aVL ECG lead (RaVL) is linked to cardiovascular risk, target organ damage, and mortality in arterial hypertension.
- While RaVL > 1.1 mV suggests left ventricular hypertrophy, the precise threshold for identifying high-risk patients remains undetermined.
- This study investigates RaVL in relation to hypertensive urgencies and compares its prognostic value with the established SCORE 2 model.
Purpose of the Study:
- To compare RaVL values in hypertensive patients with and without hypertensive urgencies against healthy controls.
- To identify independent predictors of elevated RaVL.
- To evaluate the prognostic value of RaVL for cardiovascular risk stratification compared to the SCORE 2 model.
Main Methods:
- A cross-sectional study involving 339 participants: 100 with arterial hypertension and hypertensive urgency, 134 with arterial hypertension without urgency, and 105 healthy controls.
- Data collection included standard 12-lead ECG, ambulatory blood pressure monitoring, basic laboratory tests, SCORE 2 risk calculation, and pulse wave velocity (PWV) measurement.
- Participants were stratified into groups based on blood pressure monitoring results.
Main Results:
- Participants with arterial hypertension and hypertensive urgency exhibited significantly higher RaVL values (0.76 ± 0.24 mV) compared to those without urgency (0.49 ± 0.27 mV) and healthy subjects (0.22 ± 0.25 mV).
- Elevated RaVL was more prevalent in males and non-dippers.
- Independent predictors of RaVL included age, mean arterial pressure, PWV, and SCORE 2 risk. An RaVL threshold > 0.40 mV demonstrated high cardiovascular risk (58.16% sensitivity, 73.68% specificity) compared to SCORE 2.
Conclusions:
- RaVL shows significant prognostic value for cardiovascular risk stratification in patients with arterial hypertension.
- An RaVL threshold of > 0.40 mV effectively identifies high cardiovascular risk.
- Larger studies are warranted to establish a precise high-risk threshold for RaVL to enhance cardiovascular risk estimation and target organ damage detection, particularly in patients with borderline SCORE 2 risk.
Abstract:
Background: R wave amplitude in the aVL ECG lead (RaVL) has been identified as a marker of cardiovascular (CV) risk, hypertension-mediated target organ damage (HMOD), and mortality in patients with arterial hypertension (AH), where RaVL > 1.1 mV suggests left ventricular hypertrophy. However, the exact threshold for identifying high-risk patients has yet to be determined. Therefore, we compared RaVL values among hypertensive patients with and without hypertensive urgencies (HUs) and healthy subjects, aiming to identify the predictors of elevated RaVL and to compare its prognostic value with the SCORE 2 model. Methods: This cross-sectional study included 339 participants divided into three groups according to ambulatory blood pressure monitoring results: 100 patients with AH and HU from the emergency department, 134 patients with AH without HU, and 105 healthy subjects recruited from four family medicine practices. Basic laboratory parameters were determined, SCORE 2 risk was calculated, PWV was measured using oscillometry, and a standard 12-lead ECG was recorded in all participants. Results: Participants with AH and HU had the highest RaVL values compared to those with AH without HU and healthy subjects (averages of 0.76 ± 0.24 mV, 0.49 ± 0.27, 0.22 ± 0.25, respectively; p < 0.001). Significantly higher RaVL values were observed in males compared to females (0.56 ± 0.31 vs. 0.41 ± 0.34 mV; p < 0.001) and in non-dippers compared to dippers (0.56 ± 0.34 mV vs. 0.41 ± 0.31 in dippers; p < 0.001). Age, mean arterial pressure, PWV, and SCORE 2 were shown as independent predictors of RaVL. Compared with SCORE 2, individuals with RaVL > 0.40 mV had high CV risk (sensitivity of 58.16%, specificity of 73.68%; p < 0.001). Conclusions: In this study, RaVL demonstrated good prognostic value for CV risk stratification. However, larger studies are needed to determine a precise high-risk threshold to improve CV risk estimation and HMOD detection in patients with marginal SCORE 2 CV risk.
More Related Videos
 08:10
Estimating Bilateral Atrial Function by Cardiovascular Magnetic Resonance Feature Tracking in Patients with Paroxysmal Atrial Fibrillation
Published on: July 20, 2022
 06:57
Ablation of Ischemic Ventricular Tachycardia Using a Multipolar Catheter and 3-dimensional Mapping System for High-density Electro-anatomical Reconstruction
Published on: January 31, 2019
Related Concept Videos
 01:28
Electrocardiogram Fundamentals
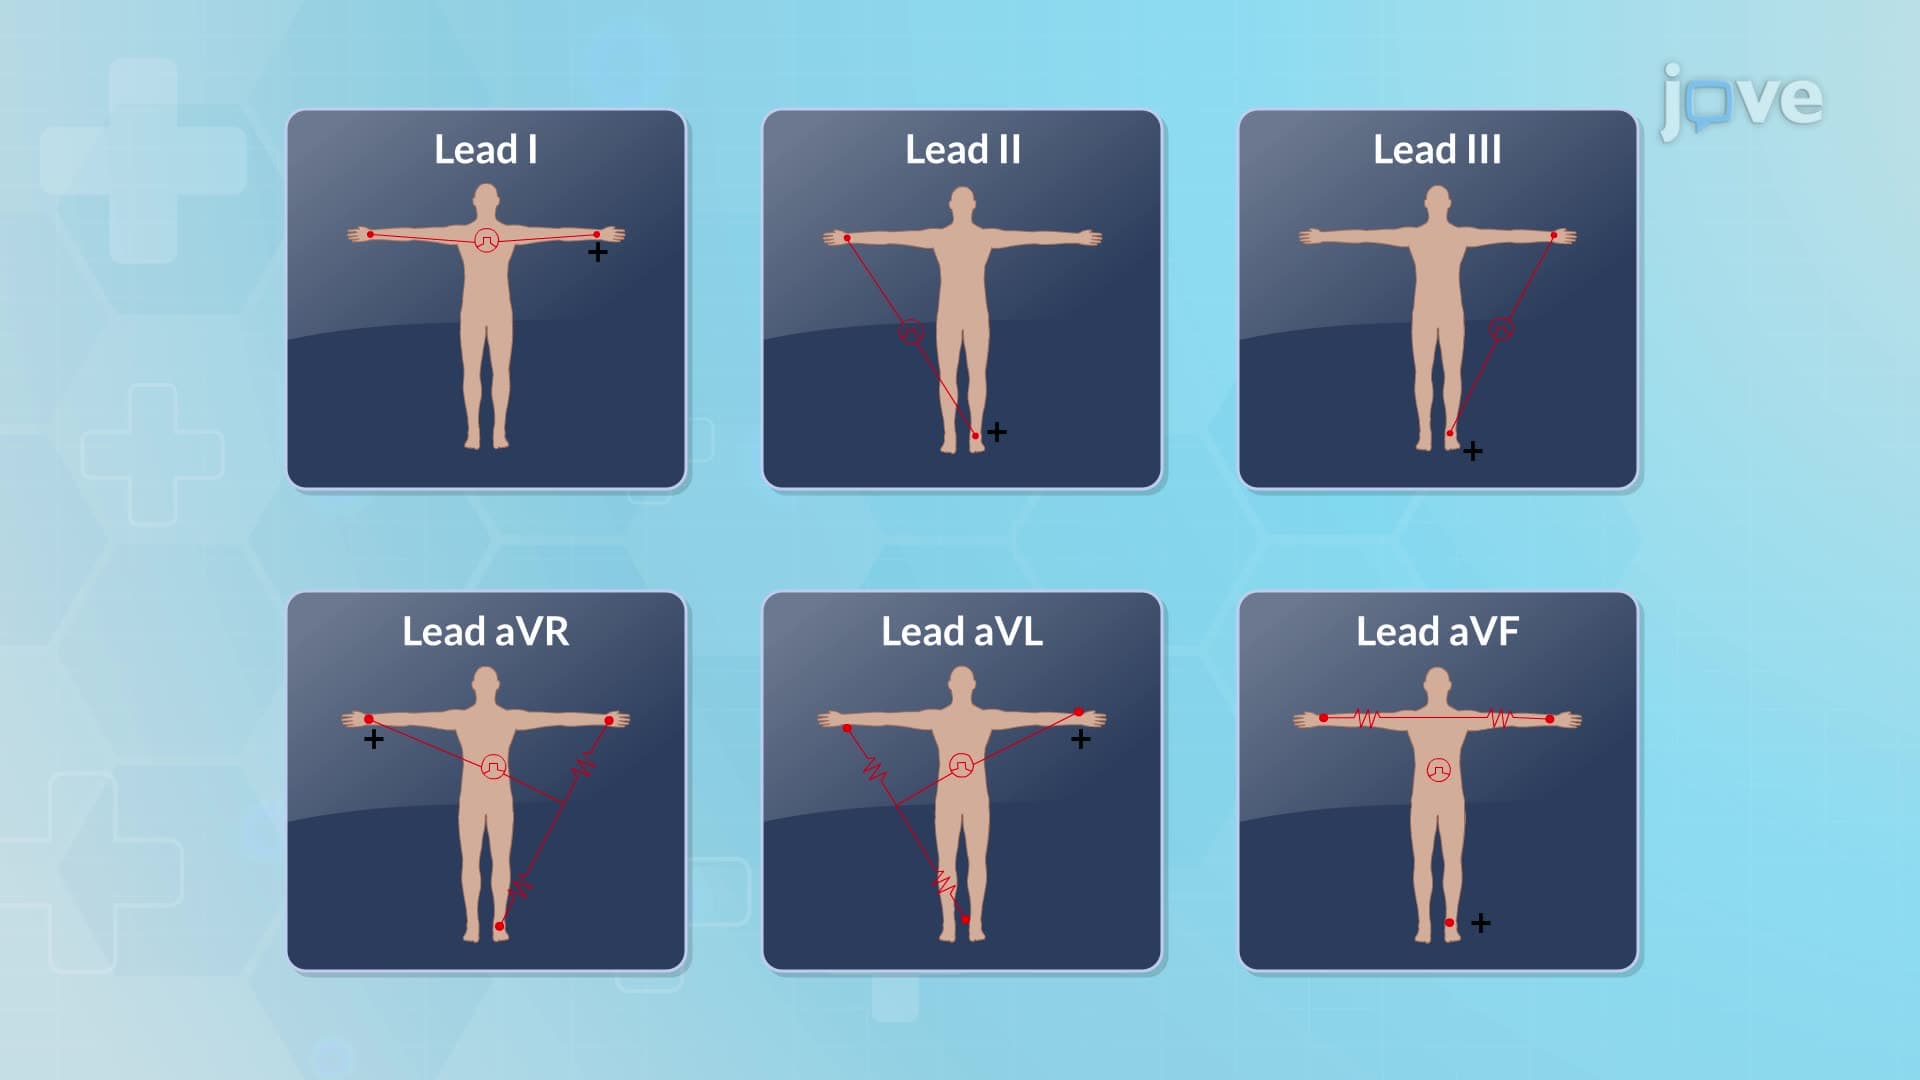
An electrocardiogram (ECG) is a diagnostic tool for identifying cardiac conditions such as arrhythmias, conduction abnormalities, and myocardial ischemia.
Definition
An electrocardiogram (ECG) visualizes the heart's electrical activity by tracing the electrical movement associated with each heartbeat on a graph or monitor. As the heart beats, an electrical wave passes through it, correlating with the cardiac cycle events.
Parts of an ECG
An ECG utilizes electrodes on the skin...
 01:25
Assessment of apical radial pulse
The A-R pulse assessment involves simultaneous evaluation of the apical and radial pulses. When the apical and radial pulse rates vary, this assessment helps identify a pulse deficit.
Pre-Procedural Preparation
 01:17
Assessment of apical pulse
Assessing the apical pulse is a critical nursing procedure, particularly indicated for:
 01:15
Aortic Regurgitation I: Introduction
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:25
Assessment of the Cardiovascular System IV: Auscultation
Normal Heart Sounds
S1 (First Heart Sound)-
S1 is made by the closure of the mitral and tricuspid valves (atrioventricular valves), marking the beginning of systole.
S2 (Second Heart Sound)-
S2 is made by the closure of the aortic and pulmonic valves (semilunar valves), marking the end of the systole.