Related Experiment Video
Updated: May 5, 2026
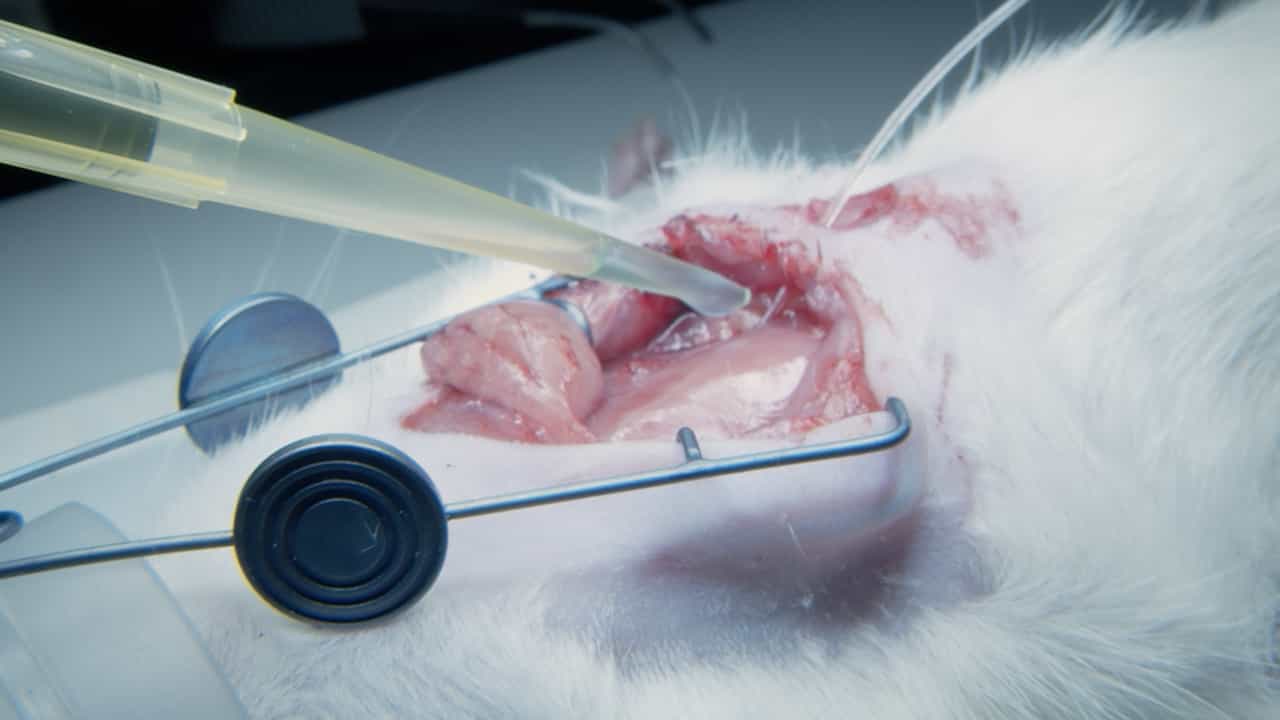

Cervical Lymph Duct-Cannulated Rat Model for Assessing Lymphatic Transport from the Head and Brain
Published on: March 10, 2026
Brain Lymphatic Dysfunction in Subarachnoid Hemorrhage: Pathophysiology and Clinical Implications
Shuangyi Guo1,2, John H Zhang2,3, Warren Boling3
1Department of Neurosurgery, Taihe Hospital, Hubei University of Medicine, Shiyan 442000, China.

Aneurysmal subarachnoid hemorrhage (SAH) remains a devastating cerebrovascular disorder with high morbidity and mortality, despite advances in aneurysm securing and neurocritical care. Clinical outcomes are determined by early brain injury (EBI), delayed cerebral ischemia (DCI), hydrocephalus, and long-term cognitive impairment, extending beyond the traditional focus on large-vessel vasospasm alone. Emerging evidence identifies the dysfunction of the glymphatic system and meningeal lymphatic pathway, the brain's primary clearance pathways, as a central and unifying mechanism linking acute hemorrhagic injury to delayed and chronic neurological sequelae. Following SAH, acute intracranial pressure elevation, subarachnoid blood clot burden, loss of arterial pulsatility, venous congestion, astrocytic aquaporin-4 perivascular depolarization, and neuroinflammation converge to suppress cerebrospinal fluid-interstitial fluid exchange and outflow in glymphatic system and subsequent meningeal lymphatic drainage. Persistent clearance failure promotes the retention of blood breakdown products, inflammatory mediators, and metabolic waste, amplifying microvascular dysfunction, cortical spreading depolarizations, blood-brain barrier disruption, and secondary ischemic injury. Importantly, accumulating data highlight venous pathology and meningeal lymphatic impairment as critical, yet underappreciated, contributors to delayed injury and post-SAH hydrocephalus. In this review, we synthesize the current knowledge of the physiological organization of glymphatic and meningeal lymphatic systems, delineate the mechanistic and molecular drivers of their dysfunction after SAH, and discuss clinical implications for EBI, DCI, hydrocephalus, and long-term cognitive outcomes. We further outline future directions, including translational imaging, biomarker development, and therapeutic strategies targeting clearance pathways, to advance disease-modifying approaches in SAH.
Aneurysmal subarachnoid hemorrhage (SAH) remains a devastating cerebrovascular disorder with high morbidity and mortality, despite advances in aneurysm securing and neurocritical care. Clinical outcomes are determined by early brain injury (EBI), delayed cerebral ischemia (DCI), hydrocephalus, and long-term cognitive impairment, extending beyond the traditional focus on large-vessel vasospasm alone. Emerging evidence identifies the dysfunction of the glymphatic system and meningeal lymphatic pathway, the brain's primary clearance pathways, as a central and unifying mechanism linking acute hemorrhagic injury to delayed and chronic neurological sequelae. Following SAH, acute intracranial pressure elevation, subarachnoid blood clot burden, loss of arterial pulsatility, venous congestion, astrocytic aquaporin-4 perivascular depolarization, and neuroinflammation converge to suppress cerebrospinal fluid-interstitial fluid exchange and outflow in glymphatic system and subsequent meningeal lymphatic drainage. Persistent clearance failure promotes the retention of blood breakdown products, inflammatory mediators, and metabolic waste, amplifying microvascular dysfunction, cortical spreading depolarizations, blood-brain barrier disruption, and secondary ischemic injury. Importantly, accumulating data highlight venous pathology and meningeal lymphatic impairment as critical, yet underappreciated, contributors to delayed injury and post-SAH hydrocephalus. In this review, we synthesize the current knowledge of the physiological organization of glymphatic and meningeal lymphatic systems, delineate the mechanistic and molecular drivers of their dysfunction after SAH, and discuss clinical implications for EBI, DCI, hydrocephalus, and long-term cognitive outcomes. We further outline future directions, including translational imaging, biomarker development, and therapeutic strategies targeting clearance pathways, to advance disease-modifying approaches in SAH.
More Related Videos


Related Concept Videos
 01:29
Hemorrhagic Stroke ll: Pathophysiology
 01:17
Hemorrhagic Stroke l: Introduction
 01:22
Cerebral Edema ll: Pathophysiology
 01:26
Bacterial Meningitis II: Pathophysiology
 01:26
Brain Abscess l: Introduction
 01:25
Secondary Spinal Cord Injury llI: Pathophysiology