Related Experiment Video
Updated: May 5, 2026
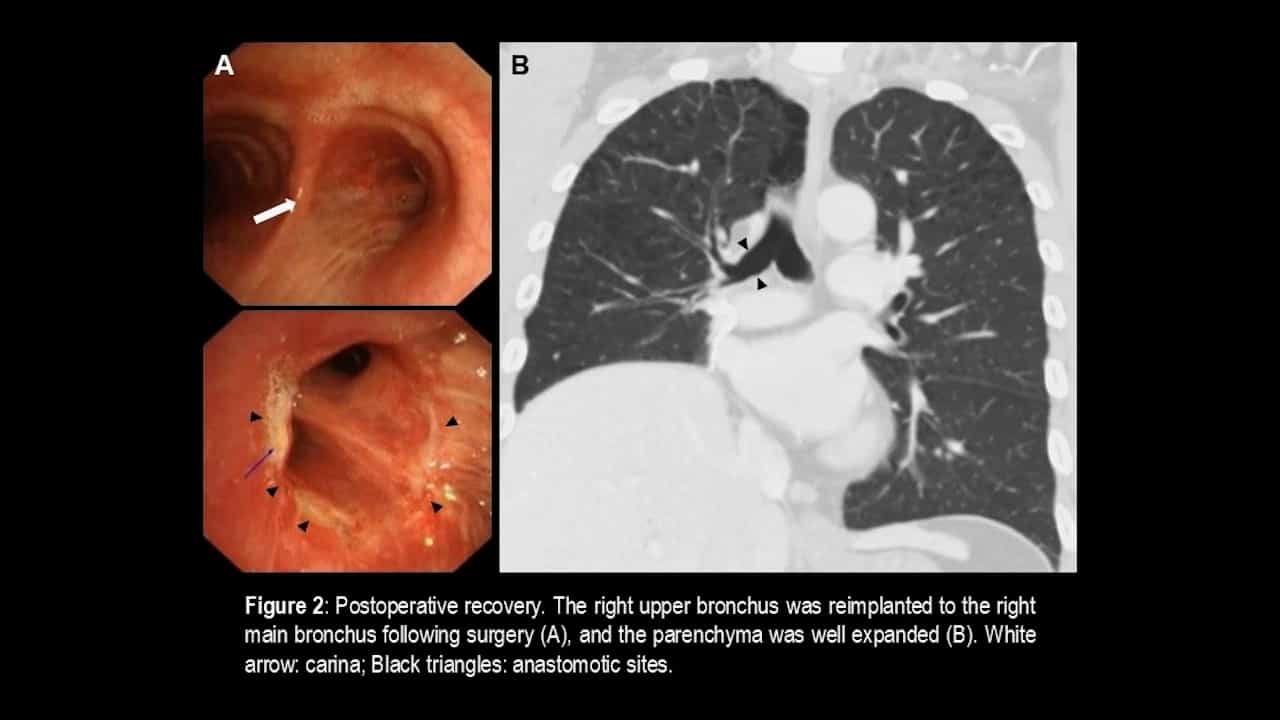
Thoracoscopic Extended Right Middle Plus Lower Sleeve Lobectomy for Non-Small-Cell Lung Cancer
Published on: February 27, 2026
Segmentectomy Versus Lobectomy in Patients with Stage IA Lung Adenocarcinoma: Long-Term Survival in a Propensity
Zhangfeng Huang1, Tenglong Luo2, Zuhan Geng1
1Department of Thoracic Surgery, Union Hospital, Tongji Medical College, Huazhong University of Science and Technology, Wuhan 430022, China.

Abstract:
Background: Whether there are differences in clinical outcomes between segmentectomy and lobectomy in patients with early-stage lung adenocarcinoma (LUAD) remains uncertain. This study aimed to compare all-cause mortality and lung cancer-specific mortality in patients with lung tumors ≤ 20 mm undergoing these two procedures. Methods: Patients with stage IA lung adenocarcinoma (≤20 mm) who underwent segmentectomy or lobectomy were identified from the SEER database (2008-2022). Propensity score matching (PSM) was applied to balance baseline characteristics. Kaplan-Meier curves depicted overall survival and lung cancer-specific survival. Multivariable Cox proportional hazards models were used to evaluate associations between surgical procedures and mortality, reporting hazard ratios (HRs) with 95% confidence intervals (CIs). Results: Among 9641 patients, 1065 (11.0%) underwent segmentectomy. After 1:1 PSM, 2028 patients had well-balanced covariates. The median follow-up was 43.0 months. In the lobectomy group, 158 all-cause deaths (35.1 per 1000 person-years) and 66 lung cancer-specific deaths (14.7 per 1000 person-years) occurred, compared with 176 and 80 events in the segmentectomy group (39.9 and 18.1 per 1000 person-years, respectively). Multivariable Cox regression demonstrated that segmentectomy, compared with lobectomy, was not associated with a higher risk of all-cause mortality (adjusted HR [aHR], 1.07, 95% CI 0.86-1.34) or lung cancer-specific mortality (aHR, 1.18, 95% CI 0.84-1.64). The results were consistent across tumor differentiation subgroups. Conclusions: Among patients with early-stage (≤20 mm) LUAD, segmentectomy was not associated with an increased risk of all-cause or lung cancer-specific mortality compared with lobectomy. Further studies with larger sample sizes are warranted to validate these findings.