Related Experiment Video
Updated: May 5, 2026


Author Spotlight: Advancements in Retroperitoneal Approach for Necrotizing Pancreatitis
Published on: March 15, 2024
Acute Pancreatitis in Pregnancy and the Early Postpartum Period: An Anaesthesiology and Critical Care Perspective
Krisztina Tóth1, Zsombor Márton2, Csaba Csontos1
1Department of Anaesthesiology and Intensive Therapy, University of Pécs Medical School, 7624 Pécs, Hungary.

Background/Objectives: Acute pancreatitis in pregnancy and the early postpartum period (APIP) is an uncommon but potentially life-threatening condition associated with significant maternal morbidity. Physiological adaptations of pregnancy, recent obstetric surgery, and overlapping postoperative symptoms frequently obscure early diagnosis and complicate perioperative and critical care management. This review provides a clinically oriented, anaesthesiology-focused overview of APIP, integrating current evidence with perioperative decision-making, pain management strategies, and intensive care considerations relevant to obstetric practice. Methods: A narrative, clinically structured review of the literature was performed focusing on epidemiology, aetiology, diagnosis, severity stratification, and management of APIP. Anaesthesiology- and ICU-specific aspects are synthesised into a pragmatic management framework. Results: Gallstone disease and hypertriglyceridaemia remain the predominant causes of APIP, with most cases occurring in the third trimester or early postpartum period. Diagnosis relies on pancreatic enzyme elevation and pregnancy-adapted imaging strategies. Early goal-directed fluid resuscitation, effective multimodal analgesia, and timely initiation of enteral nutrition are key determinants of outcome. Therapeutic ERCP and laparoscopic cholecystectomy can be safely performed during pregnancy when clinically indicated and may reduce recurrence in biliary pancreatitis. Neuraxial analgesia provides effective, opioid-sparing pain control and may improve respiratory mechanics and haemodynamic stability. Persistent organ failure remains the strongest predictor of adverse outcome and should prompt early intensive care admission. Conclusions: APIP requires early recognition and severity-adapted, multidisciplinary management. Anaesthesiology-led strategies play a central role in optimising analgesia, haemodynamic stability, and timely escalation of care. Framing APIP within a perioperative and critical care context may improve maternal outcomes in this vulnerable patient population.
Background/Objectives: Acute pancreatitis in pregnancy and the early postpartum period (APIP) is an uncommon but potentially life-threatening condition associated with significant maternal morbidity. Physiological adaptations of pregnancy, recent obstetric surgery, and overlapping postoperative symptoms frequently obscure early diagnosis and complicate perioperative and critical care management. This review provides a clinically oriented, anaesthesiology-focused overview of APIP, integrating current evidence with perioperative decision-making, pain management strategies, and intensive care considerations relevant to obstetric practice. Methods: A narrative, clinically structured review of the literature was performed focusing on epidemiology, aetiology, diagnosis, severity stratification, and management of APIP. Anaesthesiology- and ICU-specific aspects are synthesised into a pragmatic management framework. Results: Gallstone disease and hypertriglyceridaemia remain the predominant causes of APIP, with most cases occurring in the third trimester or early postpartum period. Diagnosis relies on pancreatic enzyme elevation and pregnancy-adapted imaging strategies. Early goal-directed fluid resuscitation, effective multimodal analgesia, and timely initiation of enteral nutrition are key determinants of outcome. Therapeutic ERCP and laparoscopic cholecystectomy can be safely performed during pregnancy when clinically indicated and may reduce recurrence in biliary pancreatitis. Neuraxial analgesia provides effective, opioid-sparing pain control and may improve respiratory mechanics and haemodynamic stability. Persistent organ failure remains the strongest predictor of adverse outcome and should prompt early intensive care admission. Conclusions: APIP requires early recognition and severity-adapted, multidisciplinary management. Anaesthesiology-led strategies play a central role in optimising analgesia, haemodynamic stability, and timely escalation of care. Framing APIP within a perioperative and critical care context may improve maternal outcomes in this vulnerable patient population.
More Related Videos
 07:38
Preparing a Mice Model of Severe Acute Pancreatitis via a Combination of Caerulein and Lipopolysaccharide Intraperitoneal Injection
Published on: May 10, 2024
 07:10
Establishment of a Mouse Severe Acute Pancreatitis Model using Retrograde Injection of Sodium Taurocholate into the Biliopancreatic Duct
Published on: April 1, 2022
Related Concept Videos
 01:30
Acute Pancreatitis II: Clinical Manifestations and Management
 01:25
Acute Pancreatitis I: Introduction
 01:27
Acute Pancreatitis I: Introduction
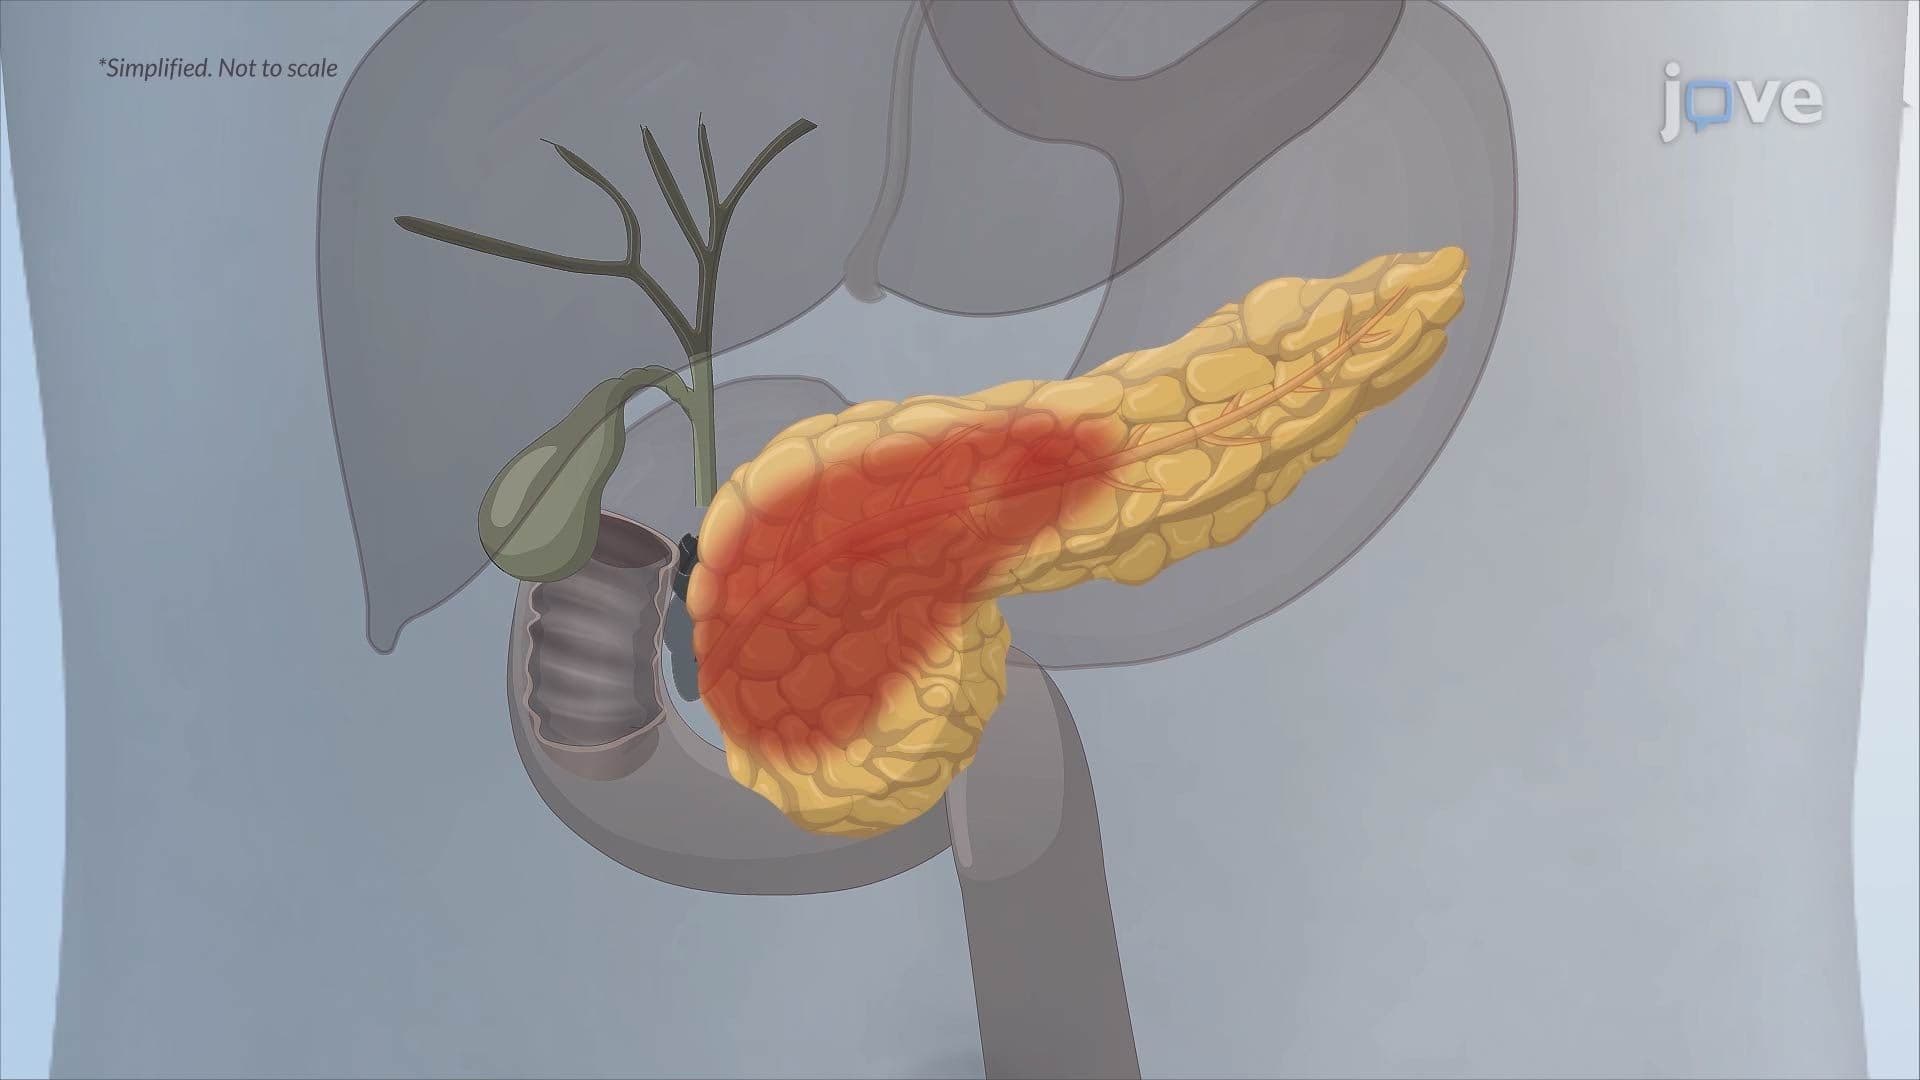
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include:
 01:21
Acute Pancreatitis II: Pathophysiology
 01:29
Chronic Pancreatitis II: Collaborative Care
Assessment:
 01:25
Chronic Pancreatitis I: Introduction