Related Experiment Video
Updated: May 6, 2026


Novel and Innovative Hybrid Technique for Type A Aortic Dissection
Published on: March 28, 2025
Cardiac POCUS in Undifferentiated Shock Revealing Aortic Dissection
Issac Cheong1,2, Javier Arrinda3, Pablo Martín Merlo2
1Department of Critical Care Medicine, Sanatorio de Los Arcos, Buenos Aires, Argentina.

Abstract:
Acute aortic dissection is a medical emergency requiring prompt diagnosis and intervention. Mortality in untreated Stanford type A dissection increases approximately 2.6% per hour during the first 24 h and may reach 47%-55% within 24-48 h. In critically ill patients, point-of-care ultrasound has emerged as a valuable bedside tool, particularly when conventional imaging is delayed or contraindicated. We describe the case of a 43-year-old man with Marfan syndrome, prior ascending aortic replacement with a Dacron graft (without aortic valve replacement), intellectual disability, psychiatric disorders, hypertension, dyslipidemia, hypothyroidism, and a known descending aortic aneurysm. He was transferred from a rehabilitation center to the intensive care unit due to hypotension. A non-contrast thoracic CT scan had been performed in the emergency department prior to ICU admission because of a documented severe allergy to iodinated contrast media. Upon ICU arrival, he was in shock and required mechanical ventilation and vasopressor support. Parasternal windows were not interpretable due to poor acoustic quality; suprasternal and abdominal aortic views were attempted but not feasible. However, apical five- and three-chamber transthoracic views revealed a markedly dilated ascending aorta and a mobile thin intimal flap distal to the aortic valve. Color Doppler demonstrated differential flow patterns consistent with true and false lumens and moderate-to-severe aortic regurgitation. These findings were highly suggestive of Stanford type A aortic dissection. Given the unequivocal transthoracic findings, transesophageal echocardiography was not performed in order to avoid further delay, and the patient was urgently transferred to a cardiac surgery center for definitive management. Clinical outcome after transfer remains unknown. This case highlights the diagnostic value of focused cardiac ultrasound in critically ill patients and underscores the importance of systematically assessing the proximal ascending aorta when evaluating shock, even in patients with previous aortic surgery.
Related Concept Videos
 01:22
Aortic Regurgitation II: Clinical Features and Diagnostic Tests
 01:21
Aneurysm II: Clinical Manifestations and Diagnostic Studies
 01:29
Cardiovascular System Abnormal Findings I: Inspection and Palpation
Abnormal findings observed during an inspection
 01:25
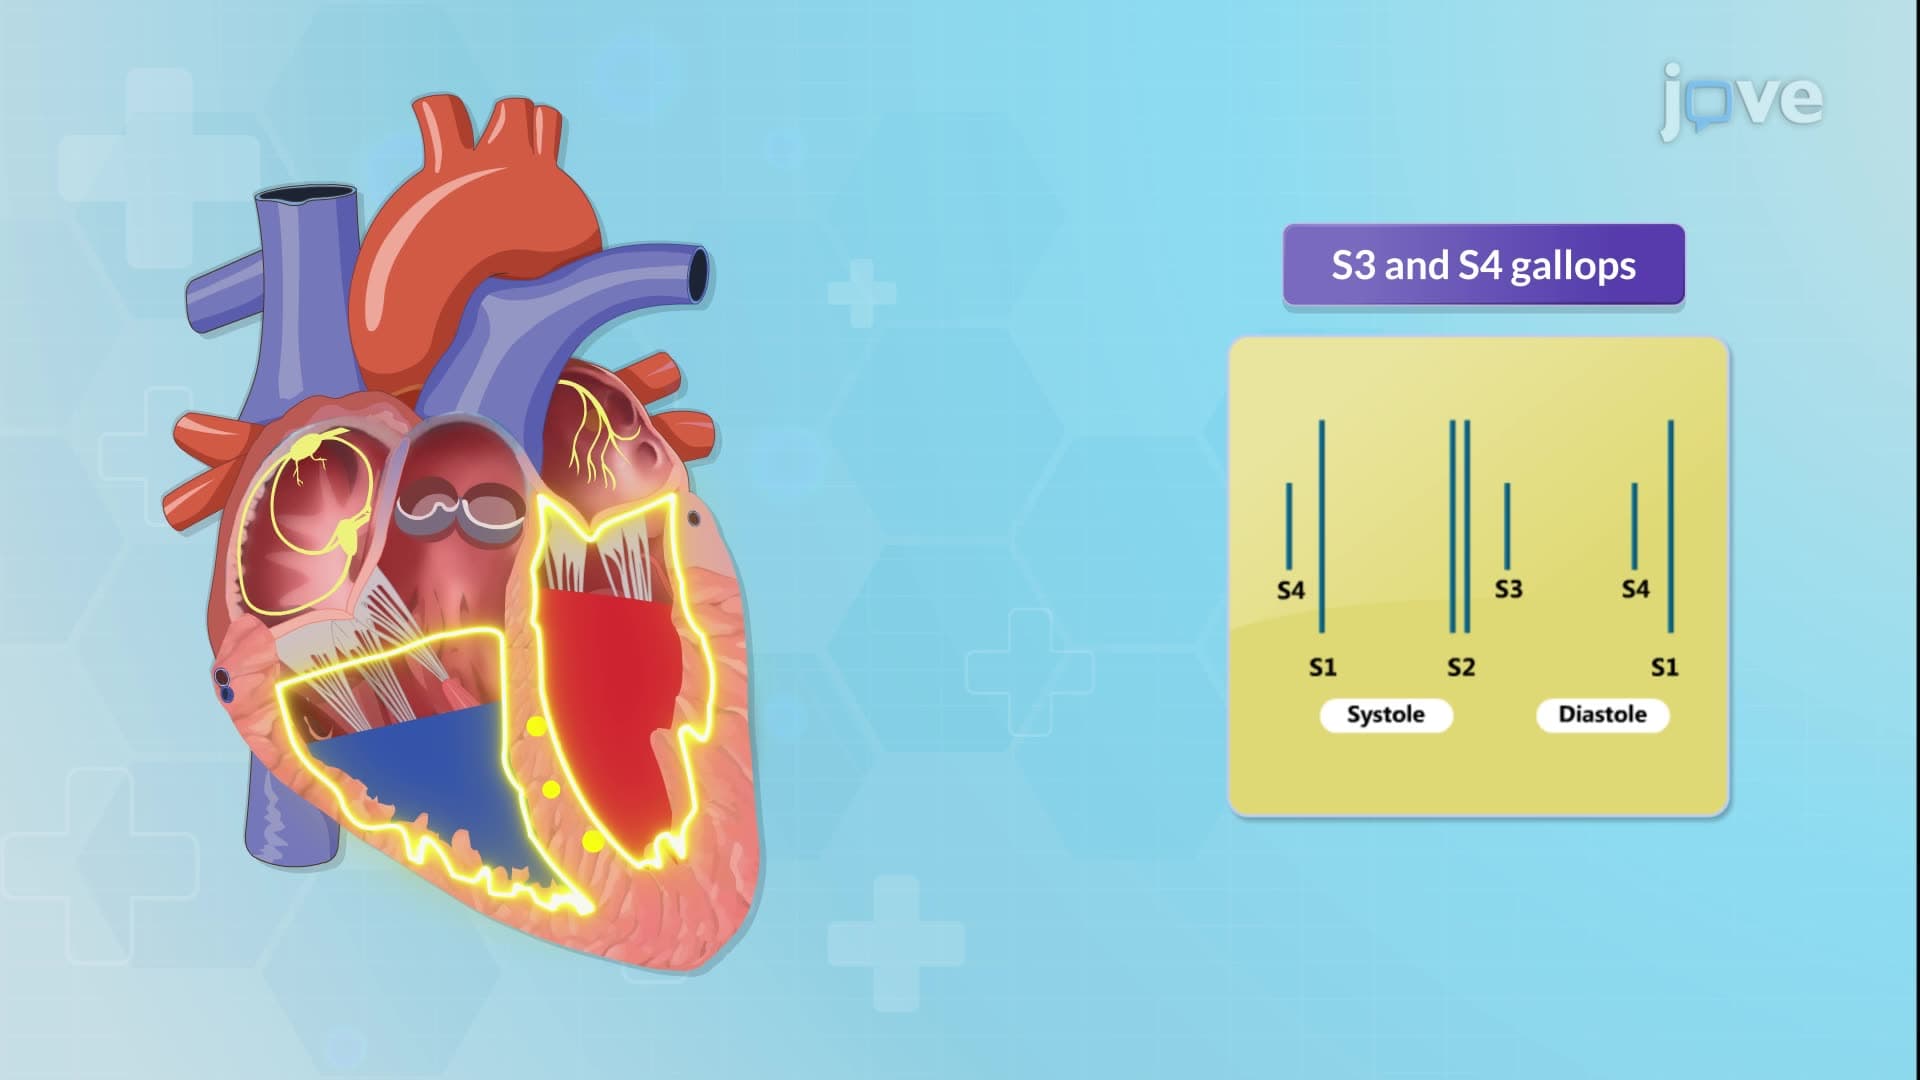
Cardiovascular System Abnormal Findings II: Auscultation
Abnormal Heart Sounds
Gallops:
 01:15
Aortic Regurgitation I: Introduction
 01:30
Aneurysm I: Introduction