Related Experiment Video
Updated: May 6, 2026

The Role of Indocyanine Green Fluorescence in Complex Laparoscopic Cholecystectomy Navigation
Published on: January 31, 2025
Thrombotic thrombocytopenic purpura associated with acalculous cholecystitis masquerading as immune thrombocytopenia
Kavya Balusu1, Purva Shah1, Nagesh Jadhav1
1Department of Internal Medicine.

Thrombotic thrombocytopenic purpura (TTP) is a potentially life-threatening condition characterized by thrombocytopenia, microangiopathic haemolytic anaemia, and end-organ ischemia. Association of TTP with acute cholecystitis is rare, with only two cases reported in literature. We report the third case of TTP associated with acute cholecystitis in an African-American female with systemic lupus erythematosus (SLE). She presented with fever and abdominal pain; laboratory testing revealed acute on chronic thrombocytopenia, and imaging confirmed acute acalculous cholecystitis. This initially led to a misdiagnosis of immune thrombocytopenia (ITP), and she was treated with antibiotics, intravenous immunoglobulin, and steroids without improvement. She subsequently developed neurological symptoms with laboratory evidence of haemolysis raising a concern for thrombotic microangiopathy. Emergent plasmapheresis was initiated for suspected TTP, resulting in improvement of her symptoms. Low ADAMTS13 activity subsequently confirmed the diagnosis. This case highlights the importance of recognizing atypical presentations of TTP to initiate prompt life-saving treatment.
Thrombotic thrombocytopenic purpura (TTP) is a potentially life-threatening condition characterized by thrombocytopenia, microangiopathic haemolytic anaemia, and end-organ ischemia. Association of TTP with acute cholecystitis is rare, with only two cases reported in literature. We report the third case of TTP associated with acute cholecystitis in an African-American female with systemic lupus erythematosus (SLE). She presented with fever and abdominal pain; laboratory testing revealed acute on chronic thrombocytopenia, and imaging confirmed acute acalculous cholecystitis. This initially led to a misdiagnosis of immune thrombocytopenia (ITP), and she was treated with antibiotics, intravenous immunoglobulin, and steroids without improvement. She subsequently developed neurological symptoms with laboratory evidence of haemolysis raising a concern for thrombotic microangiopathy. Emergent plasmapheresis was initiated for suspected TTP, resulting in improvement of her symptoms. Low ADAMTS13 activity subsequently confirmed the diagnosis. This case highlights the importance of recognizing atypical presentations of TTP to initiate prompt life-saving treatment.
Related Concept Videos
 01:20
Cholecystitis
 01:25
Acute Pancreatitis I: Introduction
 01:27
Acute Pancreatitis I: Introduction
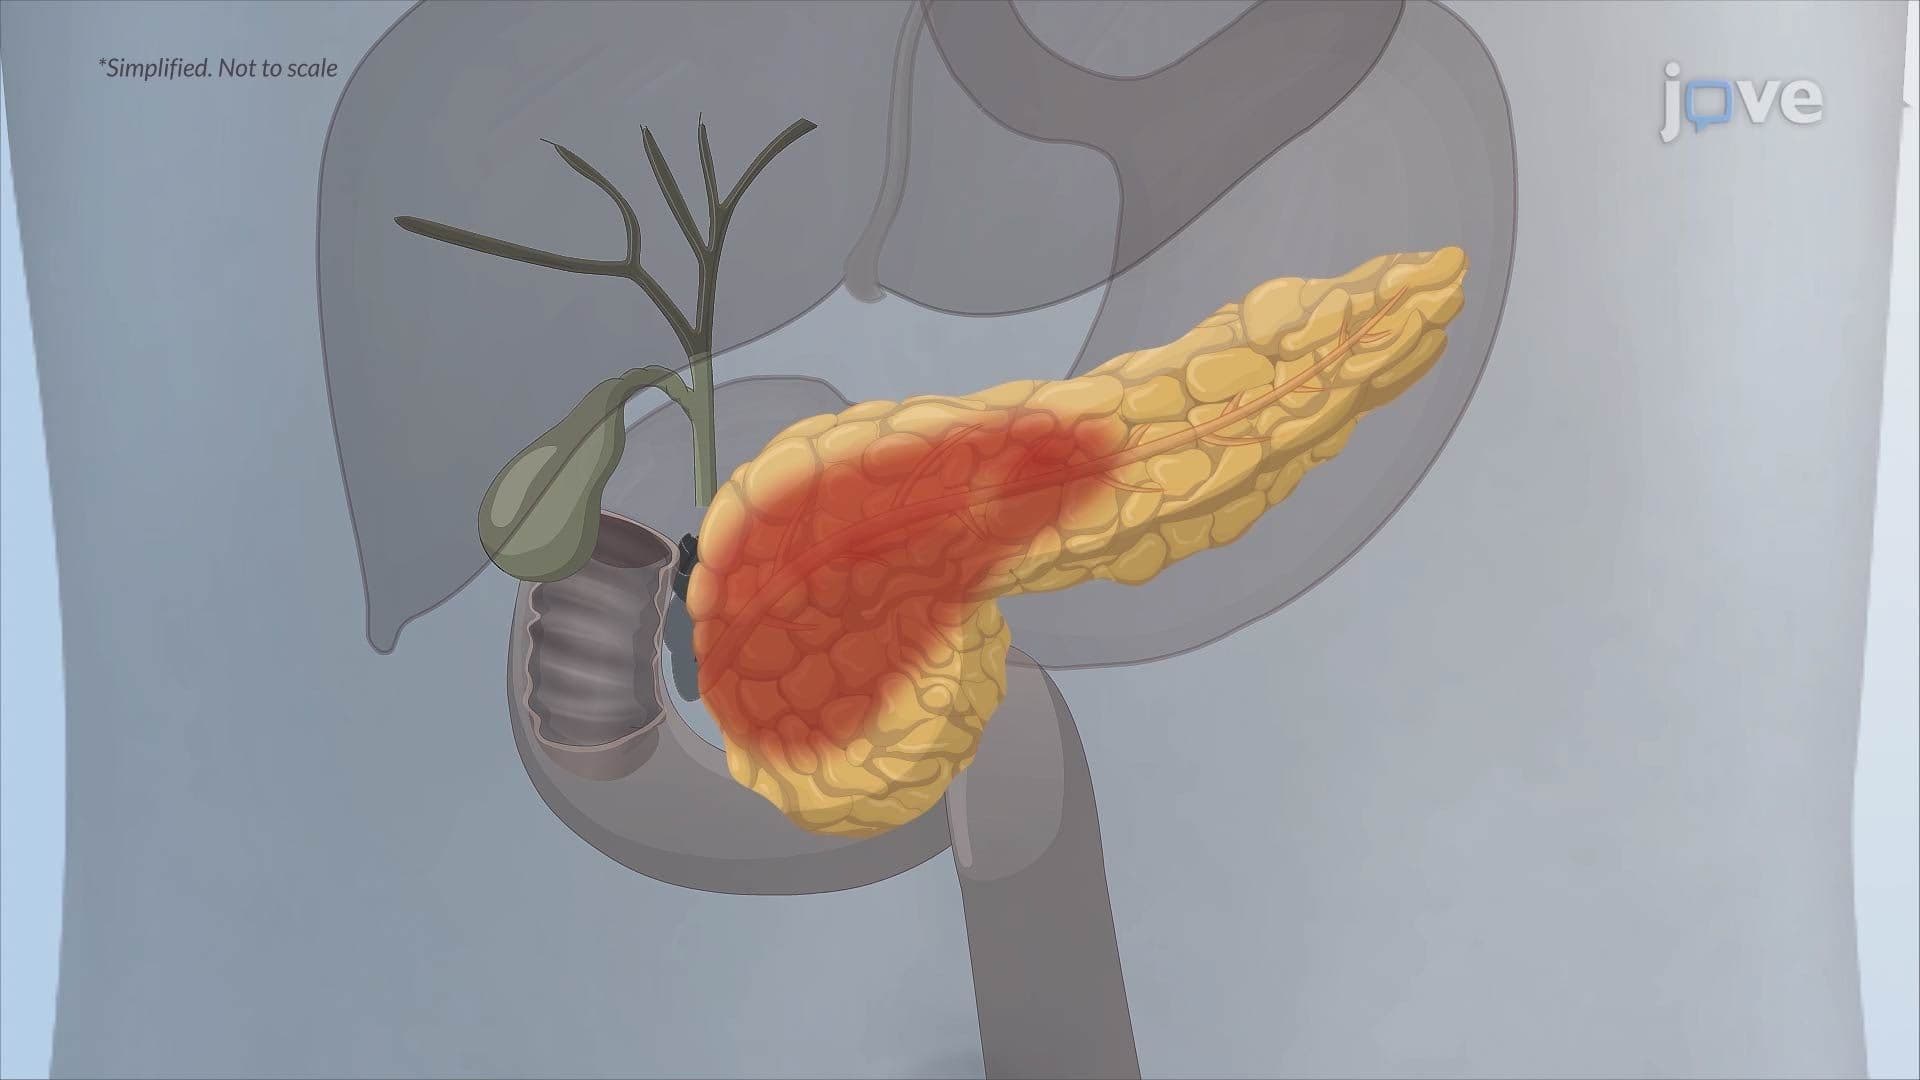
Acute pancreatitis is characterized by rapid inflammation of the pancreas, often caused by factors like gallstone blockage or excessive alcohol consumption. Chronic pancreatitis, on the other hand, is a slow, progressive inflammation that may result from long-term alcohol abuse, obstructions in the pancreatic duct, or genetic factors.
The causes of acute pancreatitis include:
 01:21
Acute Pancreatitis II: Pathophysiology
 01:19
Appendicitis
 01:25
Chronic Pancreatitis I: Introduction