Related Experiment Video
Updated: May 7, 2026

Robotic Pancreatoduodenectomy for Pancreatic Head Cancer: a Case Report of a Standardized Technique
Published on: June 24, 2022
Step-by-Step Hepatic Artery and Celiac Axis Dissection According to the Inoue Classification During Robotic
Alessia Fassari1, Francesca Marcucci2,3, Alessandro Cannavera3
1Centre Hospitalier Universitaire de Rennes, Rennes, France. alessia.fassari@gmail.com.

Insights
Robotic pancreaticoduodenectomy can safely replicate open surgery standards for celiac axis (CA) and hepatic artery (HA) dissection. This standardized robotic approach achieves all three levels of the Inoue classification, ensuring oncological safety.
Area of Science:
- Minimally Invasive Surgery
- Surgical Oncology
- Robotic Surgery
Background:
- The Inoue classification defines three levels of celiac axis (CA) and hepatic artery (HA) dissection during open pancreaticoduodenectomy (PD).
- Robotic PD adoption necessitates standardized techniques to achieve the oncological standards of open surgery.
- A clear robotic approach for all Inoue classification levels of CA-HA dissection is currently lacking.
Purpose of the Study:
- To present a stepwise robotic technique for celiac axis (CA) and hepatic artery (HA) dissection.
- To demonstrate the feasibility of achieving Inoue classification levels 1, 2, and 3 using a robotic approach.
- To provide a standardized robotic method for CA-HA dissection in pancreaticoduodenectomy (PD).
Main Methods:
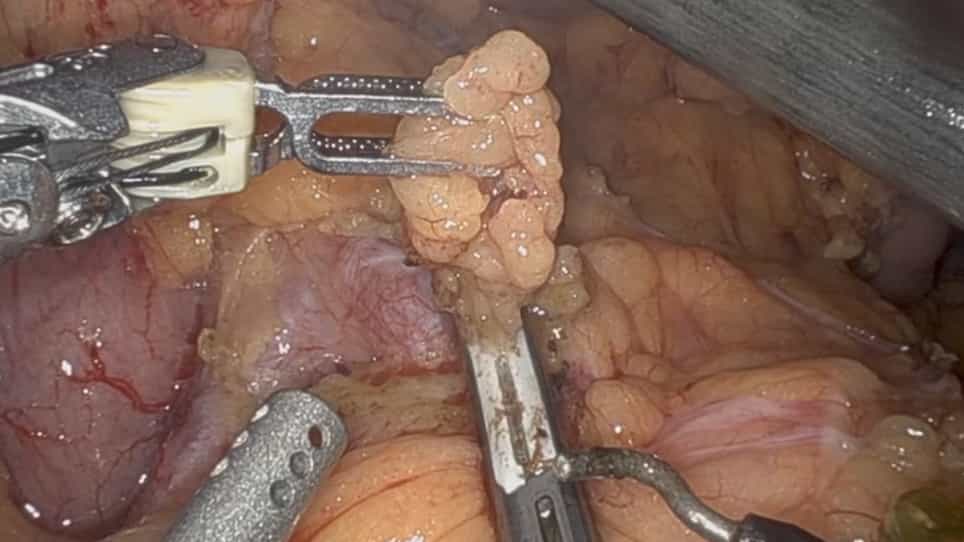
- A standardized robotic technique for graded CA-HA dissection (levels 1-3) is presented via surgical video.
- Key principles include arterial control with vessel loops, selective instrument use (monopolar scissors, Maryland bipolar forceps), and energy devices away from major arteries.
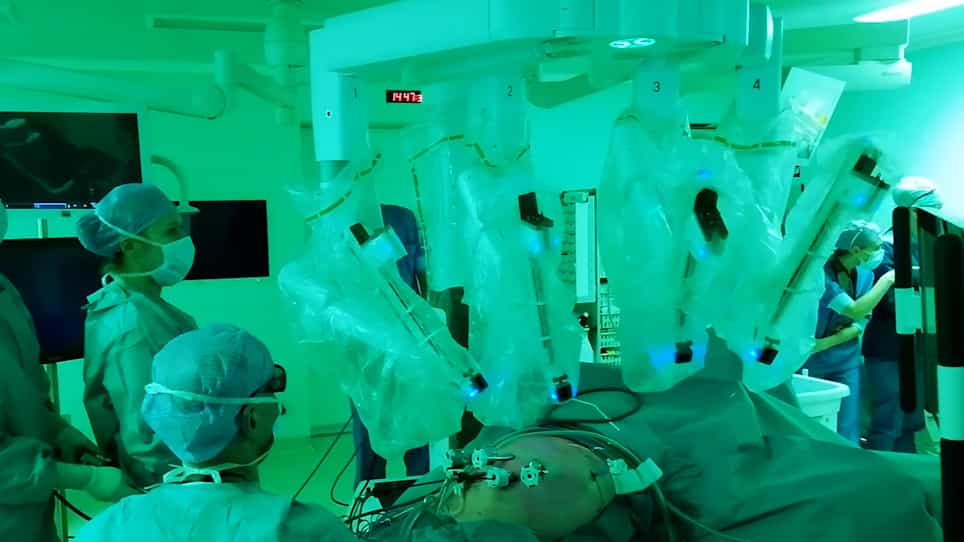
- A four-hand robotic strategy involving two experienced surgeons optimizes exposure and safety.
Main Results:
- Robotic PD successfully achieved all three levels of CA-HA dissection per the Inoue classification.
- The robotic platform provided magnified visualization and precise dissection along vascular and perineural planes.
- Advanced dissections, including perineural clearance, were performed without intraoperative arterial injury or complications.
Conclusions:
- A graded robotic dissection of the CA and HA, following the Inoue classification, is safely reproducible in PD.
- This technique supports the standardization of oncological principles in robotic pancreatic surgery.
- Robotic PD can achieve the same oncological safety as open surgery for perivascular dissection.
Background:
In 2018, Inoue et al.1 introduced a systematic classification of the extent of dissection along the celiac axis (CA) and hepatic artery (HA) during open pancreaticoduodenectomy (PD). Three levels of perivascular dissection were defined according to surgical indication: level 1, limited organ resection without oncological dissection for benign or low-grade malignant lesions; level 2, formal lymphadenectomy with preservation of the perivascular nerve plexus for borderline or low-grade malignancies; and level 3, radical dissection, including perineural clearance for pancreatic cancer. As robotic PD is increasingly adopted, it should reproduce the same oncological standards established in open surgery.2-4 However, a standardized robotic technique capable of achieving all levels of the Inoue classification has not yet been clearly described. This video article aims to present a stepwise robotic approach to CA-HA dissection consistent with these principles.
Methods:
We present a comprehensive surgical video demonstrating a standardized robotic technique to achieve graded dissection of the CA and HA from level 1 to level 3. A supplementary video specifically illustrates advanced CA-HA dissection in the setting of vascular involvement requiring resection and reconstruction. Independently of the dissection level, three constant technical principles are systematically applied: (1) arterial control through vessel loop encirclement of the HA to avoid undue manipulation; (2) a selective and stepwise use of robotic instruments according to the depth of dissection, with monopolar curved scissors used to develop the superficial planes and Maryland bipolar forceps employed for precise periadventitial skeletonization of the arterial structures, thereby minimizing mechanical and thermal injury to the arterial wall. Energy sealing devices such as the vessel sealer (Intuitive Surgical, Sunnyvale, CA, USA) are used selectively and only away from major arteries, mainly for lymphatic or venous division and for final hemostasis once lymph nodes have been mobilized from the arterial wall. Alternatively, cold dissection with scissors can be used for precise arterial divestment, as previously described by Kauffman et al.5; (3) a structured four-hand robotic strategy involving two experienced hepato-pancreato-biliary surgeons to optimize exposure and vascular safety, with one surgeon operating at the console and a second surgeon assisting at the bedside to provide dynamic retraction, suction, and vascular control.
Results:
All three levels of CA-HA dissection according to the Inoue classification were successfully achieved robotically. The robotic platform enabled stable magnified visualization and precise skeletonization along vascular and perineural planes. Advanced dissections, including circumferential perineural clearance, were feasible without intraoperative arterial injury or uncontrolled vascular complications, even during level 3 dissections or when vascular resection and reconstruction were required.
Conclusion:
A graded clearance of the CA and HA according to the Inoue classification can be safely reproduced during robotic PD, supporting standardization of oncological principles across different levels of perivascular dissection.