Related Experiment Video
Updated: May 7, 2026
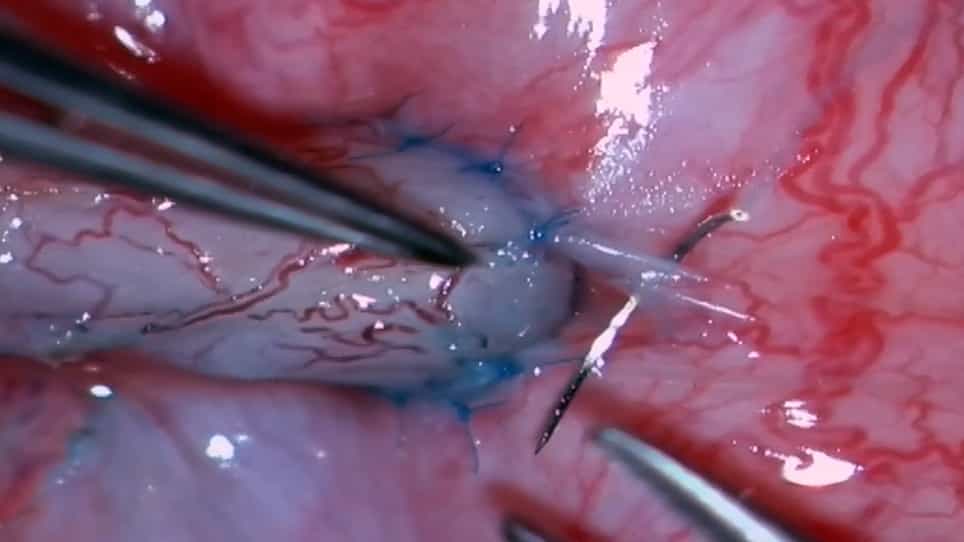

Vessel-Sparing Microsurgical Longitudinal Intussusception Vasoepididymostomy to Treat Epididymal Obstructive Azoospermia
Published on: May 27, 2022
Clomiphene citrate and human chorionic gonadotropin treatment before microdissection testicular sperm extraction in
Mohammad Al-Zubi1, Mohammad Ghassab Deameh2, Ahmed Khaled Awawdeh3
1Department of Surgery and Anesthesia, Division of Urology, Faculty of Medicine, Yarmouk University, Irbid, Jordan.

Introduction:
Infertility is defined as the inability to conceive after 12 months or longer of regular unprotected sexual intercourse. Azoospermia affects approximately 1% of men, with non-obstructive azoospermia (NOA) accounting for nearly 60% of cases. The role of hormonal treatment before microdissection testicular sperm extraction (Micro-TESE) in stimulating spermatogenesis in patients with NOA is controversial. From this standpoint, our study aimed to investigate the effect of preoperative hormonal treatment on sperm retrieval rates (SRRs) during Micro-TESE in NOA patients.
Materials And Methods:
A retrospective analysis was conducted on 152 patients who underwent Micro-TESE for NOA at our center between January 2021 and December 2023. Patients were divided into two groups. The first group included patients who received preoperative hormonal therapy consisting of clomiphene citrate (25 mg daily) and subcutaneous human chorionic gonadotropin injections (2,000 IU three times weekly) for at least 3 months prior to Micro-TESE, while the second group did not. The two groups were compared for the presence of viable sperm, age, smoking status, medical illnesses (diabetes mellitus and hypertension), hormonal profile before operation [follicle-stimulating hormone (FSH), luteinizing hormone, and total testosterone], history of undescended testes, and the presence of Klinefelter syndrome. Statistical significant was defined as p-value < 0.05.
Results:
A total of 152 NOA patients were included in this study, with 78 patients undergoing preoperative hormonal therapy and 74 patients not receiving any preoperative hormonal therapy. Results revealed no statistically significant differences in most demographic and clinical parameters between the groups. Hormonal analysis revealed a significantly lower median FSH level in the preoperative hormonal therapy group (p = 0.04). Micro-TESE outcomes were also comparable, with 50% success in the non-hormonal therapy group and 45% in the preoperative hormonal therapy group (p = 0.53).
Conclusion:
In this retrospective cohort, preoperative hormonal therapy was not associated with a statistically significant improvement in Micro-TESE sperm retrieval outcomes in NOA patients. Further studies are warranted to identify biomarkers predicting responders to preoperative hormonal stimulation.


