Removal of scleral buckle: indications, long-term outcomes and comparison with the literature
Related Experiment Video
Updated: May 8, 2026
Scleral Cross-linking Using Riboflavin and Ultraviolet-A Radiation for Prevention of Axial Myopia in a Rabbit Model
Published on: April 3, 2016
Eunice Linh You1, Sihame Doukkali1, Mélanie Hébert1
1Department of Ophthalmology, Hôpital du Saint-Sacrement, CHU de Québec - Université Laval, Quebec City, Canada.

Objective:
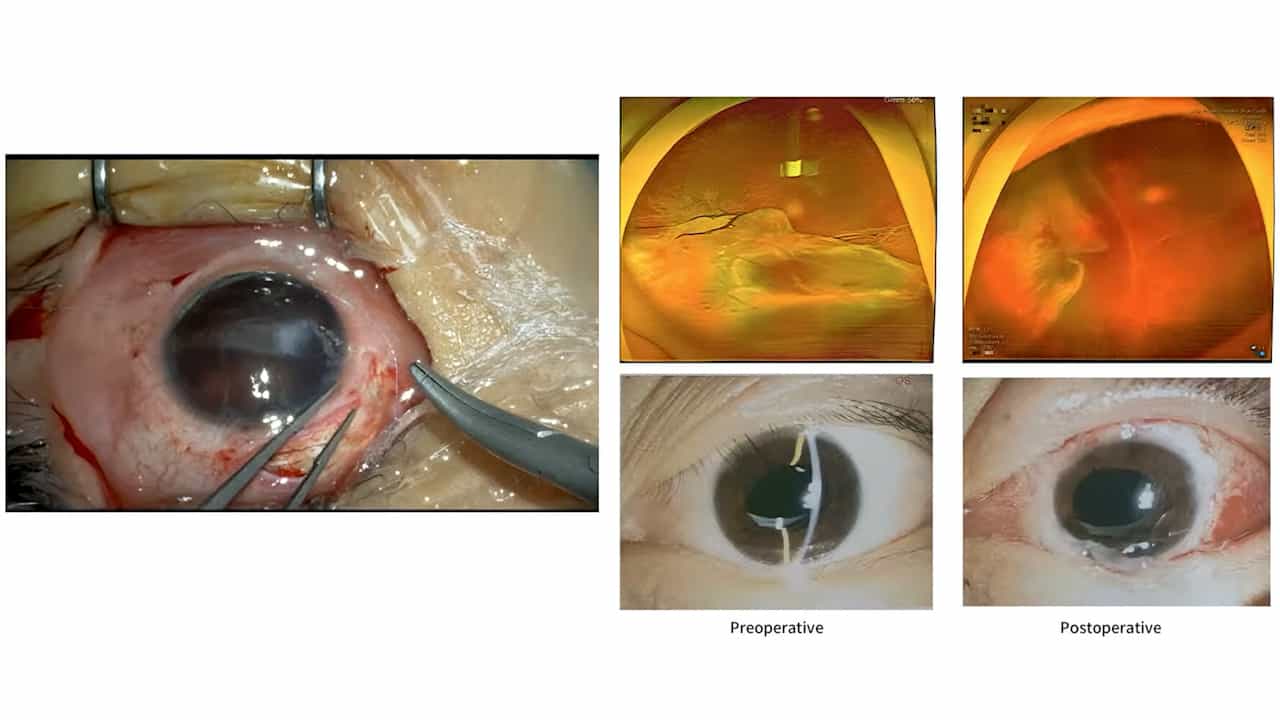
To assess the clinical indications for scleral buckle removal (SBR) and evaluate the functional and anatomic outcomes, including the risk of recurrent retinal detachment (RD) following SBR.
Design:
Retrospective chart review.
Methods:
A single-center analysis of patients operated for SBR was conducted at the Centre hospitalier universitaire de Québec - Université Laval in Quebec, Canada between 2008 and 2023 with a minimum of 1 year follow-up. Data were gathered on preoperative characteristics, indication for SBR, time to SBR, surgical techniques used and postoperative outcomes including final best-corrected visual acuity (BCVA). The primary outcome was the incidence of recurrent RD after SBR.
Results:
Among 2375 eyes that had placement of scleral buckle for RD, 35 (1.5%) required SBR. Infection (34%) and pain (31%) were the most common reasons for SBR. The median time from buckle placement to removal was significantly shorter for infectious cases (2.4 months) compared to non-infectious cases (12.6 months) (p = 0.006). Four patients (11%) experienced recurrent RD, with 3/4 of those cases occurring when buckle explantation was performed within the first month. Postoperative BCVA at final follow-up improved from logMAR 0.70 to logMAR 0.30 (Snellen equivalent of 20/100 to 20/40). A multivariate logistic regression analysis demonstrated no statistically significant predictors of recurrent RD.
Conclusion:
Infection and pain are the leading indications for SBR, with infections requiring earlier removal. Recurrent RD occurred in 11% of cases, especially with early removal, with all recurrences occurring within 3 months of SBR. Despite these risks, visual outcomes post-SBR are generally favorable. Close monitoring during the early postoperative period is therefore recommended.