Related Experiment Video
Updated: May 9, 2026

Generation of a Mouse Spontaneous Autoimmune Thyroiditis Model
Published on: March 17, 2023
Early Transient Hypothyroidism Is Associated With Long-Term Outcomes of 131I Treatment in Graves' Disease: A
Pei Yin1, Jiangmeng Wu1, Huayi Zhao1
1Department of Radiology & Nuclear Medicine, The First Hospital of Hebei Medical University, Shijiazhuang, China.

Background:
Radioactive iodine (131I) is a cornerstone therapy for Graves' disease (GD), yet predicting long-term thyroid functional outcomes remains challenging. Early transient hypothyroidism (ETH) is a common phenomenon post-therapy, but its prognostic value for differentiating between permanent hypothyroidism and persistent hyperthyroidism is not fully elucidated.
Methods:
This retrospective cohort study included 222 GD patients treated with 131I. Patients were categorized based on thyroid function within the first 6 months: the ETH group (occurrence of transient hypothyroidism, n = 59) and the Non-ETH group (n = 163). ETH was defined as TSH > 4.2 mIU/L with or without low FT4 on at least one measurement, with temporary levothyroxine support provided if symptomatic. Detailed baseline characteristics, including calculated dose per gram of thyroid tissue (mCi/g), were analyzed. The primary endpoints were permanent hypothyroidism, euthyroidism, or persistent/recurrent hyperthyroidism. Kaplan-Meier survival analysis and multinomial logistic regression models were employed to identify independent predictors of long-term outcomes.
Results:
Baseline analysis revealed that the ETH group had significantly higher pretreatment TRAb levels (median 19.30 vs. 14.35 IU/L, p = 0.021) and a higher prevalence of palpitations (84.7% vs. 64.4%, p = 0.004) compared to the Non-ETH group. Importantly, the ETH group had a significantly higher rate of developing permanent hypothyroidism (52.5% vs. 20.9%, p < 0.001), whereas the Non-ETH group was prone to persistent hyperthyroidism (55.8% vs. 28.8%). In multinomial logistic regression adjusted for dose intensity (mCi/g), Non-ETH status was a strong independent predictor for persistent hyperthyroidism (OR = 3.888, 95% CI: 1.435-10.535, p = 0.008) relative to permanent hypothyroidism. Furthermore, higher dose intensity (mCi/g) was universally associated with permanent hypothyroidism, while older age favored euthyroidism outcomes (OR = 1.055, p = 0.002).
Conclusion:
Early transient hypothyroidism following 131I therapy serves as a clinical indicator associated with effective glandular destruction and a high trajectory toward permanent hypothyroidism. Conversely, the absence of ETH signals a high risk of treatment failure. These findings suggest that patients with ETH require careful long-term monitoring for hypothyroidism rather than aggressive anti-thyroid drug re-initiation, and the dose per gram of tissue is a definitive determinant of functional ablation.
Related Concept Videos
 01:28
Graves' Disease I: Introduction
 01:24
Graves Disease II: Pathophysiology
 01:25
Hyperthyroidism I: Introduction
 01:27
Hyperthyroidism II: Pathophysiology
 01:23
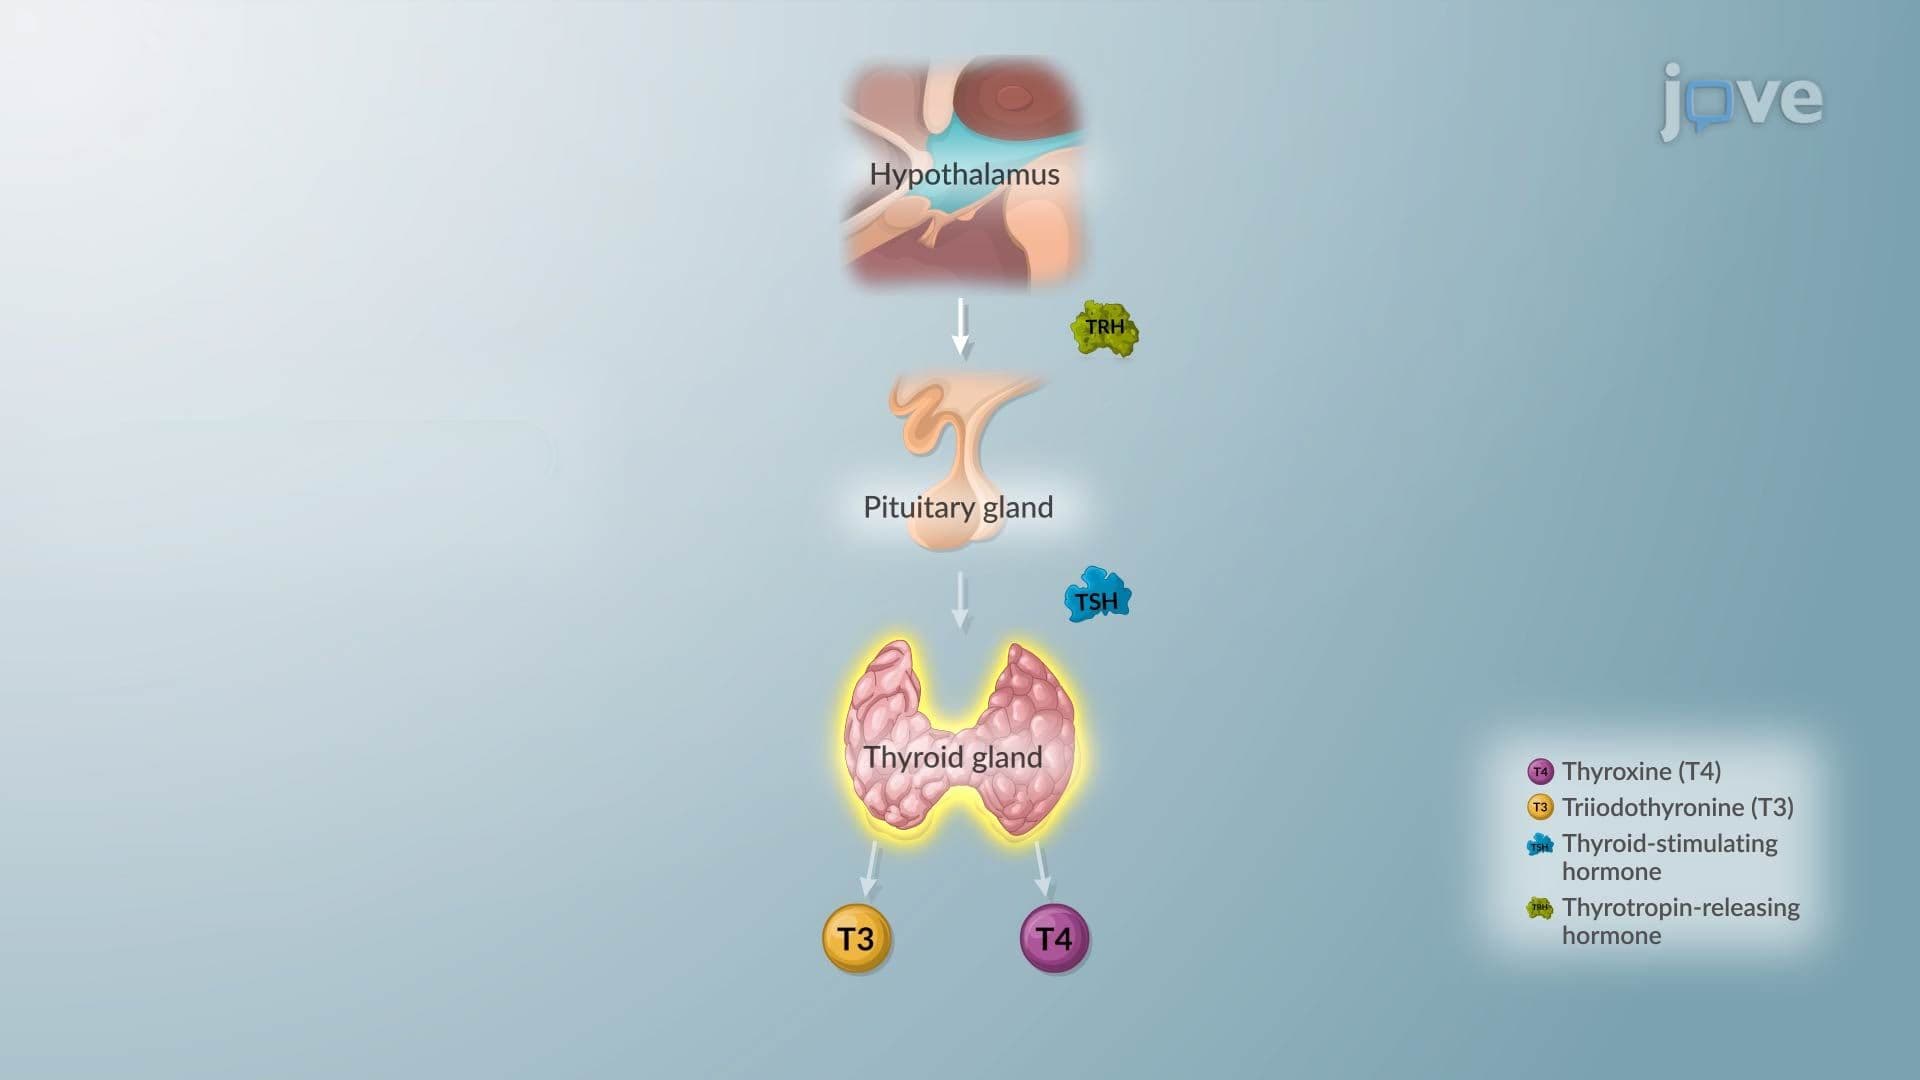
Hypothyroidism II: Pathophysiology
 01:27
Goiter