Related Experiment Videos
Nudging implementation of low tidal volume ventilation: a stepped wedge, cluster randomized trial
Meeta Prasad Kerlin1,2,3, Michael O Harhay4,5,6, Fan Li7
1Pulmonary, Critical Care and Allergy Division, Department of Medicine, Perelman School of Medicine at the University of Pennsylvania, 3400 Civic Center Blvd, Perelman Center for Advanced Medicine, 627 South Pavilion, Philadelphia, PA, 19104, USA. prasadm@pennmedicine.upenn.edu.

Background:
"Nudges" embedded in the electronic health record (EHR) facilitate desired decisions while preserving autonomy and may provide a scalable strategy to overcome the common implementation barrier of lack of knowledge about a best practice. We sought to test whether EHR-based nudges targeting two intensive care unit (ICU) clinician groups would safely increase evidence-based use of low tidal volume ventilation.
Methods:
We performed a stepped-wedge, cluster randomized, hybrid type 3 effectiveness-implementation trial in 12 ICUs from February 2021 to May 2023 to test three nudges targeting clinicians responsible for order entry and respiratory therapists responsible for operationalizing orders and documentation. A default ventilation order auto-populated a low tidal volume setting; an accountable justification order required a free-text justification to order high tidal volume; and an accountable justification flowsheet required a free-text justification to document delivery of high tidal volume. ICUs were randomly assigned to launch one of the two order nudges on a pre-specified date, followed by the flowsheet nudge six months thereafter. The primary outcome was fidelity to low tidal volume ventilation, defined as percentage of time during the first 72 h of ventilation with low tidal volumes. For additional contextual inquiry, we conducted qualitative interviews with ICU clinicians regarding their perspectives on low tidal volume ventilation and study nudges.
Results:
The primary analysis included 4412 patients. Unadjusted median fidelity to low tidal volume ventilation was 45.7%. Using multivariable mixed effects regression, marginal estimates of fidelity to low tidal volume ventilation ranged from 47.1% to 57.8% across study groups, with no significant differences after Holm adjustment for multiple comparisons. ICUs experienced variable changes with nudges in fidelity to low tidal volume ventilation. Clinician interviews revealed potential explanations for this variability, including the possibility of differential effects by experience level of clinicians and culture of interprofessional collaboration, and influence of the COVID-19 pandemic on familiarity with and use of low tidal volume ventilation.
Conclusions:
EHR-based default and accountable justification nudges did not increase utilization of low tidal volume ventilation in a broad population of mechanically ventilated patients; however, nudge effectiveness varied by ICU.
Trial Registration:
Clinicaltrials.gov, NCT04663802. Registered 10 December 2020, https://clinicaltrials.gov/study/NCT04663802.
Related Concept Videos
 01:23
Mechanical Ventilation II: Invasive Ventilation
Negative-Pressure Ventilators
Negative-pressure ventilators create a vacuum around the chest or body to draw air into the lungs, simulating breathing. This method does not require an...
 01:29
Assessment of Ventilation II: Respiratory Depth and Rhythm
Respiratory depth measures the volume of air inhaled or exhaled during a breath. It can vary from shallow to deep and typically remains consistent when a person is at rest or asleep. Occasionally, individuals will automatically inhale deeply, known as sighing, which inflates the lungs with more air than normal breathing.
To assess respiratory depth, observe the degree of chest excursion or movement:
 01:29
Mechanical Ventilation I: Indication and Settings
 01:15
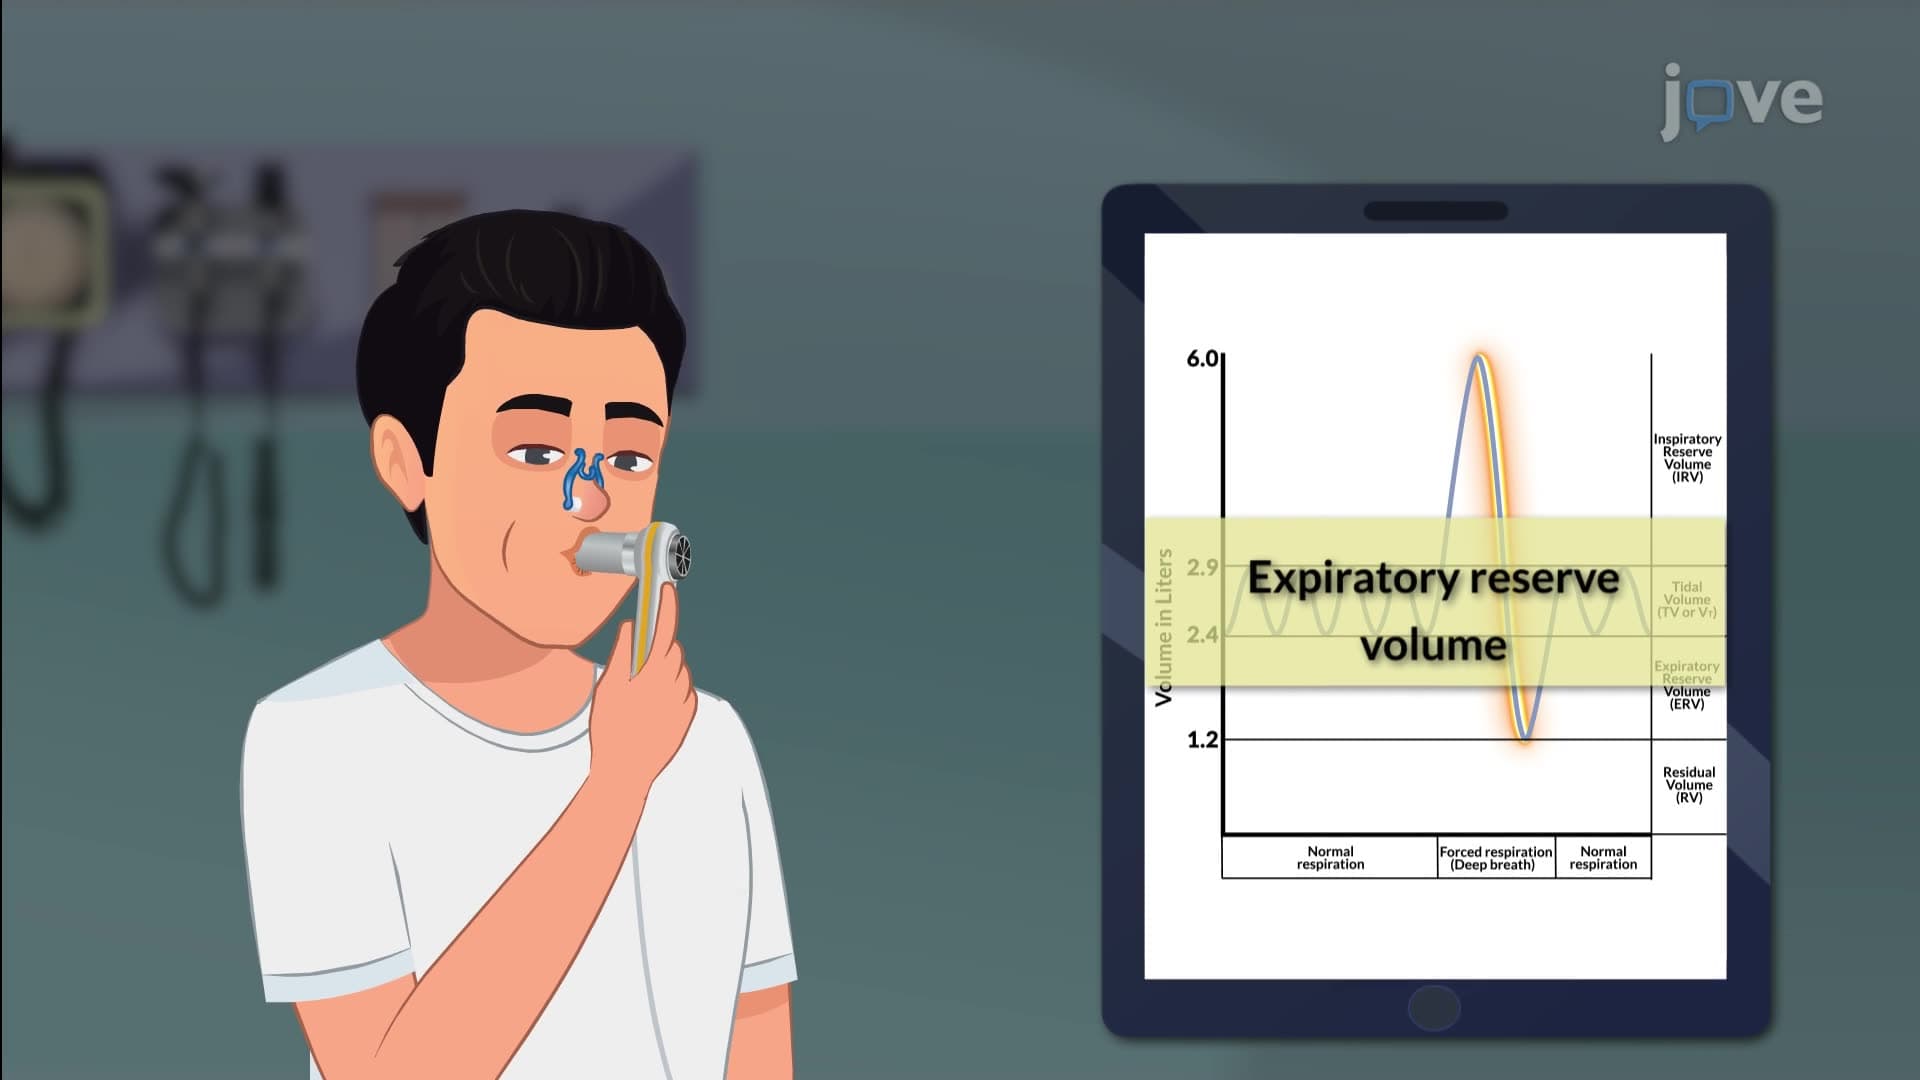
Respiratory Volumes
Tidal Volume (TV) Tidal volume (TV) is the air inhaled or exhaled in a...
 01:23
Mechanical Ventilation III: Noninvasive Ventilation
Noninvasive Positive-Pressure Ventilation (NIPPV)
 01:26
Respiratory Volumes and Capacities I