Related Experiment Video
Updated: May 9, 2026


A Hyperandrogenic Mouse Model to Study Polycystic Ovary Syndrome
Published on: October 2, 2018
Dual case insights shaping a new protocol for post-menopausal hirsutism
Einas Mohamed1, Jemima Sellicks2, Amy Kitchener3
1Division of Diabetes, Endocrinology and Metabolism, Section of Endocrinology and Investigative Medicine, Imperial College London, London W12 0NN, UK.

Abstract:
Hyperandrogenism in women typically presents with hirsutism and other virilizing features. When it presents with accelerated clinical features and/or high androgen levels (total testosterone > 5 nmol/L) (>145 ng/dL) (reference range, <2.4 nmol/L [SI: <70 ng/dL]), particularly in the post-menopausal state, an underlying ovarian or adrenal neoplasm should be considered. With ovarian pathology, androgen-secreting ovarian tumors and ovarian hyperthecosis are the key differential diagnoses. The recommended treatment for androgen-secreting ovarian tumors (ASOTs) is surgical removal. In contrast, ovarian hyperthecosis may be managed conservatively, provided an androgen-secreting malignant tumor has been excluded. Clarifying this diagnostic uncertainty is a challenge, and imaging and biochemical tests are not always diagnostic. There is additionally a need for better medical treatment in patients with benign ASOTs. We report two cases of female hyperandrogenism with a radiologically identified ovarian lesion, managed with a gonadotropin-releasing hormone (GnRH) antagonist, namely, degarelix. Degarelix was helpful for both diagnosis and treatment of symptoms. We highlight its potential role in diagnosis and medical management, particularly as an option for patients who are unwilling or unable to undergo immediate surgery. We also hypothesize that a fall in total testosterone following GnRH antagonist injection may indicate that an ovarian tumor is benign.
Related Concept Videos
 01:30
Hormonal Control of the Ovarian Cycle
Before puberty, the hypothalamus releases GnRH in a low frequency, low amplitude pulsatile manner. This along with the immature hypothalamic-pituitary-gonadal axis activity, results in low estrogen levels and the absence of a fully functional ovarian cycle. At puberty, GnRH secretion increases in both frequency and...
 01:22
Hormonal Regulation of the Menstrual Cycle
At puberty, GnRH begins a pulsatile release pattern, which triggers the anterior pituitary gland to secrete follicle-stimulating hormone (FSH) and luteinizing hormone (LH). The frequency and amplitude of GnRH pulses vary across the menstrual cycle, with faster pulses favoring LH release and slower pulses favoring FSH release.
 01:33
Hormonal Regulation
 01:40
Hormonal Regulation
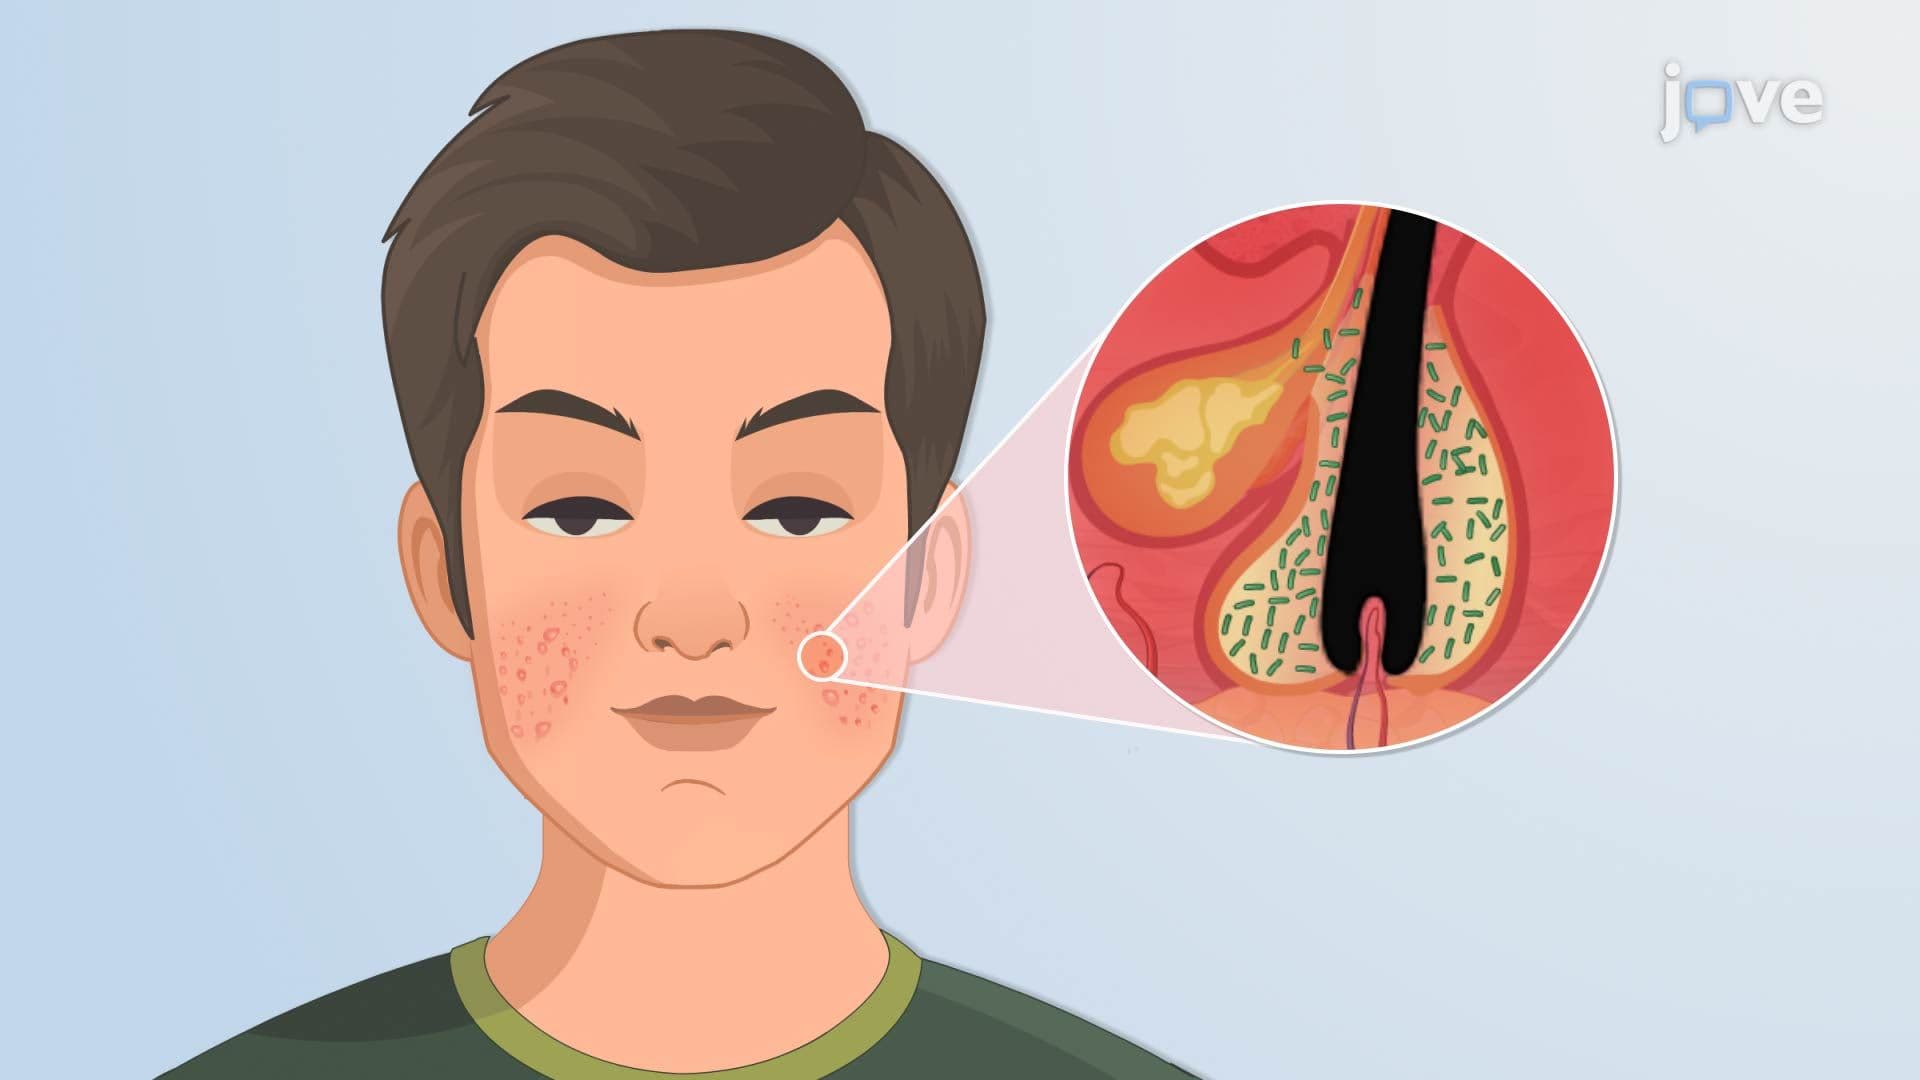 01:27
Acne Infection