Related Experiment Video
Updated: May 9, 2026


Point-of-Care Ultrasound for Peripheral Veno-Arterial Extracorporeal Membrane Oxygenation Without Left Ventricular Venting
Published on: January 17, 2025
Short- and Long-term Efficacy and Safety of Levosimendan in Veno-arterial Extracorporeal Membrane Oxygenation
Pierre-Grégoire Guinot1, Vivien Berthoud2, Agnes Soudry Faure3
1Department of Anaesthesiology and Intensive Care, Dijon University Hospital, Dijon, France; University of Burgundy, Dijon, France.; and Center for Translational and Molecular Medicine, INSERM UMR1231, Lipness Team, Dijon, France.

Background:
Liberation from veno-arterial extracorporeal membrane oxygenation (VA-ECMO) remains challenging. To date, there is limited evidence from observational studies supporting pharmacologic interventions to facilitate successful VA-ECMO weaning. The current study aimed to evaluate the efficacy and safety of a single dose of levosimendan in patients supported by VA-ECMO who met predefined criteria for weaning.
Methods:
The WEANILEVO study was a multicenter, double-blind, randomized, parallel-group, placebo-controlled trial. Eighty patients from five French centers who met VA-ECMO weaning criteria were randomly assigned 1:1 to receive either levosimendan (0.2 μg · kg -1 · min -1 ) or placebo for 24 h. The primary endpoint was VA-ECMO weaning failure, defined as absence of weaning within 48 h, recourse to another circulatory assistance device, or death within 7 days of weaning.
Results:
Due to halted funding, the planned number of patients could not be recruited. The final modified intention-to-treat analysis included 80 patients (40 in the levosimendan group and 40 in the control group). VA-ECMO weaning failure occurred in 25% of patients in both the levosimendan and placebo groups (odds ratio, 1.00 [95% CI, 0.36 to 2.75]; P = 1.00). Acute kidney injury at day 30 was significantly more frequent in the levosimendan group (62.5% vs . 38.5%; odds ratio, 2.67 [95% CI, 1.08 to 6.62]; P = 0.03). Patients receiving levosimendan required more vasopressor support (47.5% vs . 28.2%; P = 0.07) and had longer intensive care unit stays (12 [7 to 24] vs . 6 [4 to 13] days; P = 0.02). Mortality rates at 30 days (18.0% vs . 33.3%; P = 0.07) and 1 yr (31.6% vs . 51.4%; P = 0.08) did not significantly differ between groups.
Conclusions:
Levosimendan administration did not reduce VA-ECMO weaning failure in patients who already met weaning criteria; however, a clinically important benefit or harm cannot be ruled out. The observed higher incidence of acute kidney injury and longer intensive care unit stays in the levosimendan group are hypothesis generating and require confirmation in larger, adequately powered trials.
Related Concept Videos
 01:13
Bioequivalence studies: Biowaivers
 01:11
Clinical Trials: Overview
 01:26
Heart Failure Drugs: Inotropic Agents
 01:24
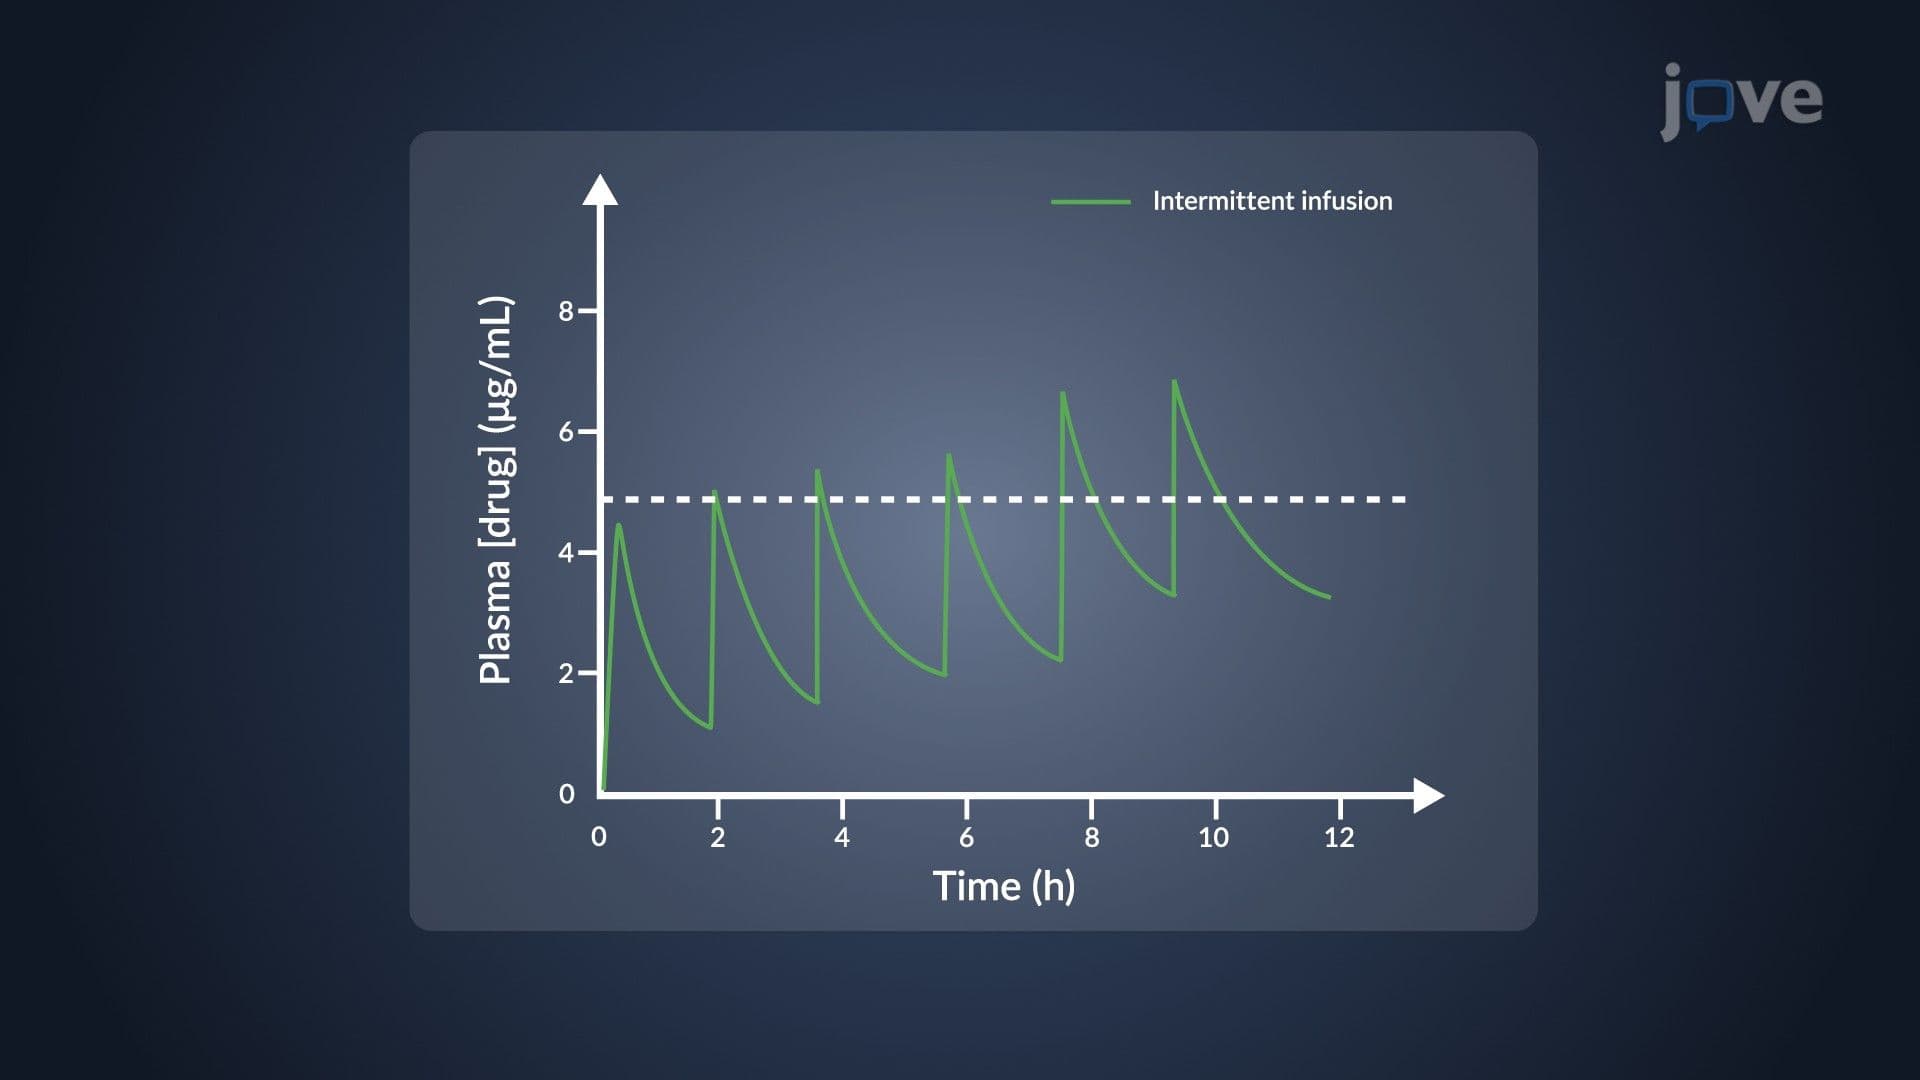
Drug Accumulation During Multiple Dosing: Intermittent IV Infusions
 01:11
Bioavailability Study Design: Single Versus Multiple Dose Studies
 01:16
Clinical Trials
There are four phases in a clinical trial. A phase one...