Comparison of Different Neostigmine Doses for Reversal of Cisatracurium-Induced Neuromuscular Block in Children Under
Antonio J M M Neto1,2, Guilherme L Benette1, Letícia C Siqueira1
1Department of Surgery, Pontifical Catholic University of São Paulo (PUC-SP), School of Medical and Health Sciences, São Paulo, Brazil.

Background:
Neostigmine is widely used to reverse nondepolarizing neuromuscular blockade in children, but the optimal dose under total intravenous anesthesia is uncertain.
Aims:
The primary aim was to compare the time to full neuromuscular recovery (TOF ratio of 1.0) following administration of neostigmine at doses of 0, 10, 20, and 30 μg/kg in children at a TOF count of 3. Secondary objectives were full reversal within 10 min and adverse events.
Methods:
This prospective, randomized, double-blind, parallel-group, superiority trial enrolled 120 children (2-10 years; ASA I-II) undergoing tonsillectomy. Participants received 0, 10, 20, or 30 μg/kg neostigmine at a TOF count of 3 measured by quantitative acceleromyography. The primary outcome was the time from TOF count of 3 to full reversal (TOF ratio = 1.0). Secondary outcomes were the proportion of patients achieving full reversal within 10 min and adverse events. Comparisons among active groups used the Kruskal-Wallis test.
Results:
A total of 118 patients were analyzed. Median [IQR] time to full reversal was 20.2 [14.8-24.1], 14.0 [10.7-16.8], 11.0 [8.2-15.5], and 11.2 [7.9-14.6] min in the 0, 10, 20, and 30 μg/kg groups, respectively. Reversal was significantly slower in the control group compared with all neostigmine doses. However, there was no statistically significant difference among the active doses (Kruskal-Wallis, p = 0.33). At 10 min, full reversal had occurred in 10.7%, 23.3%, 43.3%, and 33.3% of patients in the respective groups. Adverse events were uncommon, occurring in 10 of 118 patients, and consisted exclusively of transient bradycardia and tachycardia, without differences among groups.
Conclusions:
At TOF count of 3, neostigmine 10-30 μg/kg shortened reversal compared with no reversal, but doses above 10 μg/kg conferred no additional benefit. Quantitative monitoring remains essential, as fewer than half of patients achieved a TOF ratio of 1.0 within 10 min.
Trial Registry:
https://ensaiosclinicos.gov.br/rg/RBR-4xrx2g3.
Related Concept Videos
 01:19
Depolarizing Blockers: Pharmocokinetics
 01:11
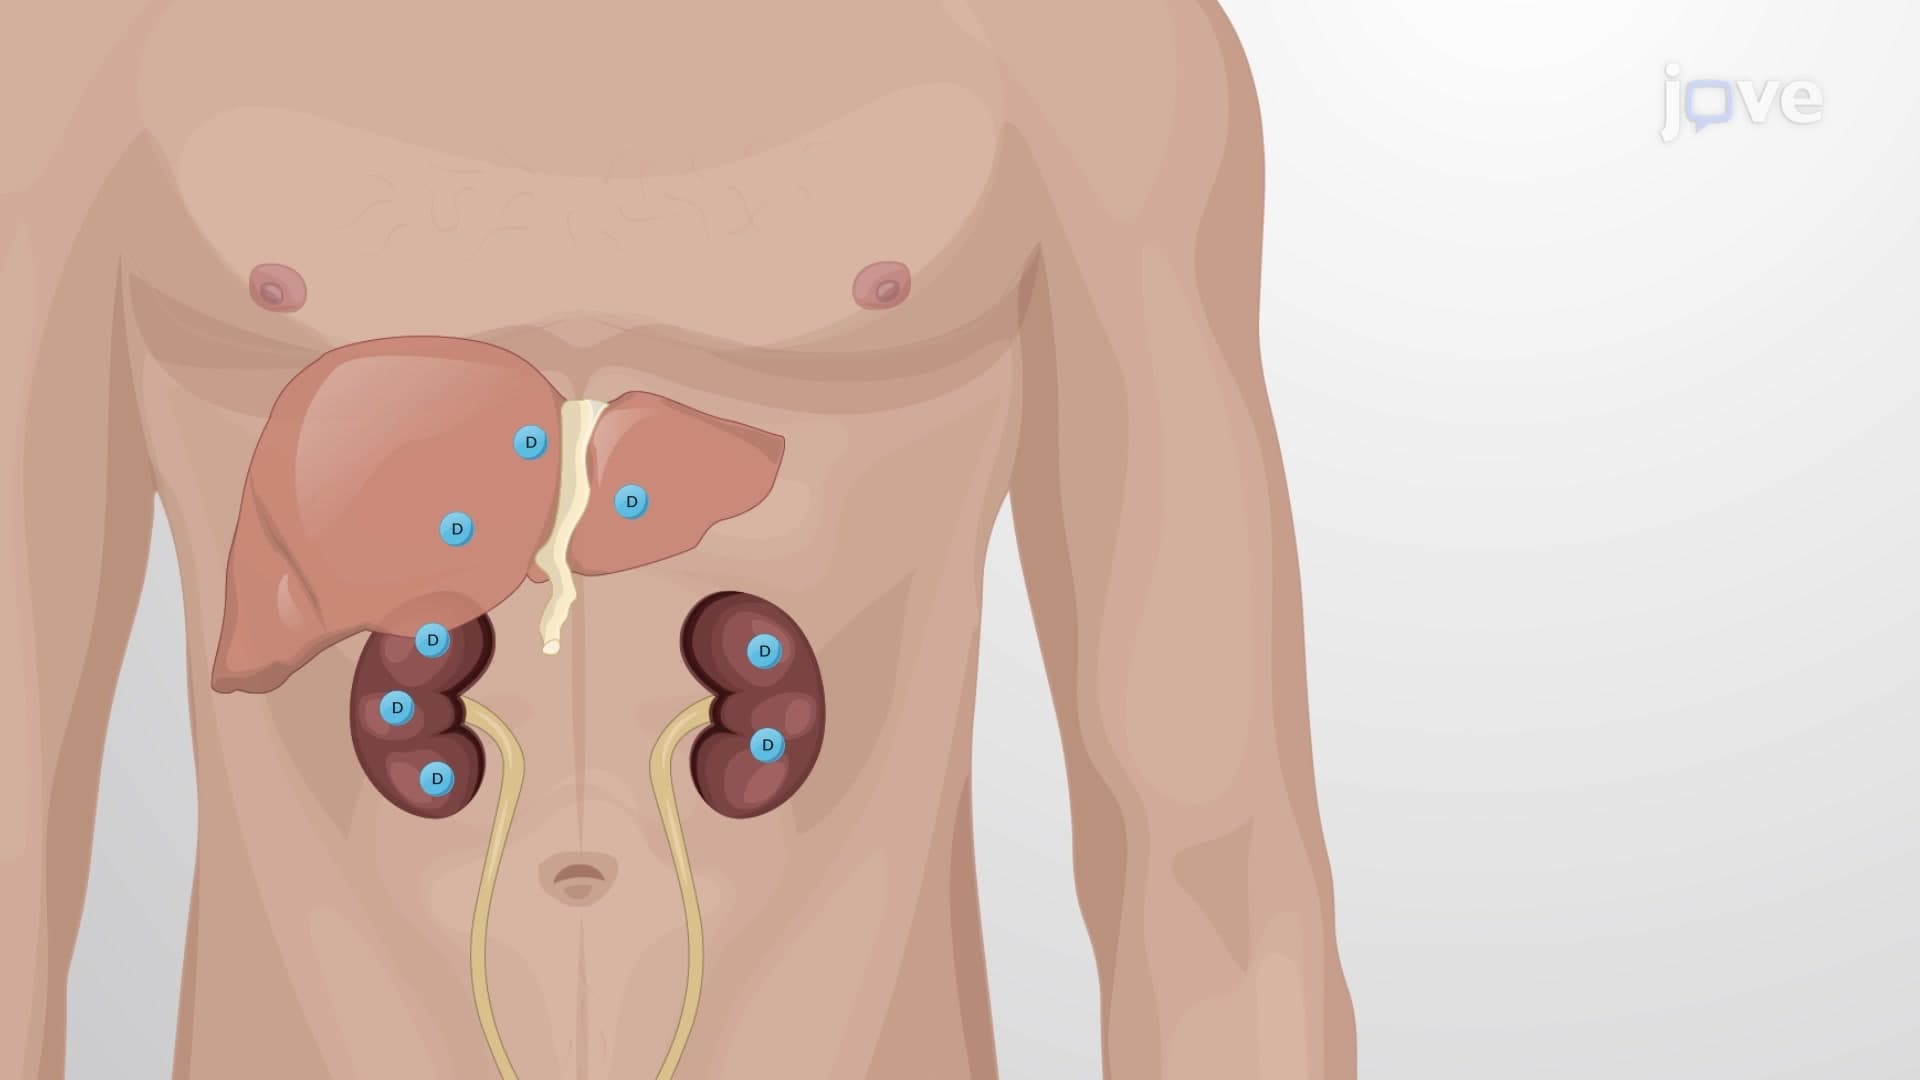
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacokinetics
Instead, they are transported by the blood to different tissues. Muscles with a greater blood supply (arteries) and blood flow receive more...
 01:27
Nondepolarizing (Competitive) Neuromuscular Blockers: Pharmacological Actions
Although all competitive neuromuscular blockers are designed...
 01:17
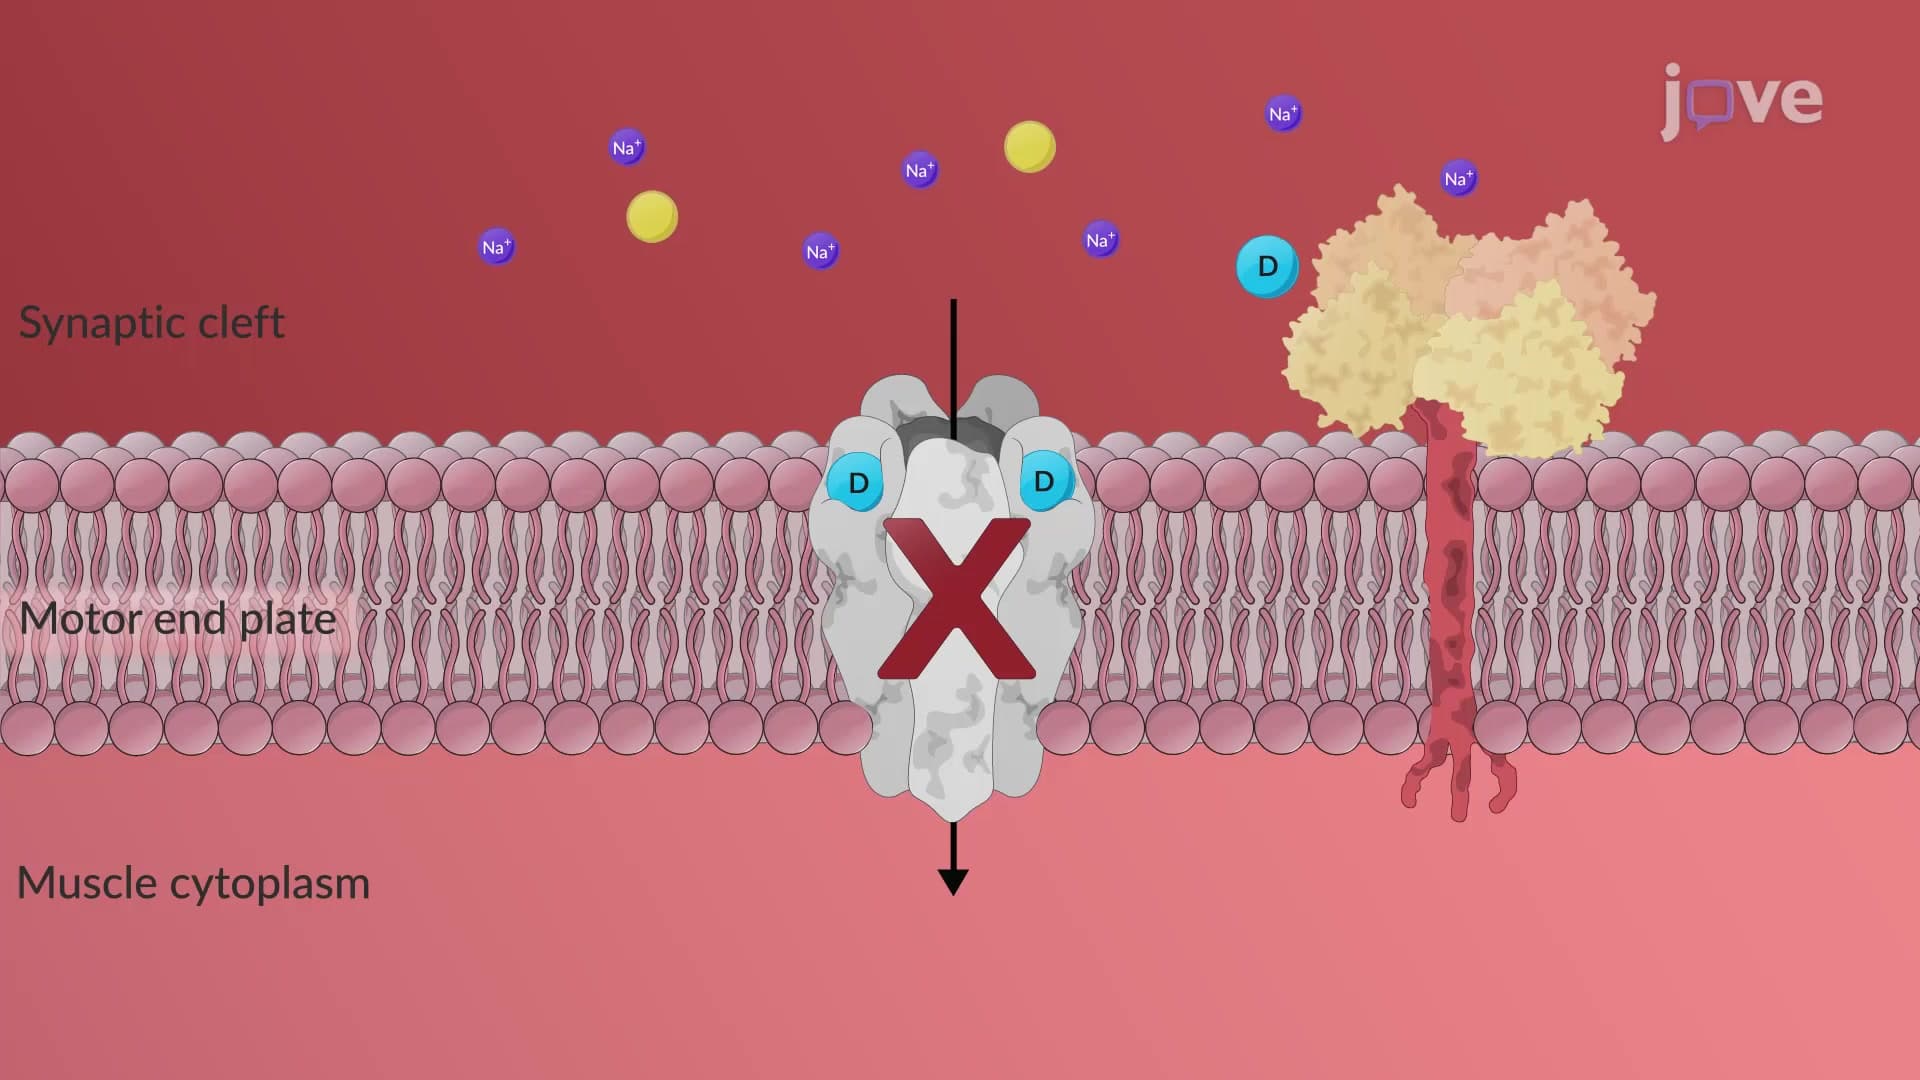
Nondepolarizing (Competitive) Neuromuscular Blockers: Mechanism of Action
Competitive antagonists prevent acetylcholine from binding to its receptor, inhibiting membrane depolarization. Without conformational changes or intrinsic...
 01:21
Skeletal Muscle Relaxants: Adverse Effects
Unlike...
 01:28
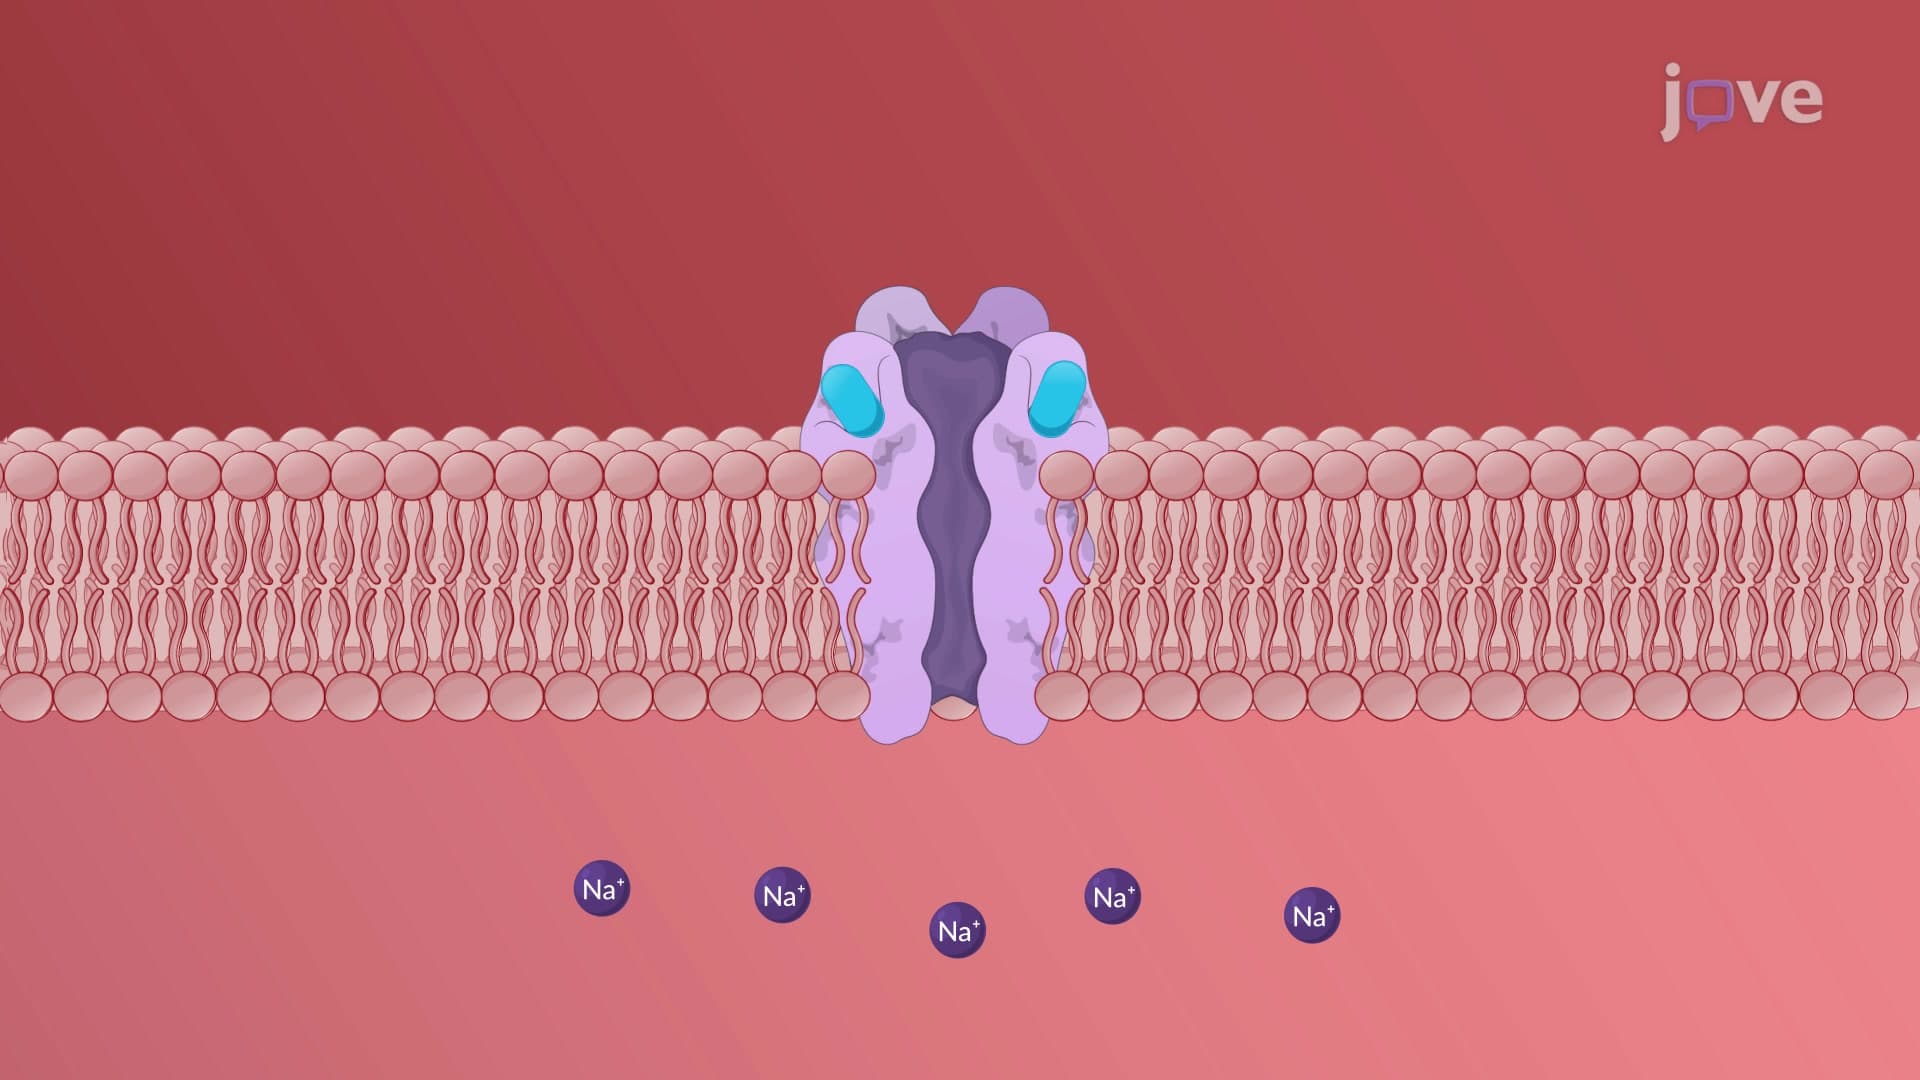
Depolarizing Blockers: Mechanism of Action
Succinylcholine is the most commonly used depolarizing blocker. Chemically, it constitutes two molecules of acetylcholine joined together by an acetate methyl group. They act on the receptors in the same way as acetylcholine. Because succinylcholine...