Related Experiment Video
Updated: May 9, 2026

Measurement of Heart Contractility in Isolated Adult Human Primary Cardiomyocytes
Published on: August 9, 2022
Towards a Quantitative Understanding of Aficamten Clinical Pharmacology: Pharmacokinetic-Cardiodynamic Modeling to
Justin D Lutz1, Russ Wada2, Daniel L Jacoby3
1Clinical Pharmacology, Cytokinetics, South San Francisco, California, USA.

Abstract:
In the phase 3 study SEQUOIA-HCM (NCT05186818), aficamten, a next-in-class cardiac myosin inhibitor, was safe and efficacious in participants with obstructive hypertrophic cardiomyopathy (oHCM). Using pharmacokinetics/pharmacodynamics (PKPD) modeling, we quantified the relationship between aficamten exposure and cardiodynamic measures of safety (left ventricular ejection fraction [LVEF]) and efficacy (post-Valsalva left ventricular outflow tract gradient [LVOT-G]), and used Clinical Trial Simulations (CTS) to predict cardiodynamics for a flexible dose regimen in a post-approval setting. PKPD relationships between aficamten average concentration over 24 h (Cavg,24) and LVEF or LVOT-G were well quantified. Within-subject variability for LVEF was low (CV = 7.6%), indicating that prior LVEF readings are highly predictive of future readings during stable therapy. A ~2% decrease in LVEF is expected per 100 ng/mL increase in Cavg,24. LVOT-G slope was ~10-fold steeper vs. LVEF, suggesting a relatively large therapeutic window. The commercial regimen allows for individualized flexible echocardiography-based dose titration (every 2-8 weeks) from 5 to 20 mg once daily and flexible maintenance dose monitoring. CTS demonstrated minimal differences in population progression of LVOT-G < 30 mmHg and LVEF < 50% between evaluated dose-titration frequencies (every 2, 4, 6, or 8 weeks) over the first 6 months of treatment, supporting a 2-8 week window for dose titration. With maintenance doses, the probability of maintaining LVOT-G < 30 mmHg (~60%) was high and the probability of occurrences of LVEF < 50% (~3%) was low. Therefore, this regimen should maintain safe and efficacious cardiodynamics while increasing convenience and access for patients with oHCM.
Related Concept Videos
 01:15
Impact of Pharmacokinetic–Pharmacodynamic Models: Regulatory Decisions
 01:15
Pharmacodynamic Models: Linear Concentration–Effect Model
 01:27
Pharmacodynamic Models: Overview
 01:14
Pharmacokinetic–Pharmacodynamic Relationship: Model Components
 01:29
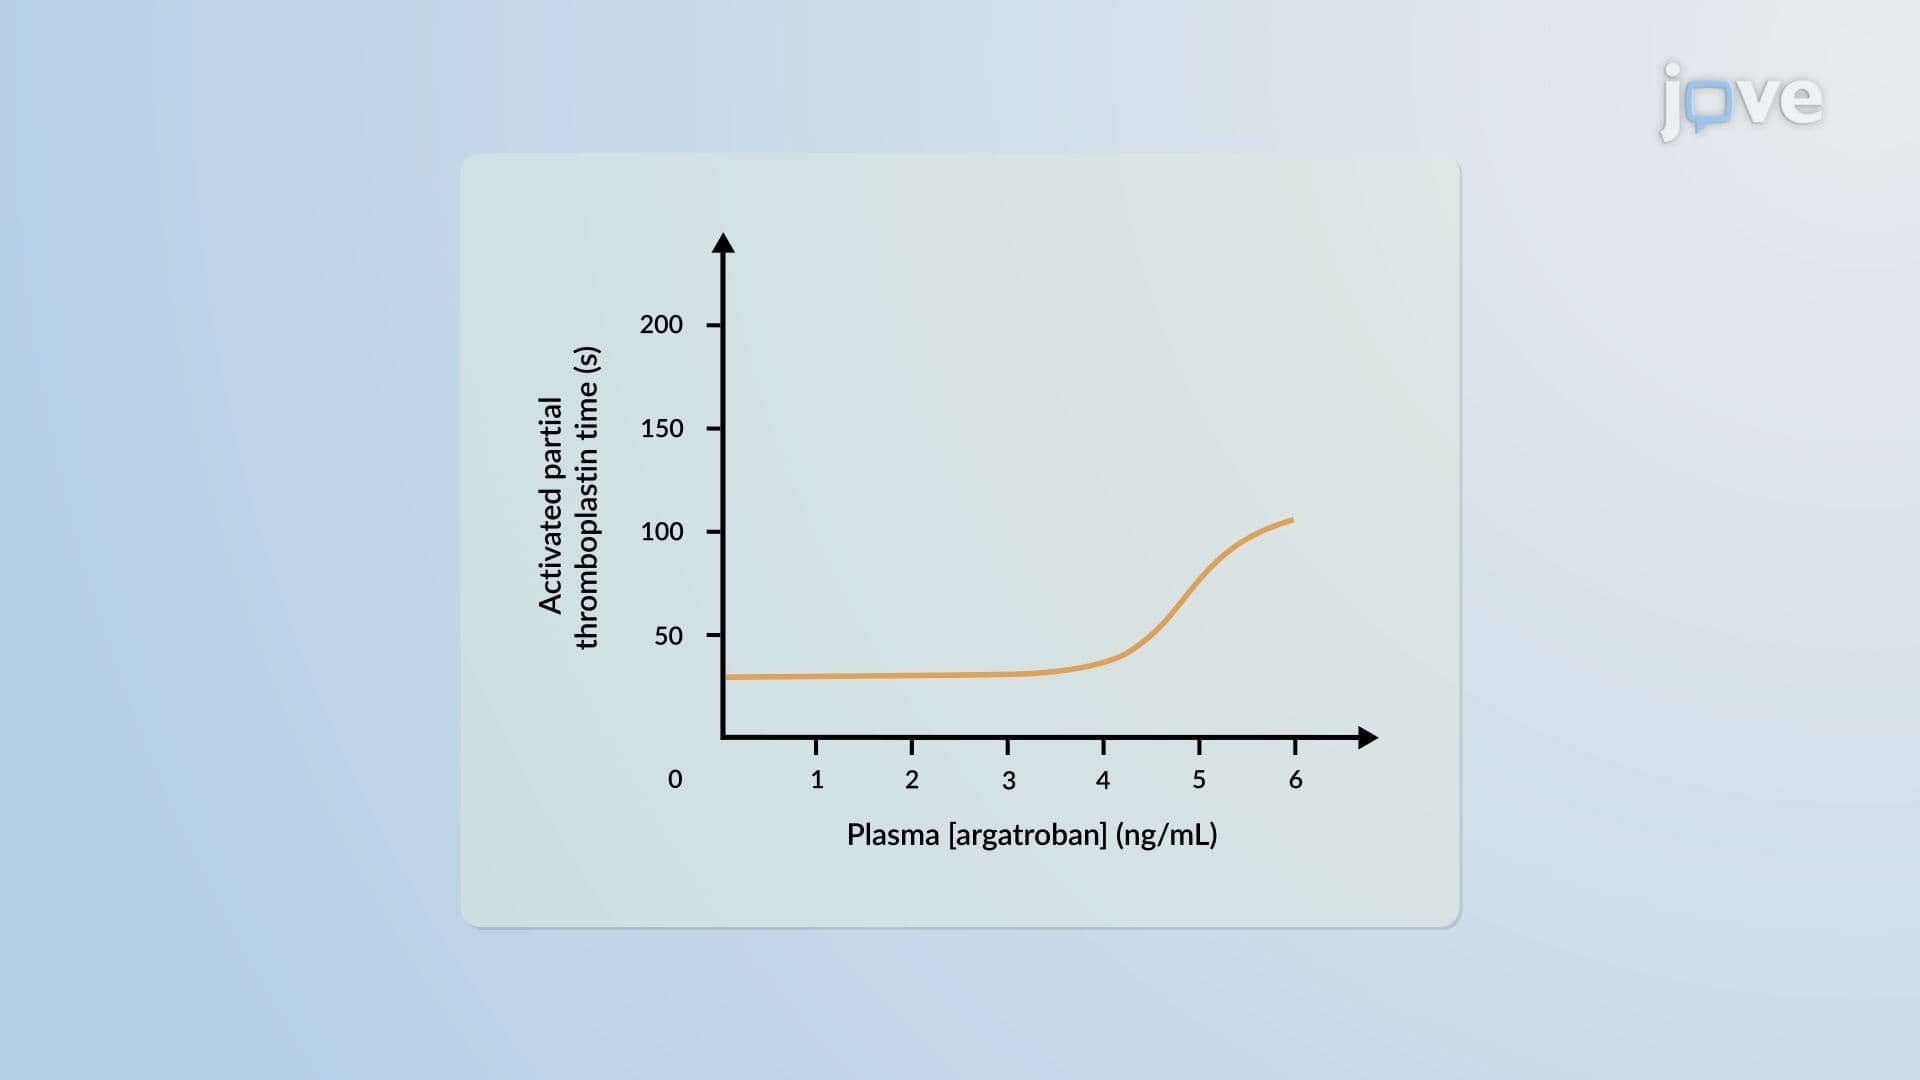
Pharmacodynamic Models: Direct Effect Model and Indirect Response Model
 01:20
Pharmacokinetic Models: Overview
There are three primary types of models: empirical, compartment, and physiological. Empirical models, with minimal assumptions,...