Related Experiment Video
Updated: May 9, 2026
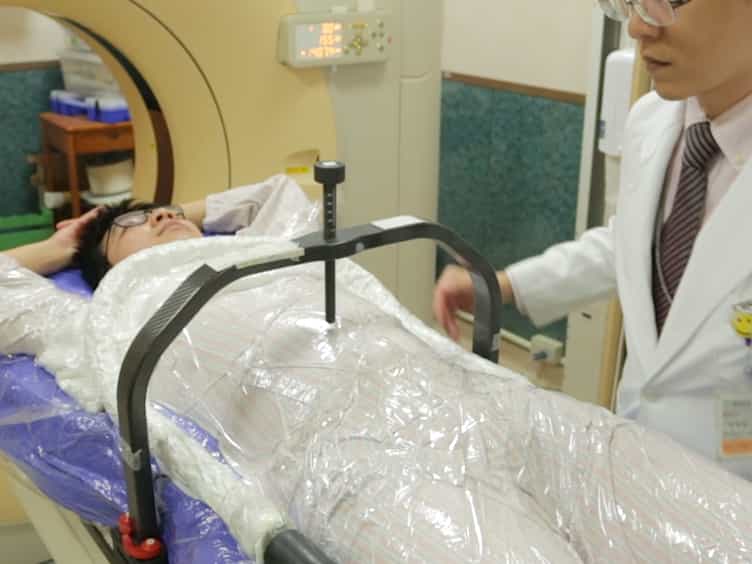
Treatment of Liver Metastases Using an Internal Target Volume Method for Stereotactic Body Radiotherapy
Published on: May 8, 2018
Cost-effectiveness analysis of upfront HA-WBRT vs. SRS for treatment of brain metastases due to SCLC
Keshav Goel1, Yushen Qian2, Erqi Pollom2
1Perelman School of Medicine, University of Pennsylvania, Philadelphia, USA. goelkp@pennmedicine.upenn.edu.

Introduction:
Hippocampal-avoidant whole brain radiation therapy (HA-WBRT) and stereotactic radio surgery (SRS) are standard of care treatments for brain metastases (BM). However, the optimal approach for treating BM originating from small cell lung cancer (SCLC) remains uncertain. We conducted a cost-effectiveness analysis comparing HA-WBRT and SRS for SCLC BMs.
Methods:
We constructed a Markov model to evaluate the incremental cost-effectiveness ratio (ICER) of SRS versus HA-WBRT. In this model, patients either receive upfront SRS or HA-WBRT. Those receiving SRS may undergo salvage HA-WBRT if they experience salvageable distant recurrences, or progress to non-salvageable local and distant recurrences. We performed over 100,000 Monte Carlo simulations, varying cost and utility parameters using Beta distributions, to analyze the impact of these variations on the ICER.
Results:
The base case ICER for SRS was $2126.88. SRS was more costly and more/less effective in 56.1%/43.9% of Monte Carlo simulations. MRI cost had the greatest positive impact on ICER, and cost of hospice had greatest negative impact. The utility decline of the four-month of neurocognitive decline post-HA-WBRT had the strongest negative impact. The transition probabilities of the controlled state, death, distant recurrence (salvageable), and local recurrence (non-salvageable) had statistically significant impacts on ICER (p < 0.001).
Discussion:
SRS was more expensive than HA-WBRT in all simulations and more effective in most. The cost of the MRI and hospice care and the transition probabilities of the controlled state and death had the greatest influence on ICER. As survival increased, ICER decreased, emphasizing the importance of patient selection for SRS.
