Related Experiment Video
Updated: May 10, 2026
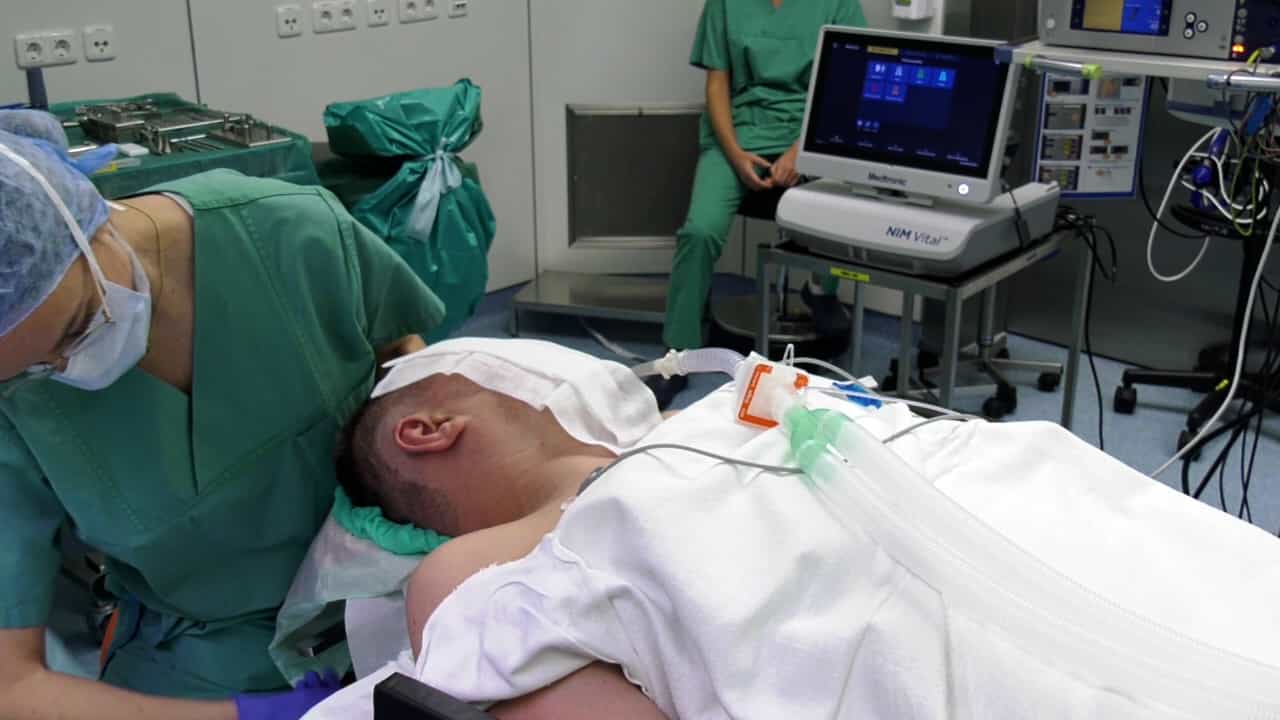

Performing Repeated Intraoperative Impedance Telemetry Measurements during Cochlear Implantation
Published on: August 4, 2023
MI-SI-R: A Mini-Invasive, Drill-Free, Anchor-Free Subperiosteal Reverse Technique for Active Bone Conduction
Pierre-François Dolhen1, Jean-Marc Gerard2, Morgan Potier3
1Clinique Causse-MSP Narbonne, Narbonne, France.

Objective:
To evaluate the feasibility, safety, and preliminary audiological outcomes of the mini-invasive subperiosteal reverse (MI-SI-R) technique, a screw-free and drill-free approach for the implantation of active piezoelectric bone conduction devices.
Setting:
Tertiary referral otology center.
Study Population And Methods:
Fourteen patients underwent 15 procedures using the MI-SI-R technique, with follow-up periods ranging from 12 to 26 months (mean: 19.6 mo; median: 22 mo). The cohort included 3 patients with single-sided deafness (SSD) and 12 with mixed hearing loss (MHL). Detailed audiological outcomes were available for a homogeneous subgroup of 9 MHL cases. A preoperative Softband bone conduction trial was performed in the same patients for intrasubject comparison, and outcomes were contrasted with published data.
Design:
Retrospective, single-center feasibility study.
Intervention:
Implantation of an active piezoelectric bone conduction device without bone anchoring or bone-bed drilling, using a 3 cm vertical retroauricular skin-periosteal incision and an endoscopically created subperiosteal pocket. The implant was positioned in reverse orientation (magnet/microphone anterior, actuator posterior).
Main Outcome Measures:
Pure-tone average (PTA), speech recognition threshold (SRT), overclosure, sound localization, SSQ, and APHAB scores; operative time, complications, and feasibility of early fitting.
Results:
At 3 months, mean PTA improved by 55.1±25.3 dB and mean SRT by 20.2±6 dB, with a mean overclosure of 19.2±9 dB HL in MHL patients. One minor surgical complication (magnet extrusion) required device replacement and was successfully managed using the same subperiosteal pocket. No implant migration was observed during follow-up.
Conclusion:
MI-SI-R is a safe and feasible mini-invasive, drill-free, and anchor-free technique for active bone conduction implantation. By preserving the periosteum and avoiding bone drilling, it represents a reusable tissue-sparing approach with encouraging short-term audiological outcomes. By optimizing implant orientation, the reverse positioning allows a more favorable anterior positioning of the external processor and microphone, consistent with expected processor placement. Larger, multicenter studies with comparative control groups will be required to confirm long-term stability and to further evaluate potential applications, including pediatric indications.
