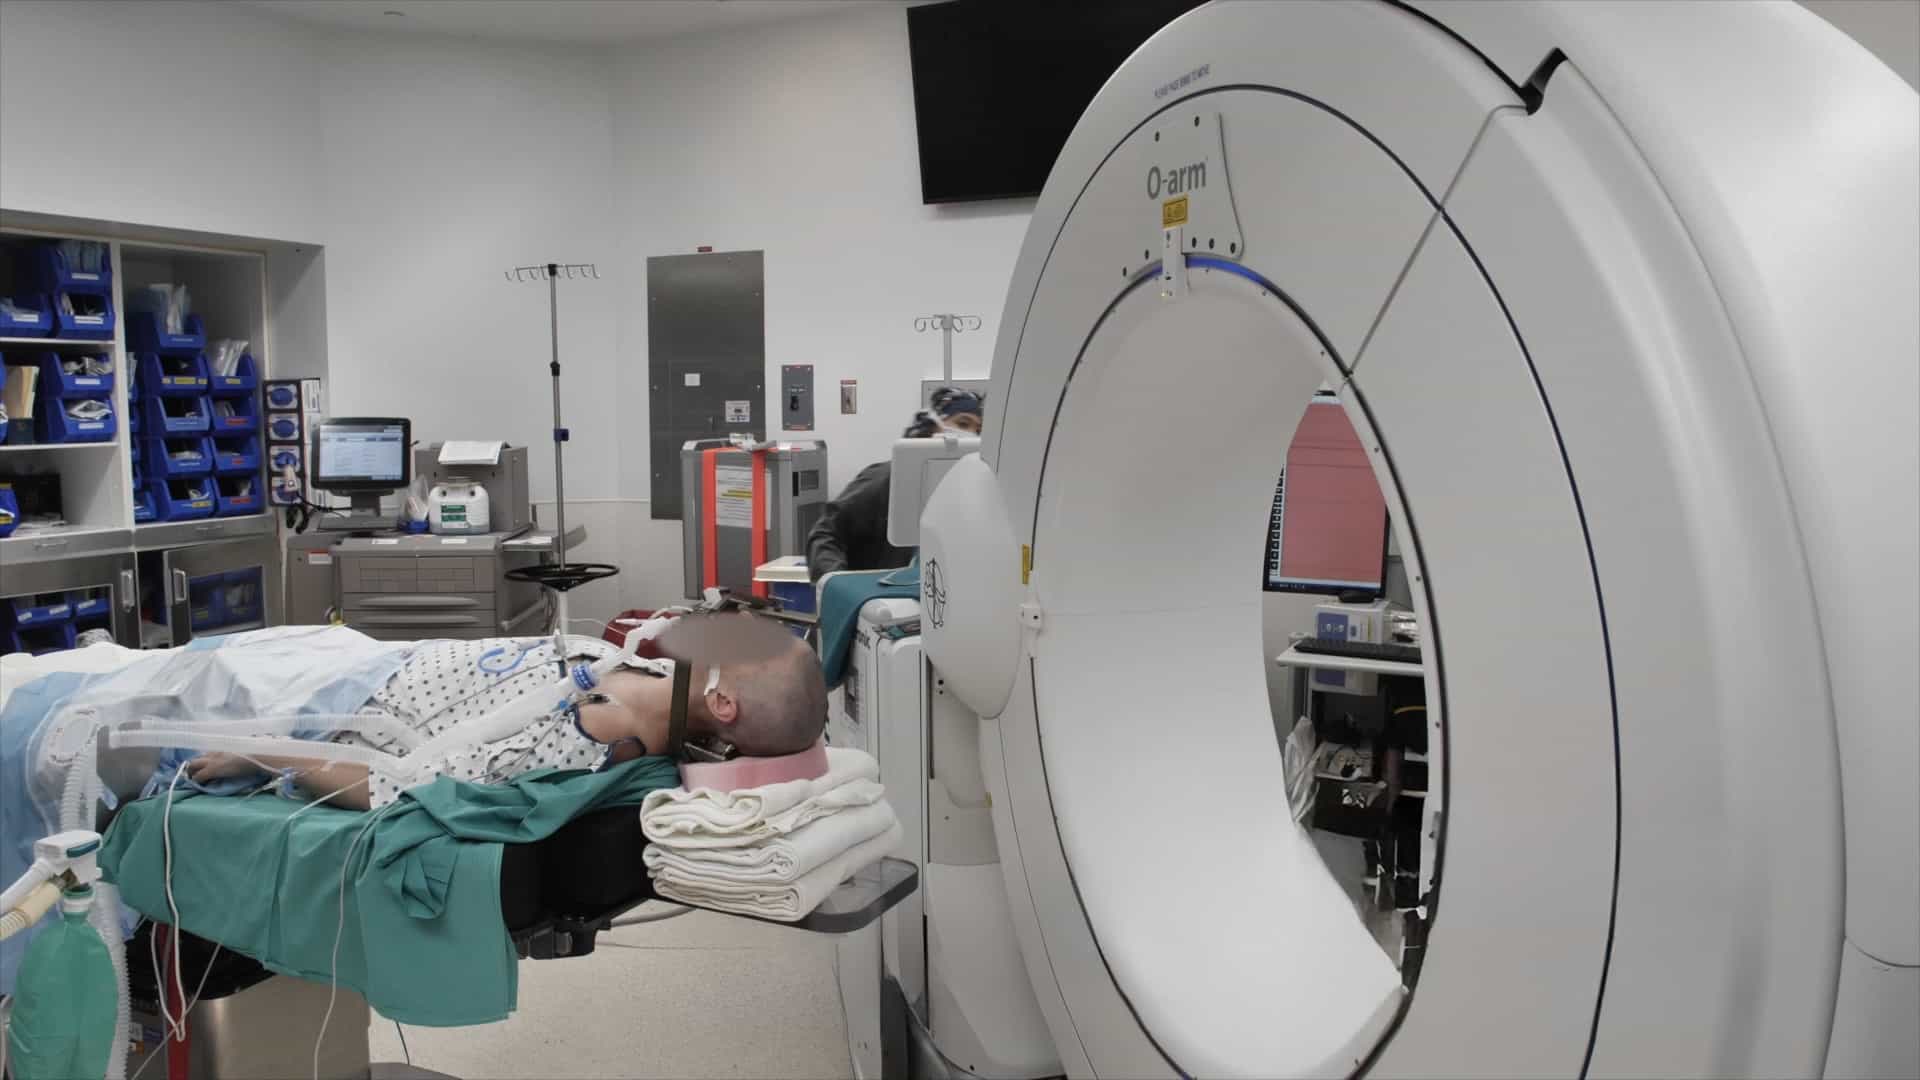
Comparison of postoperative recovery indicators between stereoelectroencephalography and subdural grid electrode implantation for drug-resistant epilepsy
Related Experiment Video
Updated: May 12, 2026
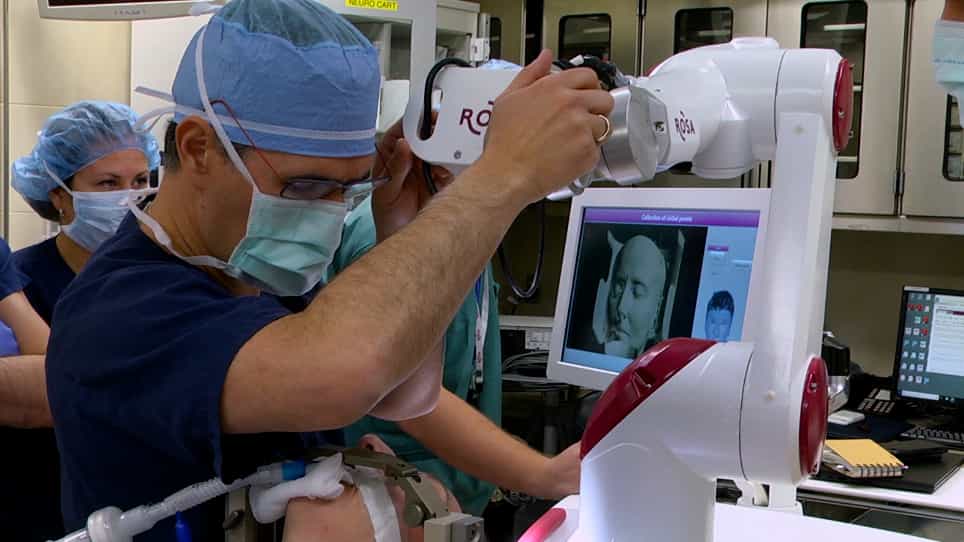
Operative Technique and Nuances for the Stereoelectroencephalographic (SEEG) Methodology Utilizing a Robotic Stereotactic Guidance System
Published on: June 9, 2023
Yuichiro Kojima1, Takehiro Uda1, Toshiyuki Kawashima1
1Department of Neurosurgery, Graduate School of Medicine, Osaka Metropolitan University, 1-4-3 Asahimachi, Abeno-ku, Osaka 545-8585, Japan.

Objective:
In intracranial electrode implantation for drug-resistant epilepsy (DRE), stereoelectroencephalography (SEEG) has increasingly been adopted as a less invasive alternative to subdural grid (SDG) implantation; however, its impact not only on surgical safety outcomes but also on the actual postoperative recovery course remains insufficiently studied. This study compared postoperative recovery indicators between SDG and SEEG.
Methods:
We retrospectively analyzed consecutive patients who underwent SDG or SEEG for DRE. Nine postoperative recovery outcomes were compared by univariable analysis: operation time, blood loss, time to adequate oral intake, number of analgesic administrations, number of antiemetic administrations, time to urinary catheter removal, time to body temperature normalization, time to white blood cell count normalization, and time to C-reactive protein normalization. In addition, exploratory multivariable regression analyses adjusted for age, sex, and year of procedure were performed.
Results:
Participants comprised 47 patients (SDG, n = 23; SEEG, n = 24). In the univariable analysis, the SEEG group showed lower blood loss, earlier resumption of oral intake, fewer antiemetic administrations, shorter time to urinary catheter removal, and shorter time to WBC normalization. In the exploratory multivariable regression analyses, SEEG was significantly associated with reduced blood loss (p = 0.0022), shorter time to adequate oral intake (p = 0.0024), and fewer antiemetic administrations (p = 0.0134), and these associations remained significant after false discovery rate correction.
Conclusions:
Compared with SDG, SEEG was associated with reduced blood loss, earlier resumption of oral intake, and fewer antiemetic administrations. These findings suggest that SEEG may offer early postoperative recovery after intracranial electrode implantation.