Related Experiment Video
Updated: May 12, 2026


Sampling Cerebrospinal Fluid and Blood from Lateral Tail Vein in Rats During EEG Recordings
Published on: September 1, 2023
Development and validation of a clinical nomogram for predicting suboptimal concentration of valproate in pediatric
Tianxin Hu1, Chunyan Du2, Li Lan2
1Department of Pharmacy, Tangdu Hospital, The Fourth Military Medical University, Xi'an, Shaanxi, China.

Insights
A new nomogram predicts suboptimal valproate levels in children with epilepsy. This tool uses dose, acute liver/kidney injury, and meropenem use to guide therapeutic drug monitoring for better seizure control.
Area of Science:
- Pharmacology
- Pediatric Neurology
- Clinical Pharmacy
Background:
- Valproate is a first-line anti-seizure medication with a narrow therapeutic range (50-100 μg/mL).
- Many pediatric epilepsy patients receive suboptimal valproate doses, leading to poor seizure control or toxicity.
- Current treatment lacks personalized predictive algorithms for pediatric valproate dosing.
Purpose of the Study:
- To develop a predictive nomogram for identifying children at risk of suboptimal valproate concentrations.
- To customize valproate treatment based on individual patient characteristics.
Main Methods:
- Retrospective cohort study of 121 pediatric epilepsy patients (aged 2-18 years) on valproate.
- Boruta algorithm and multivariable logistic regression identified predictors of suboptimal concentrations (<50 or >100 μg/mL).
- Nomogram performance assessed using AUC, C-index, calibration plots, and decision curve analysis; internally validated via bootstrap resampling.
Main Results:
- 31.4% of patients had suboptimal valproate concentrations.
- Key predictors identified: daily valproate dose, acute liver injury (ALI), acute kidney injury (AKI), and meropenem use.
- The nomogram demonstrated excellent discrimination (AUC=0.911) and good calibration, with significant associations for AKI (OR 16.5), meropenem (OR 17.39), and ALI (OR 10.86).
Conclusions:
- A validated predictive nomogram integrating dose, AKI, ALI, and meropenem use was developed for pediatric epilepsy patients.
- This tool aids in early identification of patients at risk for suboptimal valproate levels.
- The nomogram facilitates targeted therapeutic drug monitoring for optimized valproate therapy.
Background:
Valproate, a first-line anti-seizure medication, has a narrow therapeutic range of 50-100 μg/mL. Many children are prescribed insufficient doses of valproate, resulting in inadequate seizure control or potential toxicity. Currently, no predictive algorithms are available to customize treatment according to the specific needs of children. Our objective was to develop a nomogram that predicts the likelihood of suboptimal valproate concentrations in pediatric patients with epilepsy.
Methods:
We conducted a single-center retrospective cohort study of pediatric patients with epilepsy aged 2-18 years who were receiving valproate and had steady-state trough concentrations. The primary outcome was the identification of suboptimal valproate concentrations, defined as levels below 50 μg/mL or above 100 μg/mL. The Boruta algorithm was implemented to identify relevant characteristics from demographic, clinical, and pharmacological variables. Significant predictors identified through this process were incorporated into a multivariable logistic regression model, which was subsequently presented as a nomogram. We assessed the model's performance regarding discrimination using the area under the curve (AUC) and concordance index (C-index), calibration through a calibration plot and the Hosmer-Lemeshow test, and clinical value via decision curve analysis to guarantee robustness. Bootstrap resampling was performed for internal validation.
Results:
Among the 121 included patients,38 (31.4%) patients presented with suboptimal concentrations. The Boruta algorithm and multivariate regression analysis identified four predictors: daily valproate dose (mg/kg/d), acute liver injury (ALI), acute kidney injury (AKI), and the concurrent use of meropenem. The model showed excellent discrimination with an AUC of 0.911 (95% CI 0.849-0.974) and an optimism-corrected C-index of 0.902, alongside good calibration. Decision curves showed a clinical net benefit over a broad probability threshold range (3%-99%). AKI (odds ratio [OR] 16.5), meropenem use (OR 17.39), and ALI (OR 10.86) were significantly associated with suboptimal concentrations.
Conclusion:
We developed and internally validated a predictive nomogram that integrates dose, AKI, ALI, and meropenem use to assess the risk of suboptimal concentrations of valproate in pediatric epilepsy. This tool can aid in the early identification of high-risk patients, enabling targeted therapeutic drug monitoring.
More Related Videos
 09:57
Electromagnetic Source Imaging in Presurgical Evaluation of Children with Drug-Resistant Epilepsy
Published on: September 20, 2024
 08:04
Identification and Classification of Position-specific GABAA Receptor Subunit Missense Variants for Their Role In Hippocampal Pyramidal Neurons
Published on: June 6, 2025
Related Concept Videos
 01:23
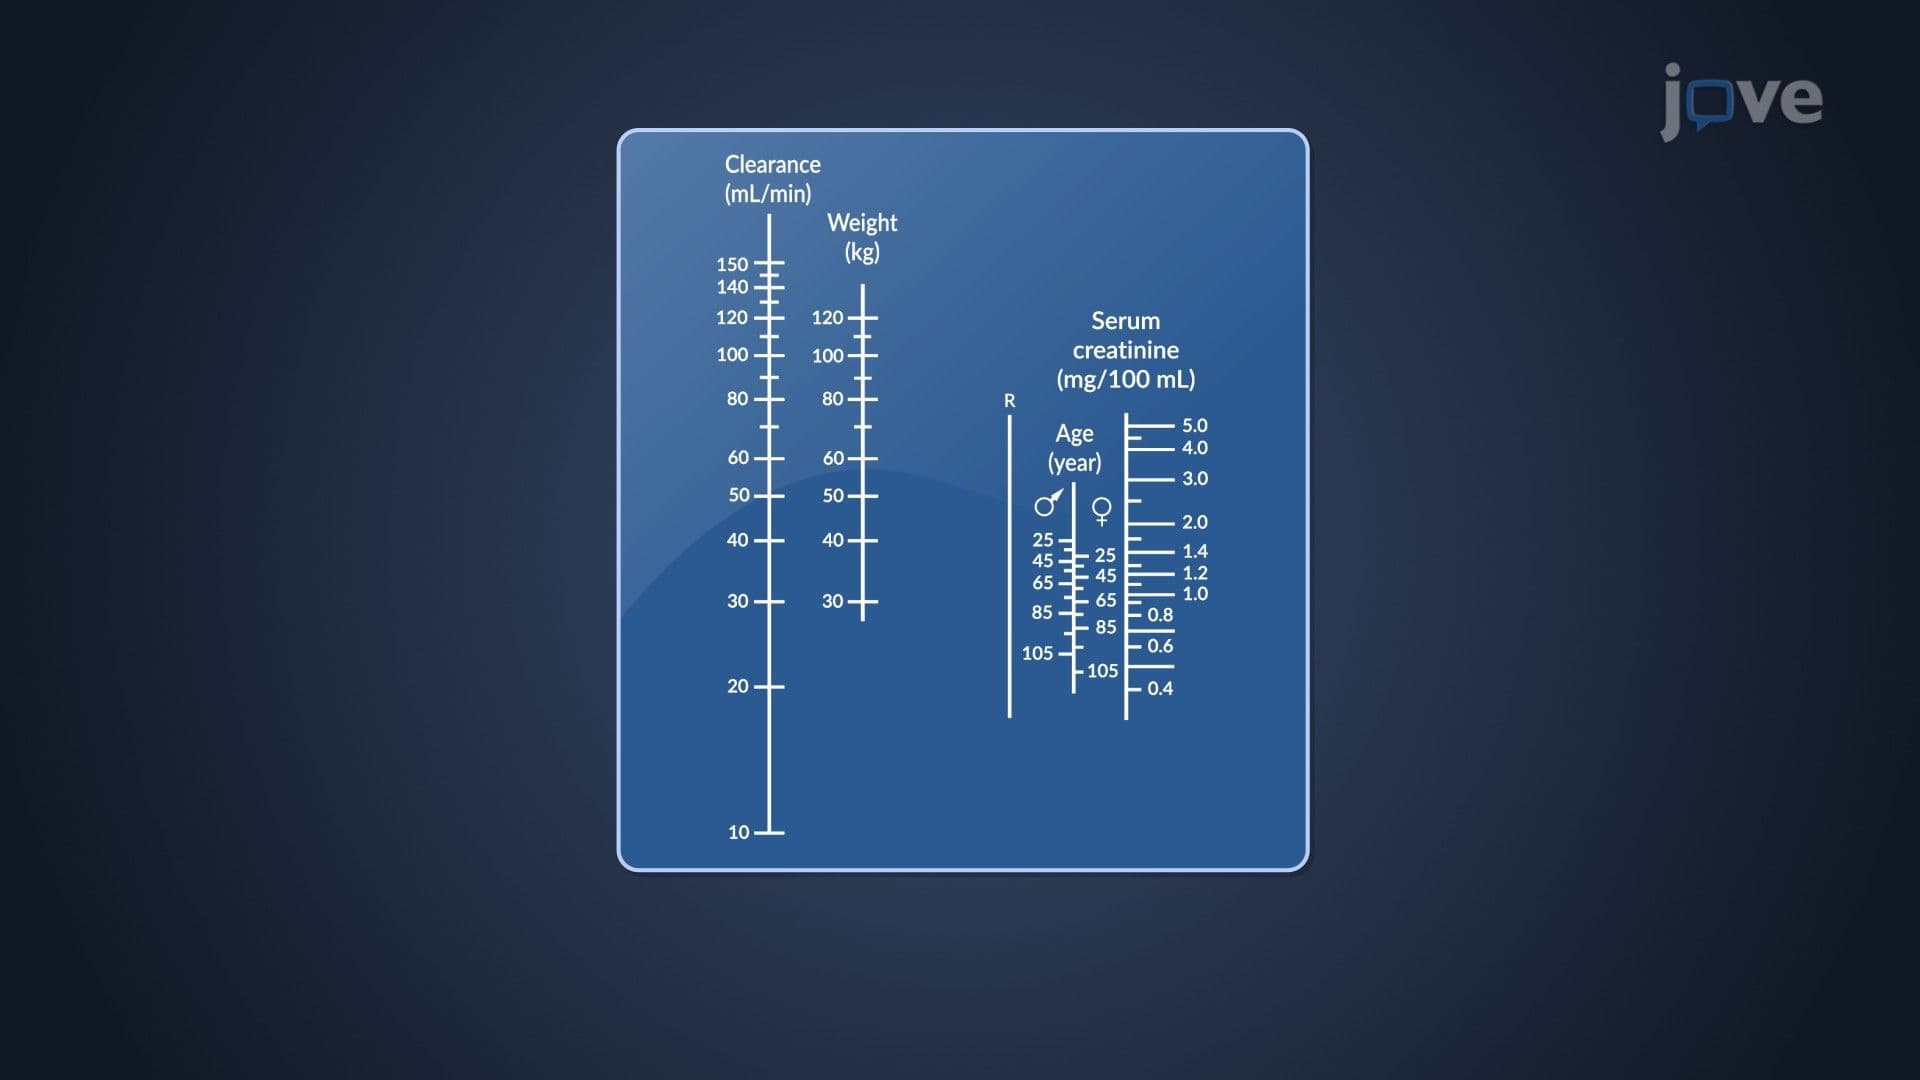
Dosage Regimen Designs: Nomograms and Tabulations
 01:24
Pharmacokinetics in Pediatric Patients: Drug Metabolism
 01:26
Pharmacokinetics in Pediatric Patients: Drug Excretion
 01:17
Pharmacokinetics in Pediatric Patients: Drug Distribution
 01:23
Pharmacokinetics in Pediatric Patients: Overview and Drug Absorption
 01:29
Drug Dosing: Infants and Children