Related Experiment Video
Updated: May 12, 2026
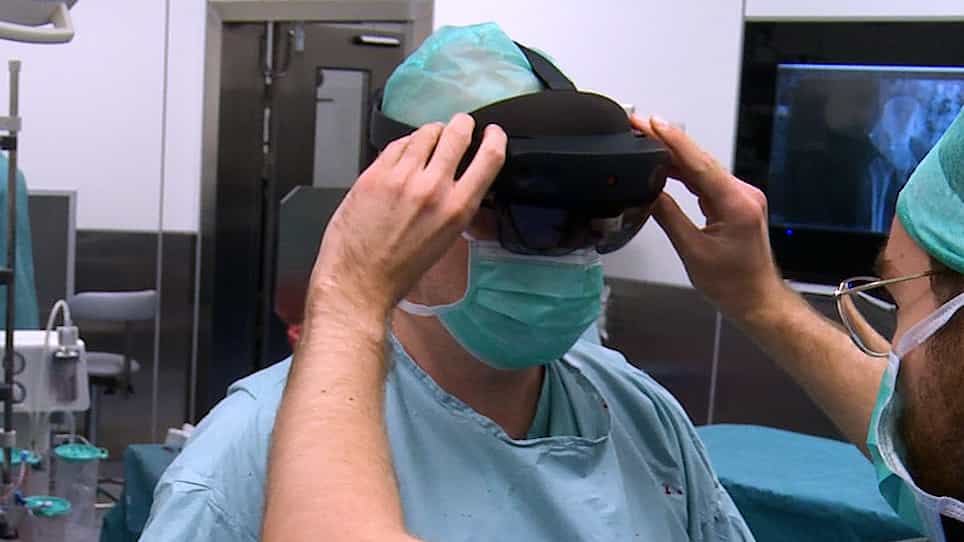

The Use of Mixed Reality in Custom-Made Revision Hip Arthroplasty: A First Case Report
Published on: August 4, 2022
Utilization Trends and Surgical Outcomes of Technology-Assisted Total Hip Arthroplasty in the United States From 2014
Michael S Kim1, Deeyana Roshanzaer1, Melissa R Romoff1
1Department of Orthopaedic Surgery, University of California, Irvine, School of Medicine, Orange, CA, USA.

Background:
Utilization of technology-assisted total hip arthroplasty (TA-THA) with computer navigation or robotic assistance continues to increase in the United States. This study aims to provide an updated examination of the trends and patient factors associated with TA-THA and compare postoperative surgical complications between TA-THA and manual THA (M-THA).
Methods:
A retrospective cohort study was conducted using the TriNetX United States Collaborative Network. Current Procedural Terminology codes were used to identify a cohort of patients who received TA-THA vs M-THA between January 1, 2014, and December 31, 2024. Procedural incidences, regional and institutional distribution, and postoperative complication rates were analyzed. Outcomes included revision surgery, dislocation, periprosthetic fracture, superficial infection, deep infection, and aseptic loosening. Subanalyses were performed at 1-30, 31-90 days, and 3 years. Statistical comparisons used 2-tailed Student's t-tests (P < .05) and odds ratios (ORs).
Results:
During the 10-year study period, 208,003 THA procedures were performed with 19,122 (9.2%) TA-THA and 188,881 (90.8%) M-THA. The utilization of TA-THA increased from 7.2% in 2014 to 14.2% in 2024, with highest adoption in the West (16.9%) and lowest in the Northeast (5.2%) (P < .001). Nonacademic institutions reported greater relative adoption than academic centers (12.7% vs 8.4%; P < .001). At 3-year follow-up, M-THA was associated with higher odds of all-cause revision (OR: 1.28), dislocation (OR: 1.43), deep infection (OR: 1.45), and aseptic loosening (OR: 1.38). In contrast, M-THA exhibited a lower risk of superficial infection (OR: 0.65). No significant difference was observed for the incidence of periprosthetic fractures.
Conclusions:
The utilization of TA-THA has more than doubled over the past decade, with notable regional and institutional differences. Compared to M-THA, TA-THA was associated with a decreased risk of multiple postoperative complications over a 3-year period. Further studies will be needed to determine whether this technology should be widely adopted by general orthopaedic surgeons performing THA or if it will primarily serve as a tool for arthroplasty surgeons seeking enhanced efficiency and precision.

